Related Experiment Video
Updated: Oct 19, 2025

Direct Mouse Trauma/Burn Model of Heterotopic Ossification
Published on: August 6, 2015
Heterotopic Ossifications after Fractures of the Anterior Pelvic Segment: Overview of Morphology and Clinical
D Kolesar1, V Džupa1,2, K Šídlo2
1Centre for Integrated Studies of the Pelvis, Third Faculty of Medicine, Charles University, Prague.

Abstract:
PURPOSE OF THE STUDY In certain patients after treated pelvic fractures, heterotopic ossifications can be observed in the area of the pubic bone, which protrude ventrally, and often also laterally and distally into surrounding soft tissues of the groin or even medially into the proximal thigh. These ossifications are shaped like sharp spikes of various lengths, which is why the authors refer to them as "spicules". In some patients, these ossifications are also associated with pain. The aim of this study was to provide an overview of the morphology of heterotopic ossifications of the anterior segment of the pelvis and to discuss the etiology of their origin, and further to determine the incidence, risk factors and clinical significance of these "spike-like" ossifications. MATERIAL AND METHODS X-ray images of patients treated for pelvic injuries between 2009 and 2018, in whom radiological documentation was available at least 12 months after the injury or surgery were evaluated. Patients with acetabular fractures or combined pelvic and acetabular injuries were not included in the study. Possible risk factors studied included gender, severity of injury, type of fracture according to the AO / ASIF classification, concomitant bladder injury, method of treatment and type of osteosynthesis of the anterior segment of the pelvis. The categorial data concerning risk factors for the observed "spicule" type ossifications was statistically evaluated using the chi-square test at the 5% level of significance. RESULTS The studied group consisted of 218 patients (121 women, 97 men) aged 13 to 92 years of age (mean age was 54 years, median age was 55 years). Heterotopic "spicule" type ossifications occurred in 21 patients (4 females, 17 males) aged 18 to 76 years (mean 39 years, median 41 years). Significant risk factors in the observed ossification group included male sex (p = 0.0004), severity of trauma (predominance of "spicules" was seen in multiple trauma patients, (p = 0.0024), unstable pelvic injury according to AO / ASIF classification (predominance of "spicules" in type B and C fractures over type A fractures, (p = 0.0013), concomitant bladder injury (p = 0.0009) and in patients undergoing surgical treatment of the fracture (p < 0.0001), where all the observed spicules were seen in patients undergoing anterior pelvic segment osteosynthesis. A statistically significant difference was also evident when comparing the osteosynthetic material used in the anterior segment (a increased incidence of ossifications was seen in patients undergoing plate fixation compared to patients in whom pubic screws were used, p = 0.0050). DISCUSSION Heterotopic ossifications are described as relatively common consequences of pelvic fractures, but are not considered a major problem because they usually do not produce any clinical correlations. The causes of post-traumatic and postoperative ossifications in the pelvic area include the effects of high energy traumas, extensive surgical procedures, prolonged artificial lung ventilation, and post-infectious states after complications of surgical treatment. CONCLUSIONS The study identified risk factors for heterotopic "spicule" type ossifications. The identified risk factors include male sex, severity of injury, unstable type of fracture, concomitant bladder injury, surgical treatment, and the use of massive implants. Only the effect of bladder injuries can be partially influenced by performing less invasive surgical techniques during combined pelvic and bladder injuries. Key words: pelvic fracture, pelvic injury, complications, heterotopic ossifications, multiple trauma, unstable pelvic trauma, urinary bladder injury.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025
Related Concept Videos
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into ...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:18
Classification of Bones
Long and Short Bones
The appendicular skeleton, particularly the upper and lower limbs, is primarily made of long and short bones. The...
 01:24
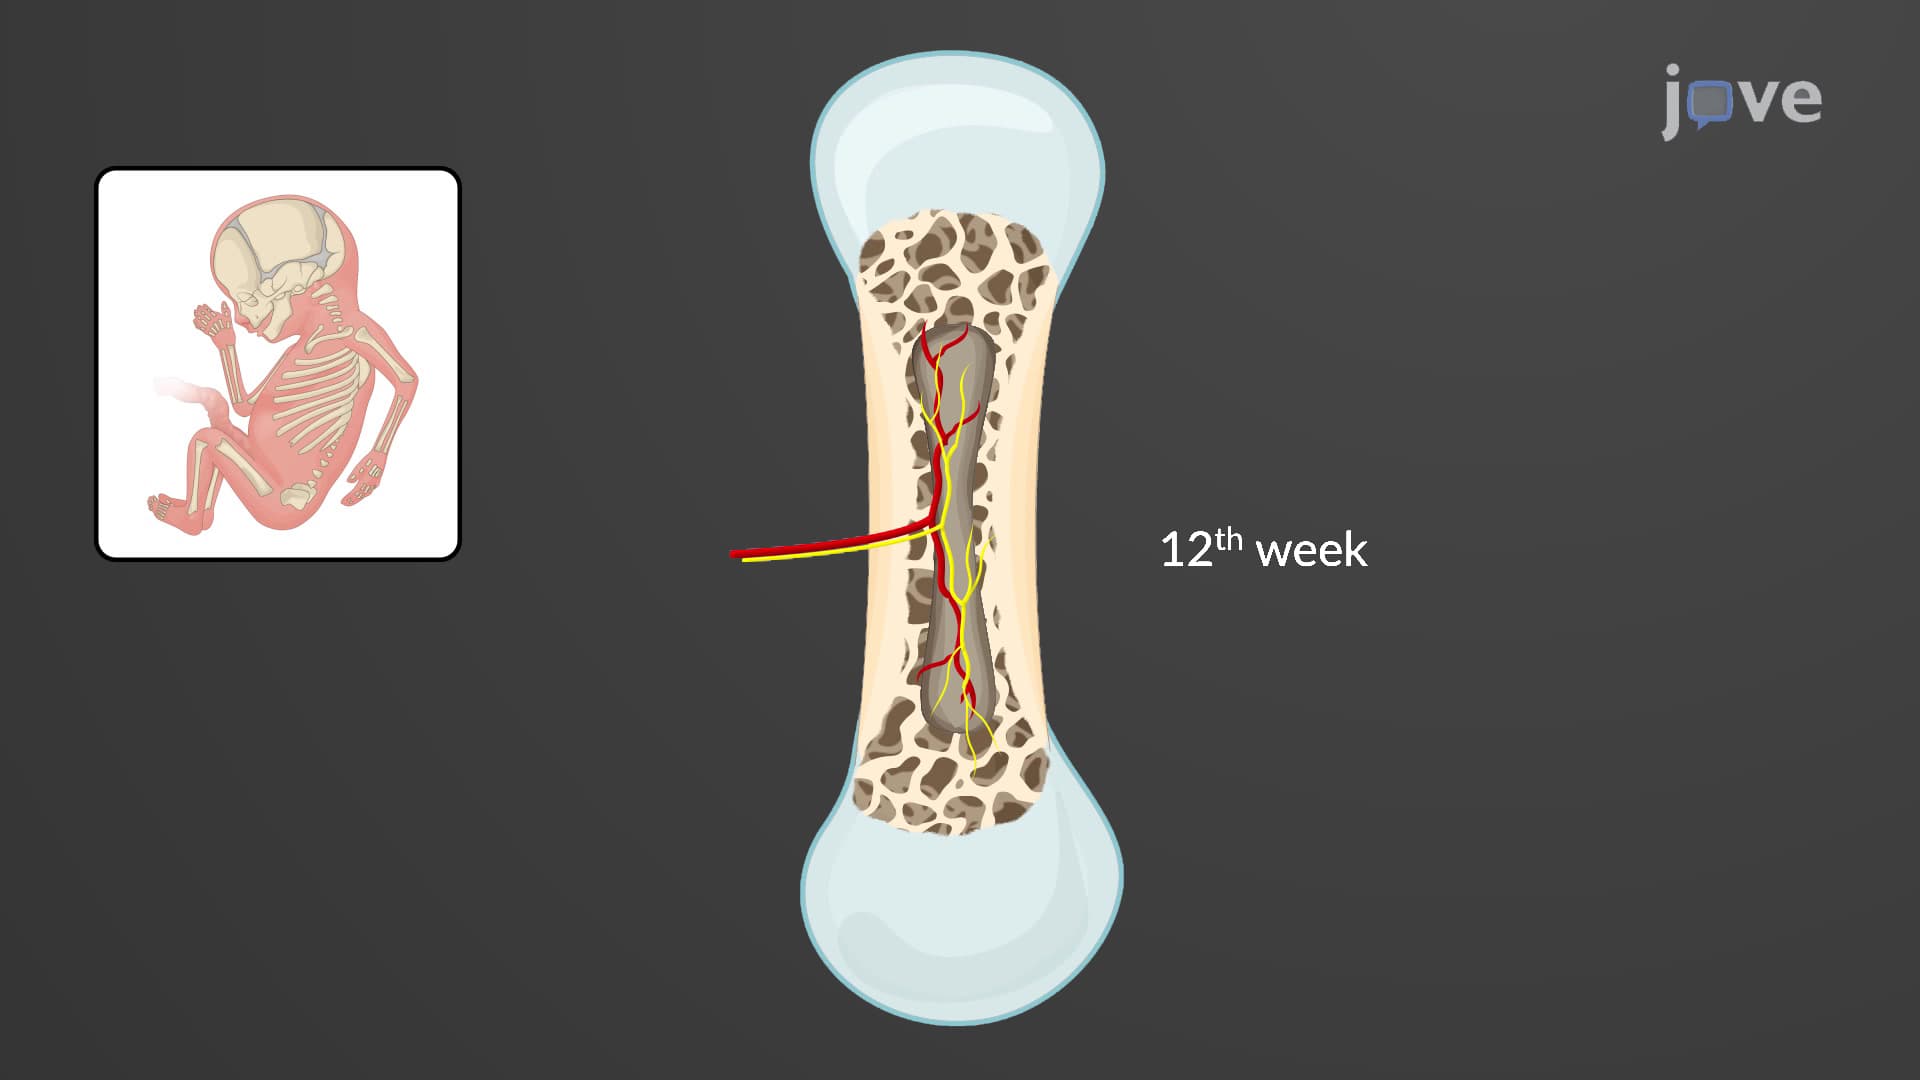
Bone Formation by Endochondral Ossification
 01:17
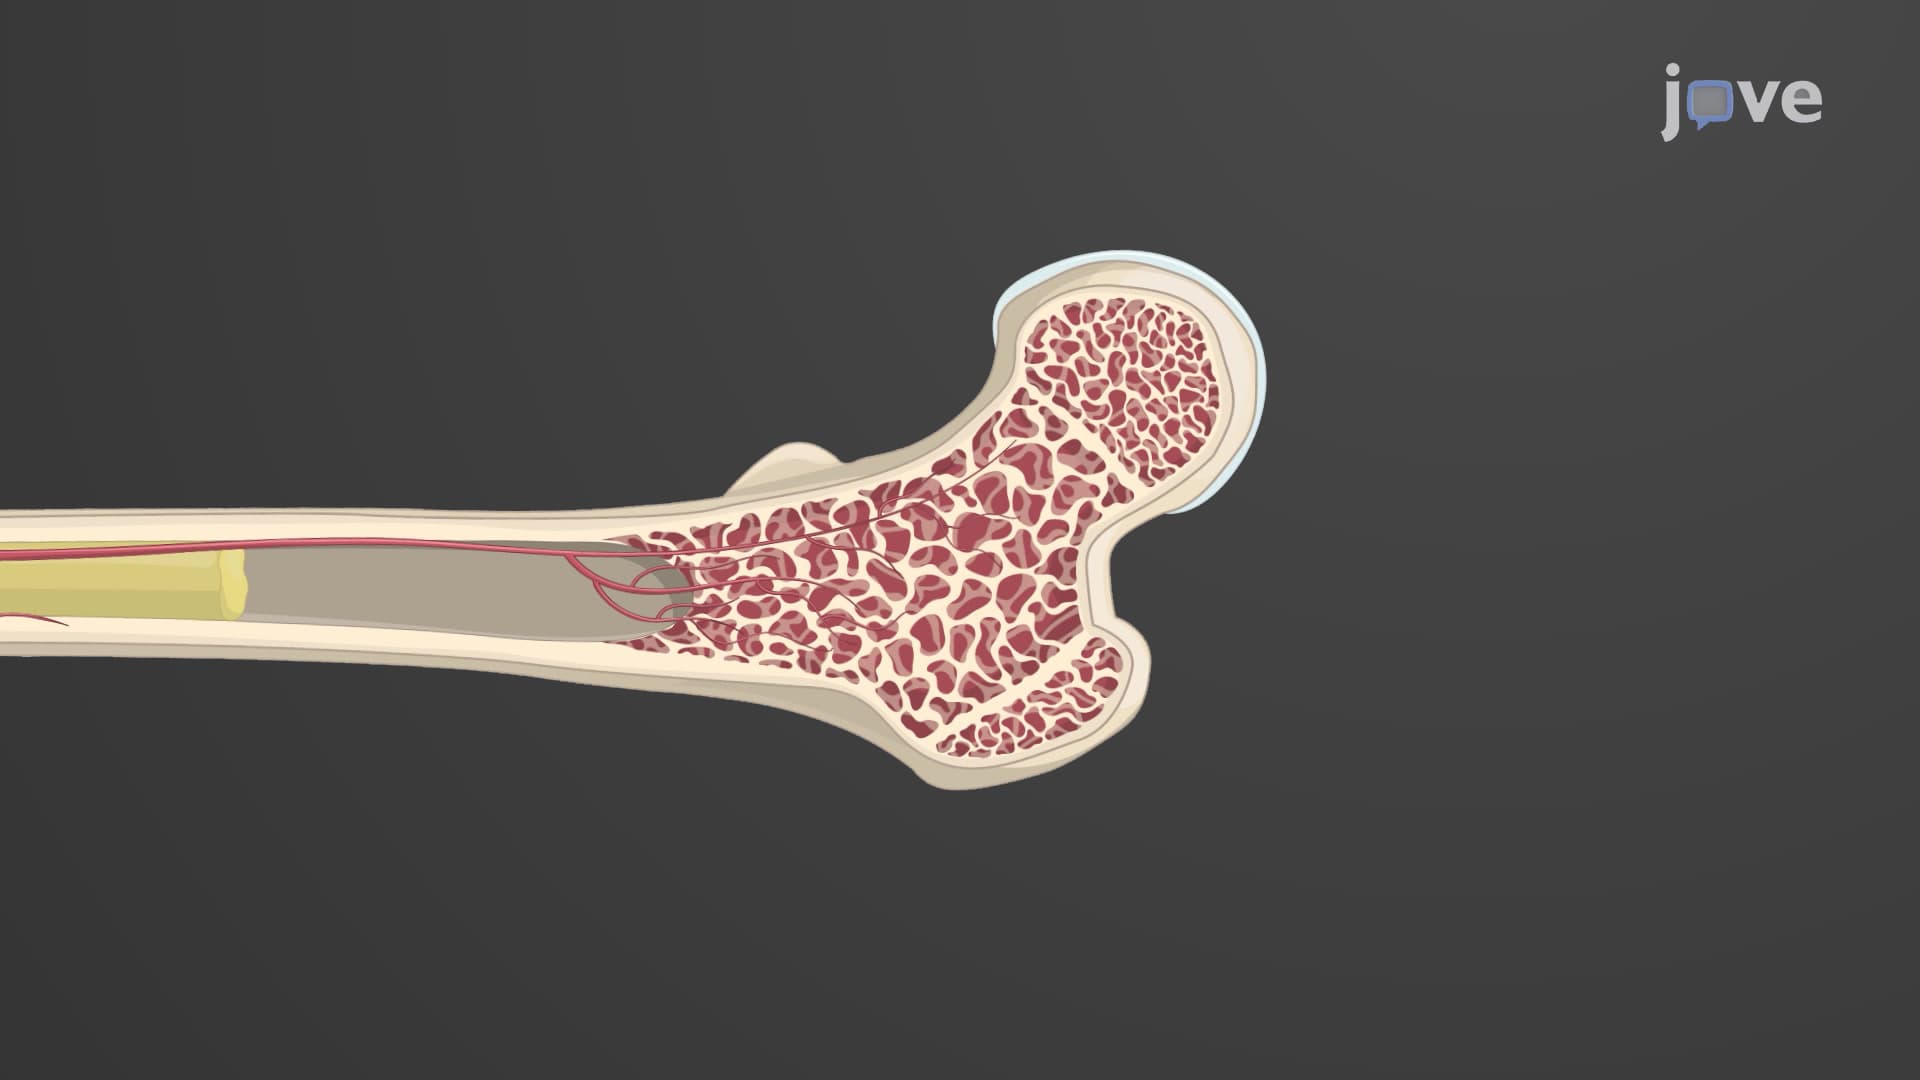
Gross Anatomy of Bone
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...