Reduced Systolic Function and Not Genetic Variants Determine Outcome in Pediatric and Adult Left Ventricular Noncompaction Cardiomyopathy
Related Experiment Video
Updated: Oct 19, 2025

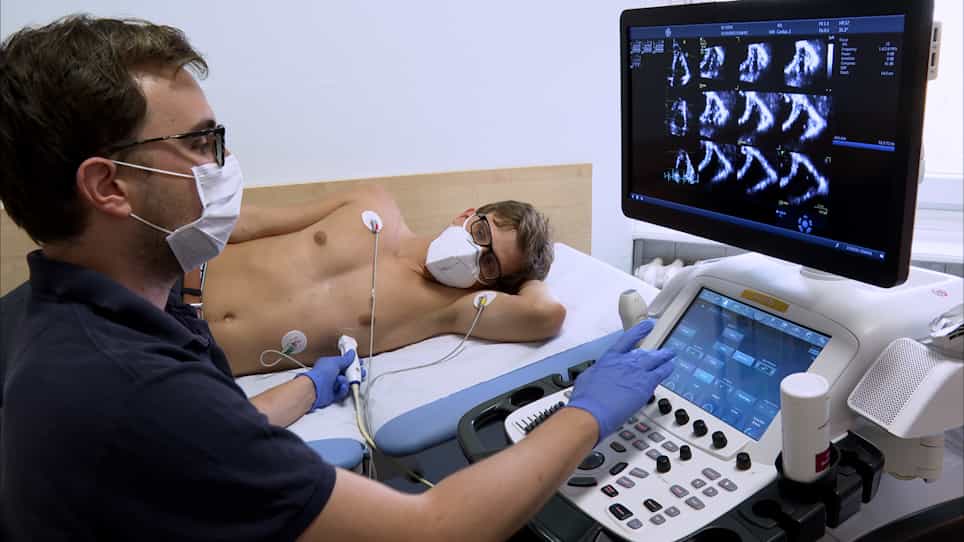
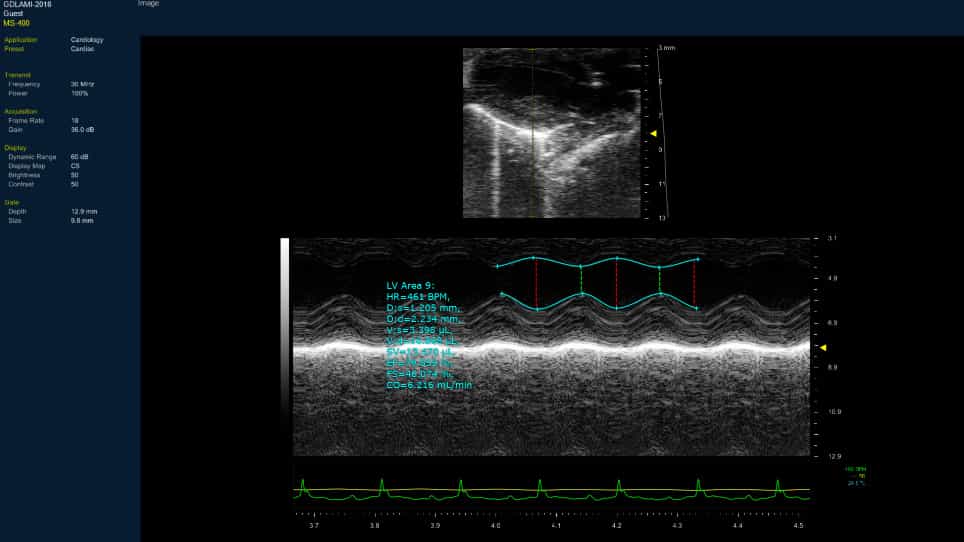
Biventricular Assessment of Cardiac Function and Pressure-Volume Loops by Closed-Chest Catheterization in Mice
Published on: June 15, 2020
Alina Schultze-Berndt1,2, Jirko Kühnisch2,3, Christopher Herbst2,3
1Department of Pediatric Cardiology, Charité - Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin, Humboldt-Universität zu Berlin, Berlin Institute of Health, Berlin, Germany.

Insights
Genetic variants in left ventricular noncompaction cardiomyopathy (LVNC CMP) do not predict major adverse cardiac events (MACE). Reduced left ventricular systolic function is the primary risk factor for MACE in LVNC CMP patients.
Area of Science:
- Cardiology
- Genetics
- Molecular Biology
Background:
- Left ventricular noncompaction cardiomyopathy (LVNC CMP) is a genetic heart muscle disease with unclear genotype-phenotype correlations and clinical outcomes.
- Understanding genetic contributions is crucial for risk stratification and management in both pediatric and adult patients.
Purpose of the Study:
- To investigate the correlation between genetic variants and clinical outcomes in patients with LVNC CMP.
- To determine if genetic findings can predict major adverse cardiac events (MACE).
Main Methods:
- Retrospective multicenter study of 149 unrelated LVNC CMP index patients diagnosed between 1987 and 2017.
- Next-generation sequencing of 174 target genes using the Illumina TruSight Cardio Sequencing Panel.
- Analysis of major adverse cardiac events (MACE) including cardiac death, heart transplantation, and mechanical circulatory support.
Main Results:
- Genetic variants were identified in 77% of index patients, with most classified as variants of unknown significance (VUS).
- The yield of likely pathogenic or pathogenic variants was 31%. Common genes involved were MYH7, TTN, and MYBPC3.
- Genetic variants did not predict MACE risk. Reduced left ventricular systolic function (OR 4.6) and increased LVEDD were significant risk factors for MACE.
Conclusions:
- Genetic variants in LVNC CMP do not serve as predictors for MACE in pediatric or adult populations.
- Reduced left ventricular systolic function is the primary independent risk factor for MACE.
- Genetic screening is valuable for cascade screening to identify at-risk family members.
Abstract:
Background: Left ventricular noncompaction cardiomyopathy (LVNC CMP) is a genetic cardiomyopathy. Genotype-phenotype correlation and clinical outcome of genetic variants in pediatric and adult LVNC CMP patients are still unclear. Methods: The retrospective multicenter study was conducted in unrelated index patients with LVNC CMP, diagnosed between the years 1987 and 2017, and all available family members. All index patients underwent next-generation sequencing for genetic variants in 174 target genes using the Illumina TruSight Cardio Sequencing Panel. Major adverse cardiac events (MACE) included mechanical circulatory support, heart transplantation, survivor of cardiac death, and/or all-cause death as combined endpoint. Results: Study population included 149 LVNC CMP patients with a median age of 27.8 (9.2-44.8) years at diagnosis; 58% of them were symptomatic, 18% suffered from non-sustained and sustained arrhythmias, and 17% had an implantable cardioverter defibrillator (ICD) implanted. 55/137 patients (40%) were ≤ 18 years at diagnosis. A total of 134 variants were identified in 87/113 (77%) index patients. 93 variants were classified as variant of unknown significance (VUS), 24 as likely pathogenic and 15 as pathogenic. The genetic yield of (likely) pathogenic variants was 35/113 (31%) index patients. Variants occurred most frequently in MYH7 (n=19), TTN (n = 10) and MYBPC3 (n = 8). Altogether, sarcomere gene variants constituted 42.5% (n = 57) of all variants. The presence or absence of (likely) pathogenic variants or variants in specific genes did not allow risk stratification for MACE. Reduced left ventricular (LV) systolic function and increased left ventricular end-diastolic diameter (LVEDD) were risk factors for event-free survival in the Kaplan-Meier analysis. Through multivariate analysis we identified reduced LV systolic function as the main risk factor for MACE. Patients with reduced LV systolic function were at a 4.6-fold higher risk for MACE. Conclusions: Genetic variants did not predict the risk of developing a MACE, neither in the pediatric nor in the adult cohort. Multivariate analysis emphasized reduced LV systolic function as the main independent factor that is elevating the risk for MACE. Genetic screening is useful for cascade screening to identify family members at risk for developing LVNC CMP.
More Related Videos
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:22
Mitral Stenosis I: Introduction
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy