Related Experiment Video
Updated: Oct 19, 2025
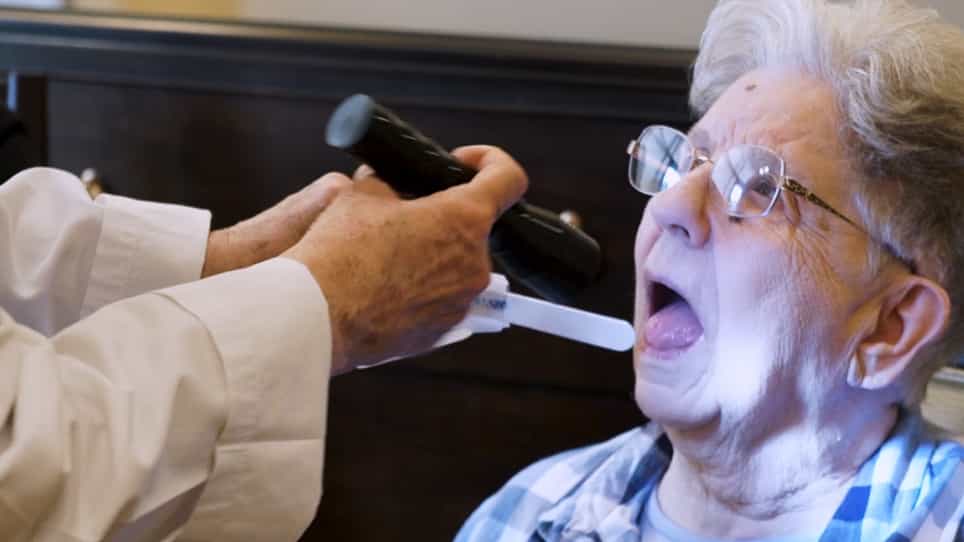

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
How physicians evaluate patients with dementia who present with shortness of breath
Dan P Ly1,2,3, Paul G Shekelle4
1Hospitalist Division, VA Greater Los Angeles Healthcare System, Los Angeles, California, USA.

Background:
Whether the presence of dementia in patients makes it difficult for physicians to assess the risk such patients might have for serious conditions such as pulmonary embolism (PE) is unknown. Our objective was to examine the differential association of four clinical factors (deep venous thrombosis (DVT)/PE, malignancy, recent surgery, and tachycardia) with PE testing for patients with dementia compared to patients without dementia.
Methods:
We performed a cross-sectional study of emergency department (ED) visits to 104 Veterans Affairs (VA) hospitals from 2011 to 2018 by patients aged 60 years and over presenting with shortness of breath (SOB). Our outcomes were PE testing (CT scan and/or D-dimer) and subsequently diagnosed acute PE.
Results:
The sample included 593,001 patient visits for SOB across 7124 ED physicians; 5.6% of the sample had dementia, and 10.6% received PE testing. Three of the four clinical factors examined had a lower association with PE testing for patients with dementia. For example, after taking into account that at baseline, physicians were 0.9 percentage points less likely to test patients with dementia than patients without dementia for PE, physicians were an additional 2.6 percentage points less likely to test patients with dementia who had tachycardia than patients without dementia who had tachycardia. We failed to find evidence that any clinical factor examined had a differentially lower association with a subsequently diagnosed acute PE for patients with dementia.
Conclusions:
Clinical factors known to be predictive of PE risk had a lower association with PE testing for patients with dementia compared to patients without dementia. These results may be consistent with physicians missing these clinical factors more often when evaluating patients with dementia, but also with physicians recognizing such factors but not using them in the decision-making process. Further understanding how physicians evaluate patients with dementia presenting with common acute symptoms may help improve the care delivered to such patients.
More Related Videos


Related Concept Videos
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Acute Respiratory Failure-IV