Related Experiment Video
Updated: Oct 19, 2025

Detrusor Underactivity Model in Rats by Conus Medullaris Transection
Published on: August 28, 2020
Sacral Neuromodulation Changes Pelvic Floor Activity in Overactive Bladder Patients-Possible New Insights in
Jeroen Voorham1, Donald Vaganée2, Petra Voorham-van der Zalm3
1Department of Urology, Leiden University Medical Center, Leiden, The Netherlands; Department of Urology, Antwerp Surgical Training, Anatomy and Research Centre (ASTARC), Faculty of Medicine and Health Sciences, University of Antwerp, Antwerp, Belgium.

Objectives:
To evaluate if electrodiagnostic tools can advance the understanding in the effect of sacral neuromodulation (SNM) on pelvic floor activity, more specifically if SNM induces changes in pelvic floor muscle (PFM) contraction.
Materials And Methods:
Single tertiary center, prospective study (October 2017-May 2018) including patients with overactive bladder syndrome undergoing SNM. Electromyography of the PFM was recorded using the Multiple Array Probe Leiden. The procedure consisted of consecutive stimulations of the lead electrodes with increasing intensity (1-3, 5, 7, 10 V). Recordings were made after electrode placement (T0) and three weeks of SNM (T1). Patients with >50% improvement were defined as responders, others as nonresponders. For the analyses, the highest electrical PFM response (EPFMR), defined as the peak-to-peak amplitude of the muscle response, was identified for each intensity. The sensitivity (intensity where the first EPFMR was registered and the normalized EPFMR as percentage of maximum EPFMR) and the evolution (EMFPR changes over time) were analyzed using linear mixed models.
Results:
Fourteen patients were analyzed (nine responders, five nonresponders). For nonresponders, the PFM was significantly less sensitive to stimulation after three weeks (T0: 1.7 V, T1: 2.6 V). The normalized EPFMR was (significantly) lower after three weeks for the ipsilateral side of the PFM for the clinically relevant voltages (1 V: 36%-23%; p = 0.024, 2 V: 56%-29%; p = 0.00001; 3 V: 63%-37%; p = 0.0002). For the nonresponders, the mean EPFMR was significantly lower at 8/12 locations at T1 (T0: 109 μV, T1: 58 μV; mean p = 0.013, range <0.0001-0.0867). For responders, the sensitivity and evolution did not change significantly.
Conclusions:
This is the first study to describe in detail the neurophysiological characteristics of the PFM, and the changes over time upon sacral spinal root stimulation, in responders and nonresponders to SNM. More research is needed to investigate the full potential of EPFMR as a response indicator.


Related Concept Videos
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating...
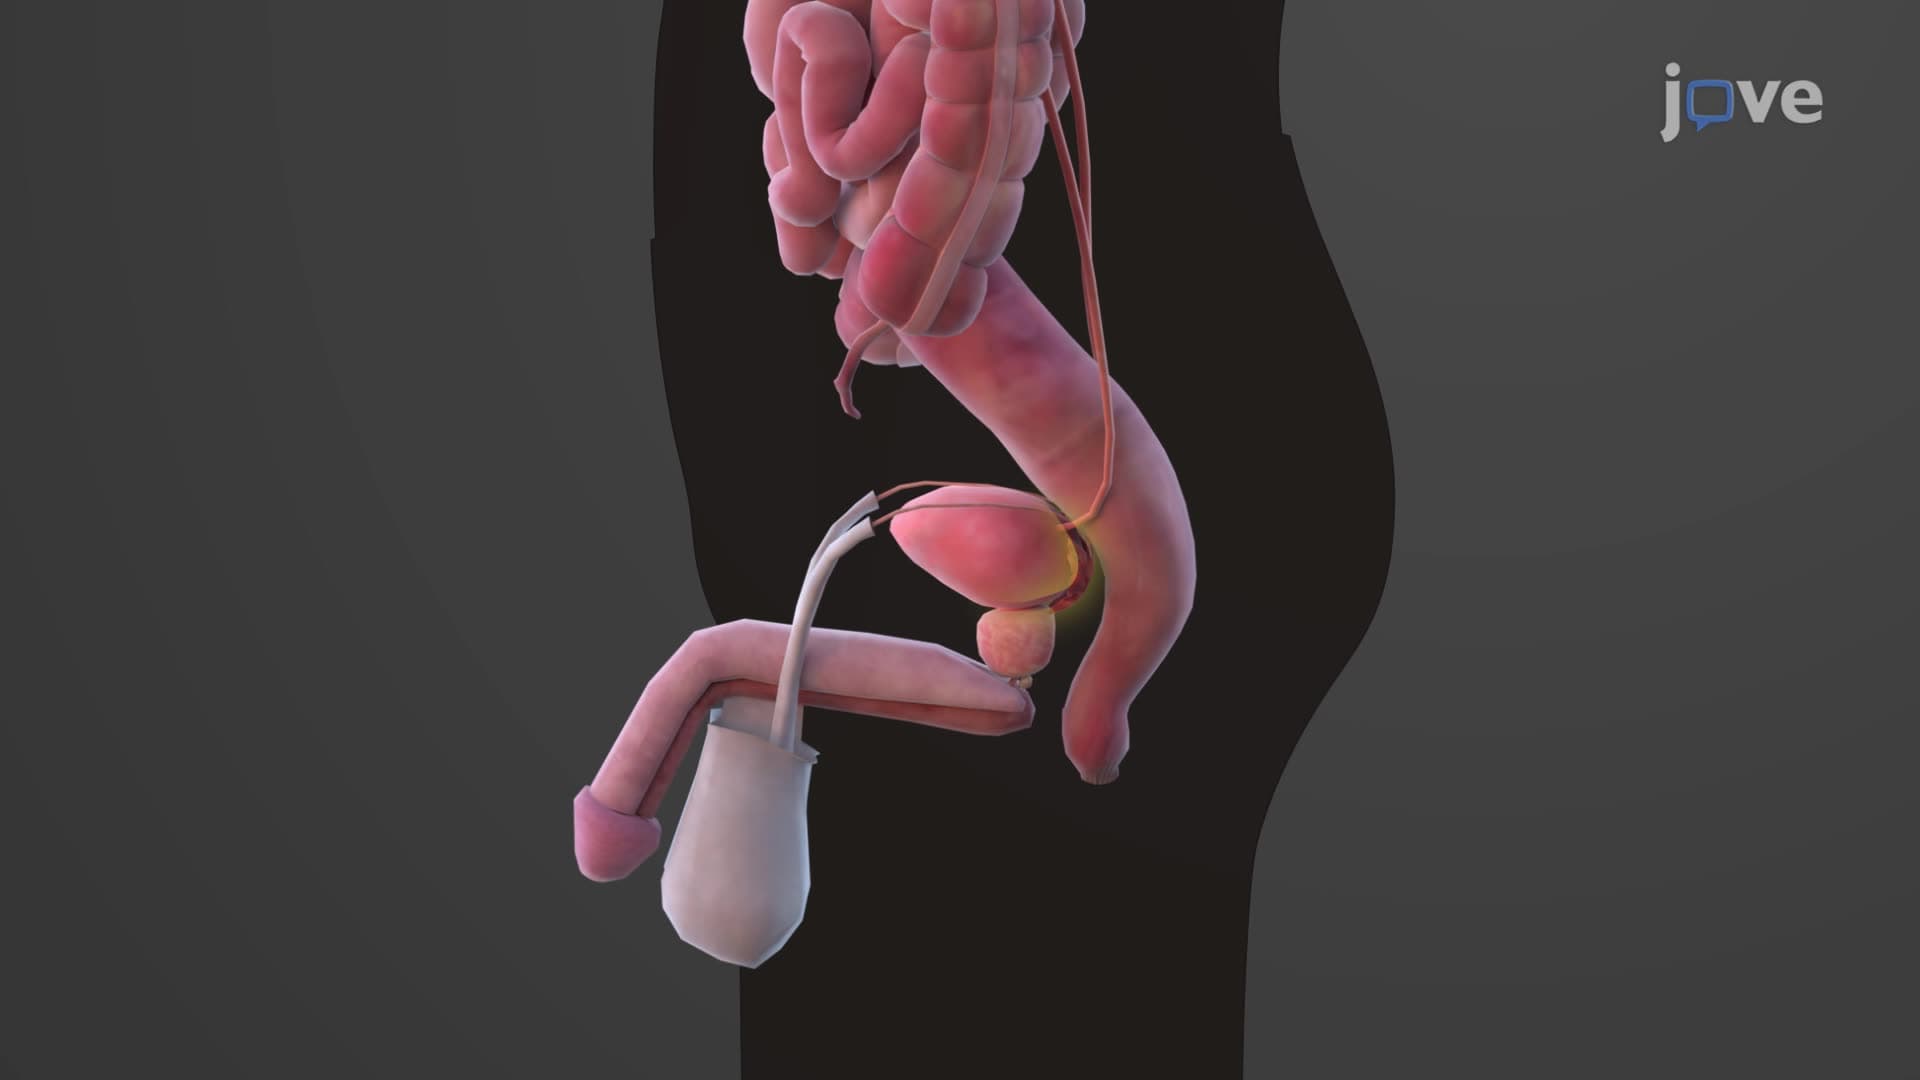 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:23
Drugs Affecting GI Tract Motility: Serotonin Receptor Agonists
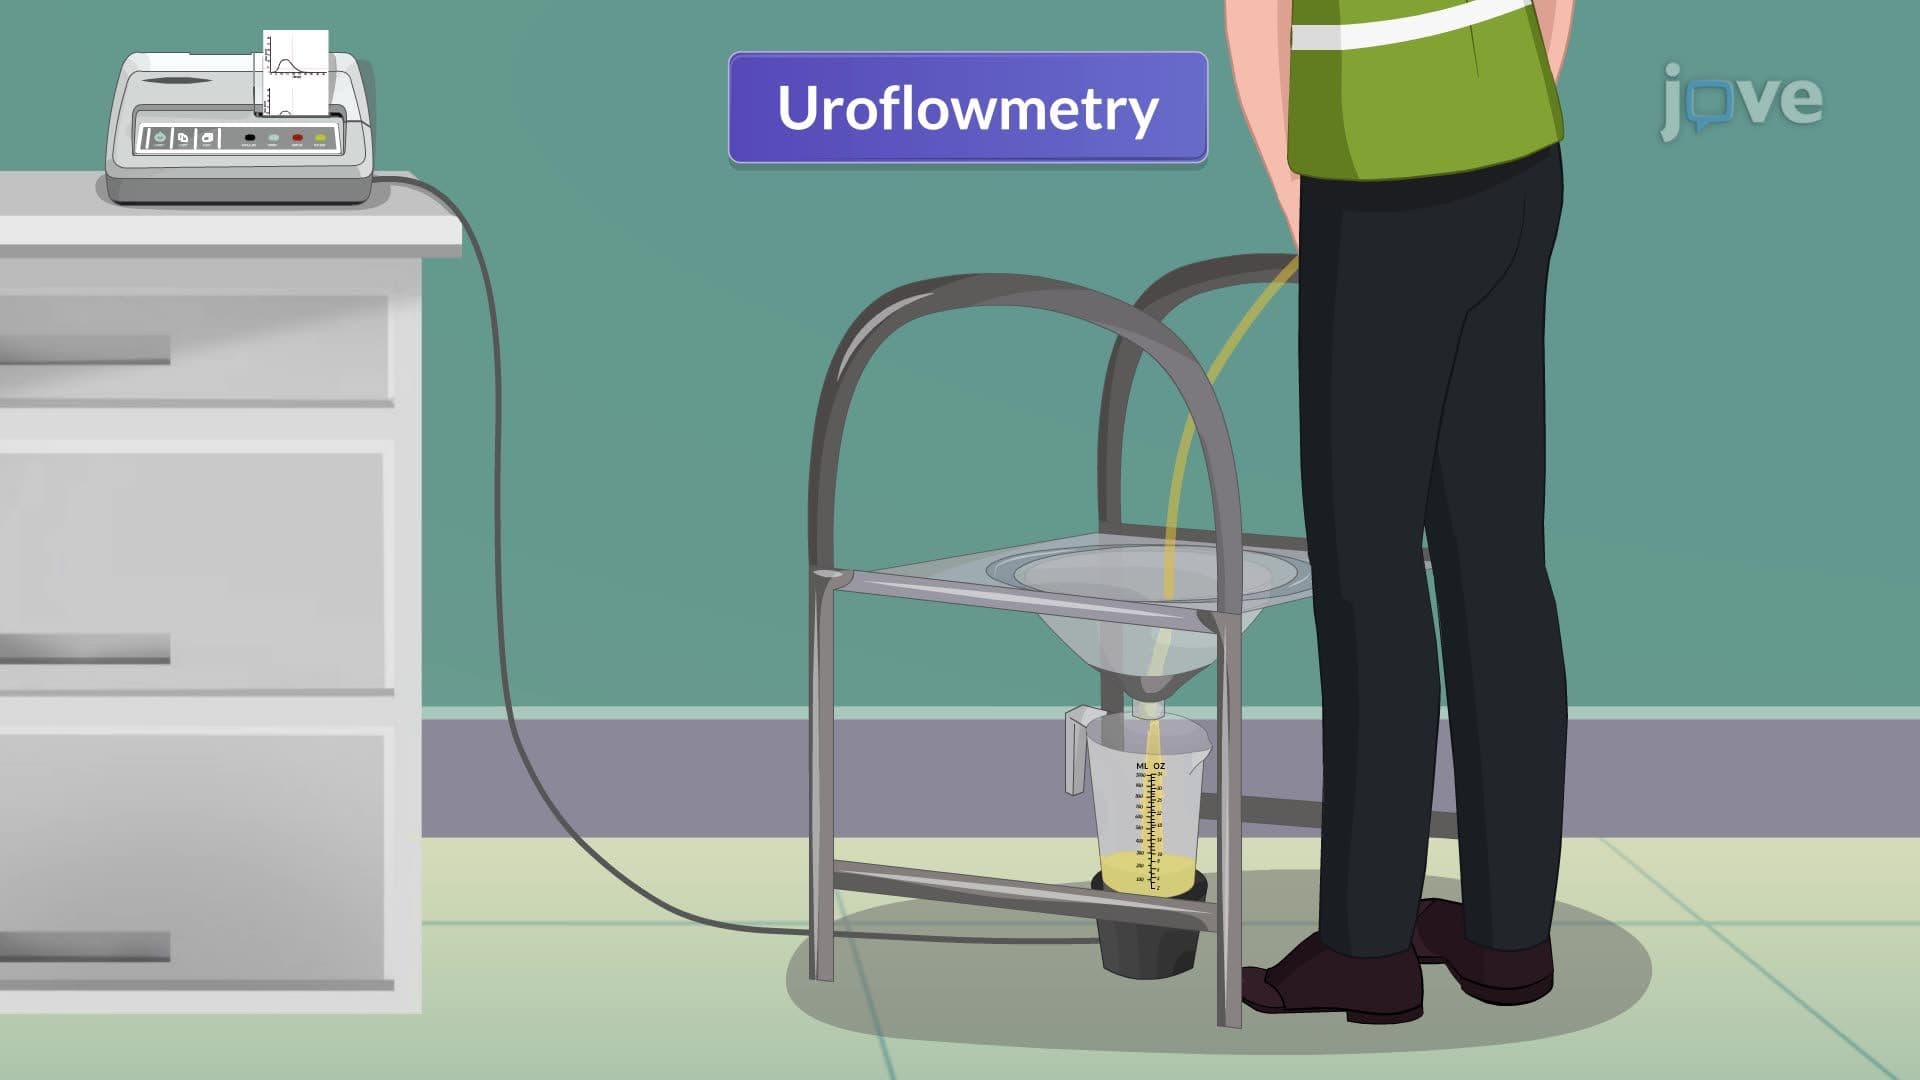 01:19
Urodynamic Studies: Uroflowmetry
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...