Related Experiment Video
Updated: Oct 19, 2025
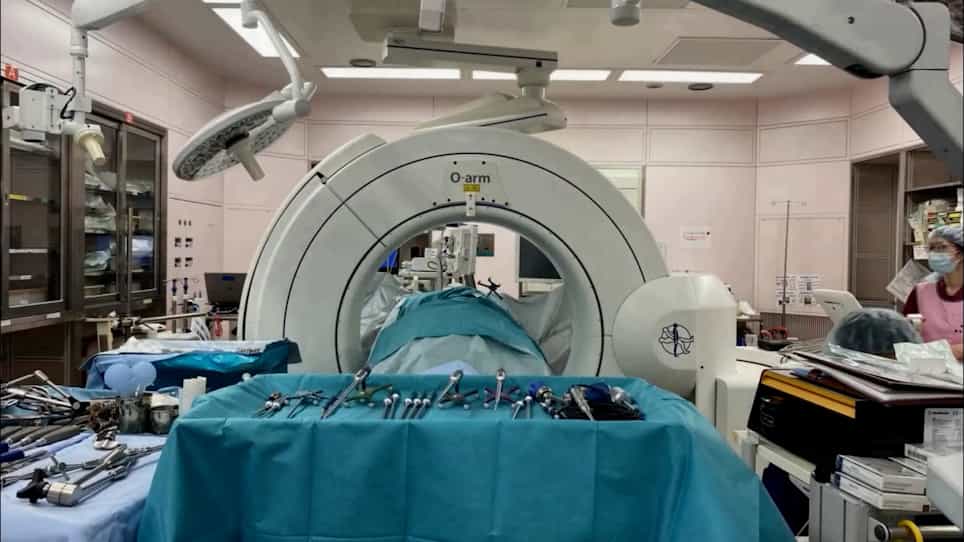

C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Suggestion of a safe zone for C1 pedicle screws depending on anatomical peculiarities
Maximilian Lenz1, Arne Harland2, Philipp Egenolf2
1Department for Orthopaedic and Trauma Surgery, Faculty of Medicine, University of Cologne, Joseph-Stelzmann Strasse 24, Kerpener Str. 62, 50931, Cologne, Germany. maximilian.lenz@uk-koeln.de.

Objective:
For surgical treatment of instable upper cervical injuries, the Harms technique using lateral mass screws provides rigid fixation and favourable clinical outcomes. The use of the posterior arch of C1 as a "pedicle" allows for screw anchorage, giving improved biomechanical stability. Therefore, the aim of this study was to introduce a bilateral safe zone for C1 pedicle screws, regarding screw angulation and pedicle height.
Material And Methods:
We retrospectively reviewed the CT scans of 500 patients. Three-dimensional reformats were generated for detailed measurements. Centre screw entry point (EP), length of lateral mass as screw trajectory, lateral mass width (LMW), length of screw trajectory (ST), maximal divergence (DI) and maximal convergence (CON) from EP without perforation, and pedicle height (PH) of the posterior arch were measured.
Results:
The 500 cases consisted of 335 males and 165 females, with a mean age of 49.5 years. Measurements did not demonstrate significant side-related differences. The mean screw entry point was 22.8 mm from the midline-axis (left 22.6 mm; right 23.0 mm). From this point, a safe zone between 11.6° of divergence and 19.6° of convergence was detected. Measurements of female patients were generally smaller, with significant differences from male patients (p < 0.05). 158 subjects (31.6%) had a PH < 4 mm.
Discussion:
C1 pedicle screws were feasible in the majority of patients. Proposing a safe zone for screw angulation may provide safety and avoid screw perforation. However, detailed knowledge of the individual C1 anatomy and the preoperative measurement is essential in the operative planning.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 09:07
An Anesthesia, Surgery, and Harvest Method for the Evaluation of Transpedicular Screws Using an In Vivo Porcine Lumbar Spine Model
Published on: May 31, 2017