Related Experiment Video
Updated: Oct 19, 2025


Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Parenchymal Brain Abscess as an Intracranial Complication After Sinusitis
Maria C Michali1, Ioannis G Kastanioudakis1, Lentiona V Basiari1
1Department of Otorhinolaryngology, Head and Neck Surgery, University Hospital of Ioannina, Ioannina, GRC.

Abstract:
Brain abscesses caused by sinusitis are rare in the antibiotic era. The purpose of the current manuscript was to report a rare case of a brain abscess located mainly in the frontal lobe after sinusitis, which was initially thought to be meningitis or encephalitis. A 39-year-old man was transferred to our hospital from another neighbouring hospital with tonic-clonic seizures, severe headache, and purulent nasal secretions. For one week, he was taking antibiotics for sinusitis. The computed tomography indicated lesions in the right sinuses but not in the parenchymal brain and thus antibiotics along with antiepileptic drugs were given. However, due to the deterioration of symptoms, magnetic resonance imaging was executed, which revealed an abscess in the frontal lobe. Afterward, an anterior ethmoidectomy and middle maxillary antrostomy were performed in order to drain the purulent content from the right sinuses. Ten days later, the patient presented disorientation and thus an open craniotomy for successful removal of the parenchymal abscess was performed. One month later, the patient was discharged with mild irritability, which was eliminated gradually over the next two months. Conclusively, brain abscesses can be caused by local spread from an infection of the paranasal sinus. The contribution of imaging modality is very significant not only for the early diagnosis but also for the therapeutic management of such cases. Frequently antibiotic treatment is insufficient and surgery may be required.
Insights
Brain abscesses from sinusitis are rare but can occur. Early diagnosis with imaging and often surgical intervention are crucial for effective treatment.
Area of Science:
- Neurology
- Otolaryngology
- Infectious Diseases
Background:
- Brain abscesses secondary to sinusitis are uncommon in the current antibiotic era.
- This case highlights a rare instance of frontal lobe abscess originating from sinusitis.
Observation:
- A 39-year-old male presented with seizures, headache, and purulent nasal discharge after a week of sinusitis treatment.
- Initial CT scans showed sinus lesions but no brain parenchymal involvement, leading to antibiotic and antiepileptic drug treatment.
- Deterioration prompted MRI, revealing a frontal lobe abscess.
Findings:
- Surgical sinus drainage (ethmoidectomy and antrostomy) was performed.
- A subsequent craniotomy successfully removed the brain abscess.
- The patient recovered with gradual resolution of irritability.
Implications:
- Sinusitis can lead to serious intracranial complications like brain abscesses.
- Advanced imaging (MRI) is vital for accurate diagnosis and management planning.
- Antibiotic therapy alone is often insufficient; surgical intervention may be necessary.


Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:18
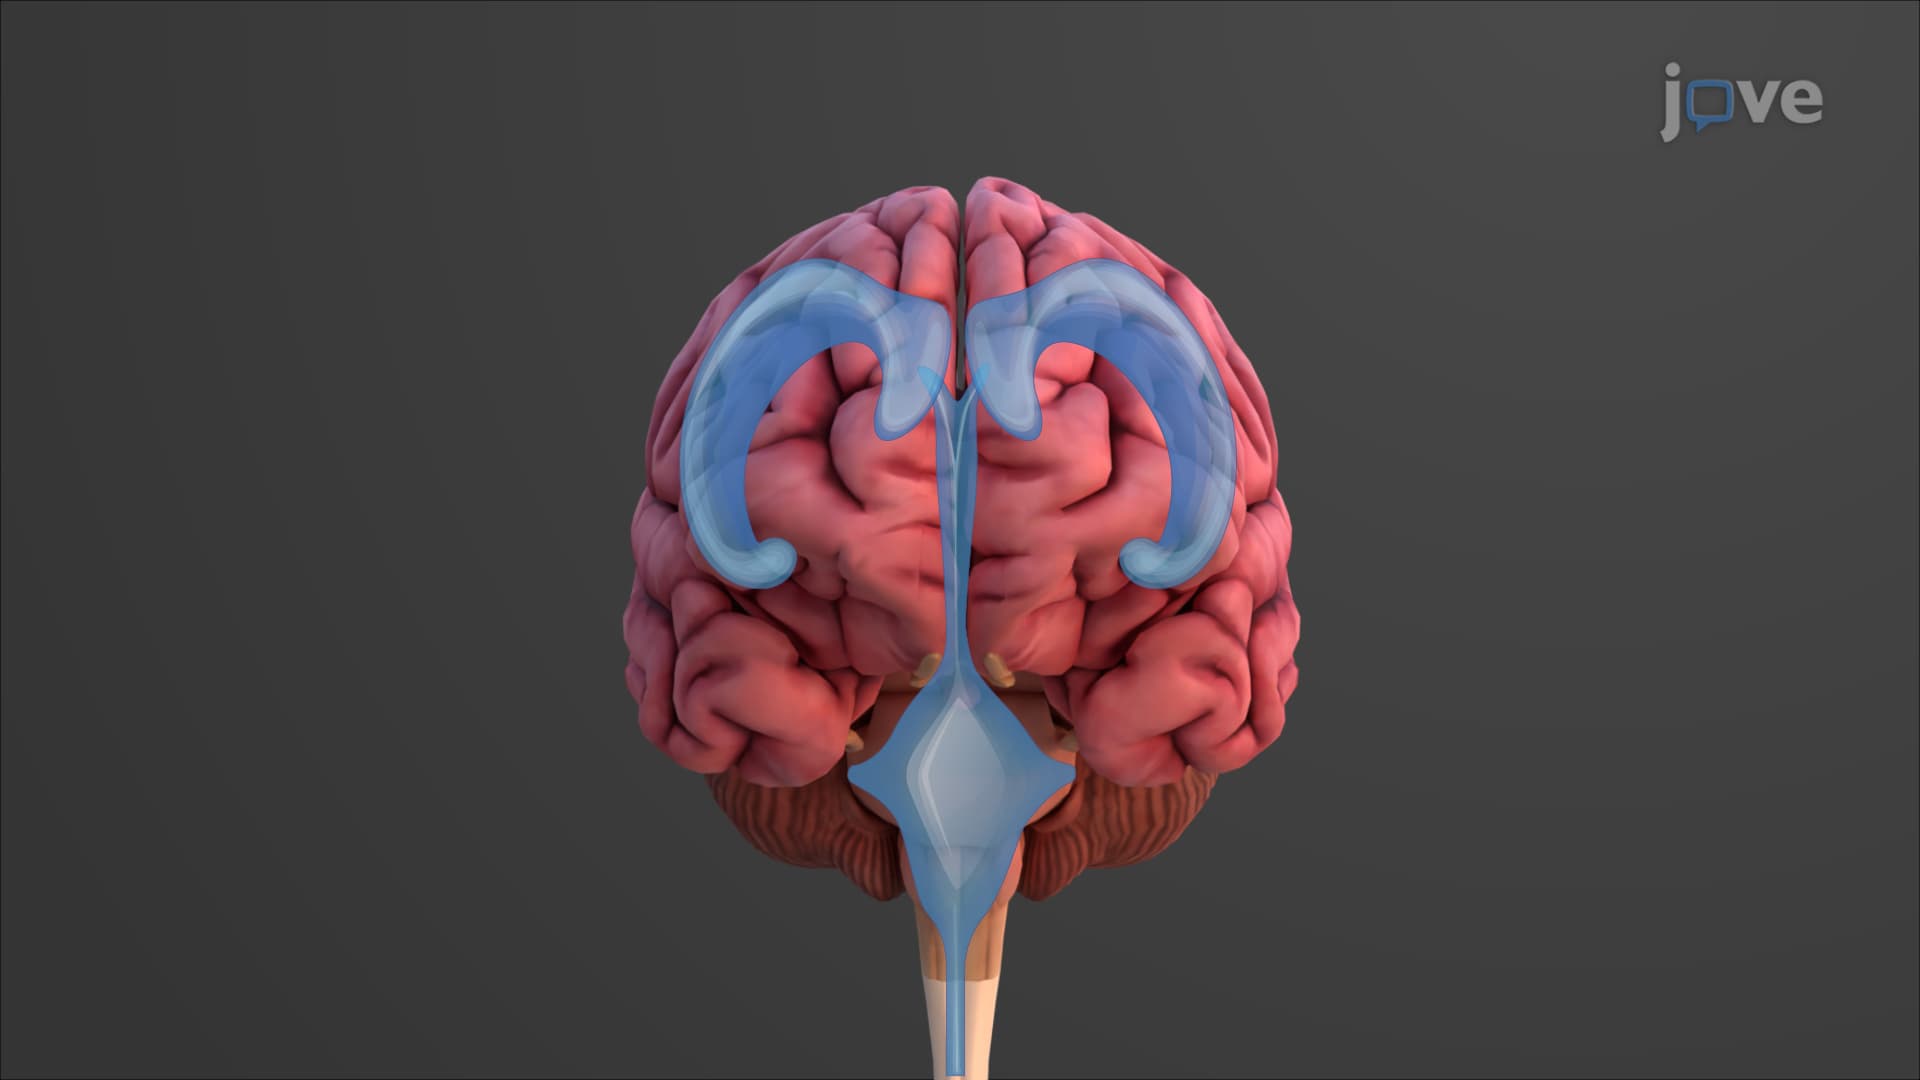
Anatomy of the Brain: Ventricles
 01:30
Pneumonia III: Complications and Assessment