Related Experiment Video
Updated: Oct 18, 2025
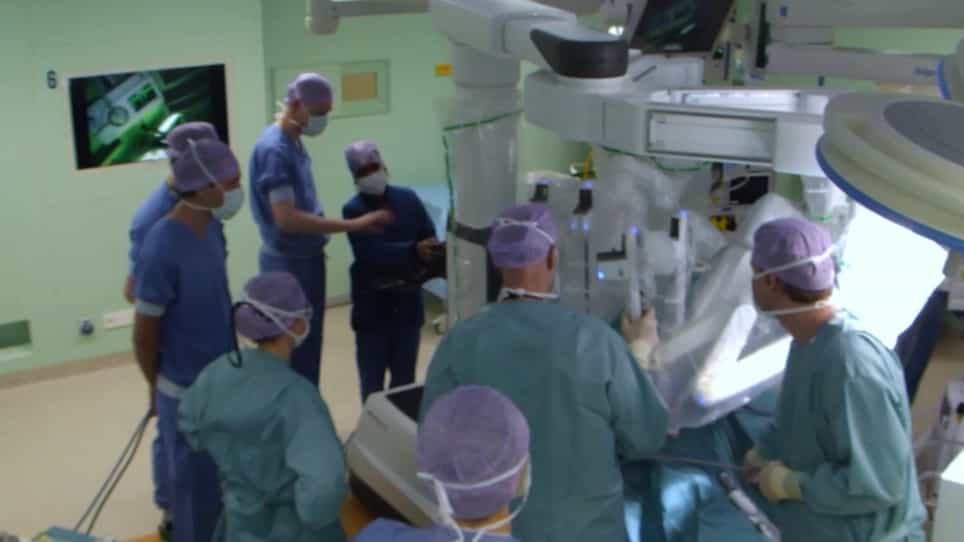

Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Challenge of coexisting type 2 diabetes mellitus and insulinoma: a case report
Joseph Singbo1, Michael Locketz2, Ian Louis Ross3
1Department of Medicine J47 Old Main Building Division of Endocrinology and Diabetes, Groote Schuur Hospital, University of Cape Town, Observatory, Cape Town, 7945, South Africa.

Background:
Insulinomas are rare clinical entities, but concurrent diabetes mellitus is even more uncommon, and the combination is easily missed. Recurrent hypoglycemia could be misconstrued as improved glycemic control. We present an unusual patient with type 2 diabetes and neuroglycopenia, with apparent improved glycemic control due to an insulinoma.
Case Presentation:
A 54-year-old mixed ancestry man with a positive family history of type 2 diabetes mellitus was diagnosed with type 2 diabetes mellitus and hypertension 8 years prior to admission. He presented with episodes of abnormal behavior and hypoglycemia. Inappropriately high insulin and C-peptide concentrations were identified at the time of hypoglycemia. Despite poor adherence to his diabetic treatment, he had no target organ damage relating to diabetes, and his hemoglobin A1c (HbA1c) was 5.3%. A diagnosis of insulinoma was made, and he was started on diazoxide, with endoscopic ultrasound revealing a possible lesion in the pancreatic tail measuring 12 mm × 12 mm. A fine-needle aspiration biopsy could not be performed due to overlying splenic arteries and the risk of vascular perforation. An intraoperative ultrasound confirmed a 15 mm × 10 mm tumor in the pancreatic tail, necessitating a partial pancreatectomy and splenectomy, which were curative. A well-differentiated intermediate grade 2 pancreatic neuroendocrine tumor producing insulin was confirmed on histopathology.
Conclusions:
Recurrent, progressive hypoglycemia and improved glycemic control in a diabetic, without an alternative explanation, may suggest an insulinoma. Insulinomas that exist with type 1 diabetes mellitus, particularly malignant insulinomas, must have escaped autoimmune attack through lack of autoantigen expression. Computed tomography on its own may be insufficiently sensitive for diagnosis of insulinomas, whereas endoscopic and intraoperative ultrasonography may improve the identification of the culprit lesion.


Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in...
 01:15
Diabetes: Symptoms, Diagnosis, and Complications
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...