Related Experiment Video
Updated: Oct 18, 2025
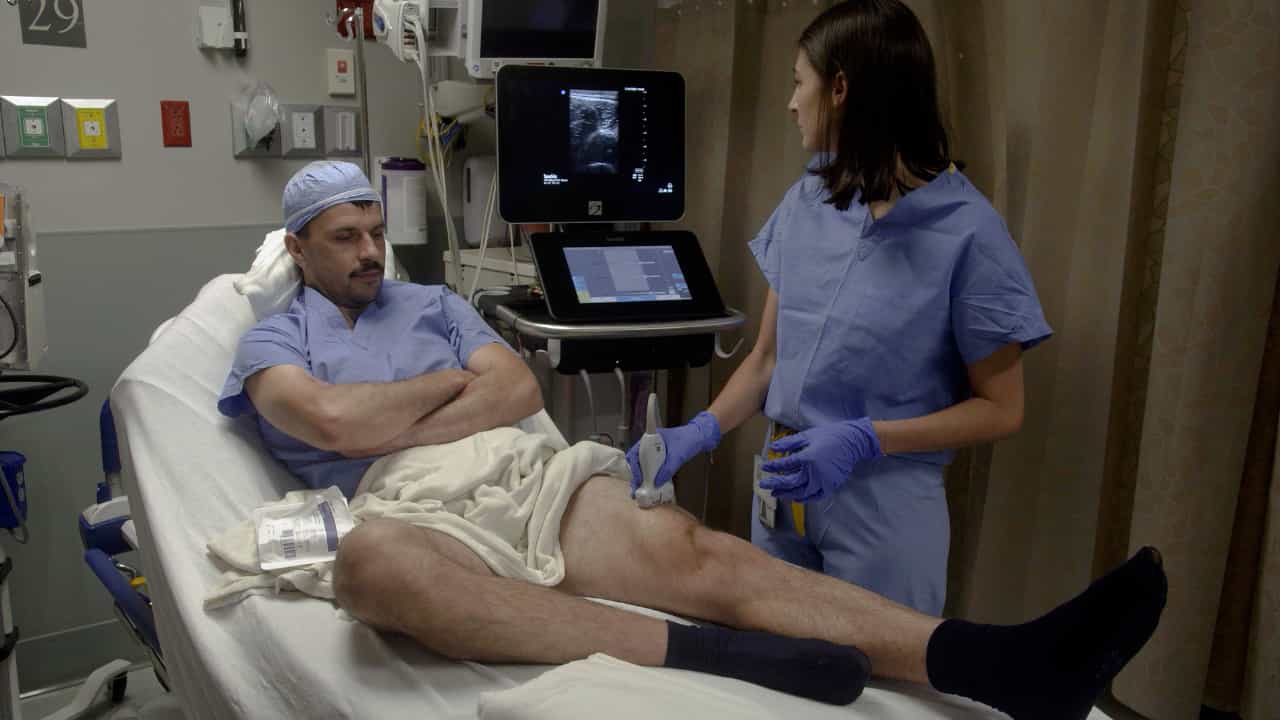

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Identification of Frailty Using a Claims-Based Frailty Index in the CoreValve Studies: Findings from the
Jordan B Strom1,2,3, Jiaman Xu2,3, Ariela R Orkaby3,4
1Department of Medicine Cardiovascular Division Beth Israel Deaconess Medical Center Boston MA.

Insights
Claims-based frailty indices (CFIs) in aortic valve disease patients identify individuals with worse health impairments and higher mortality risk. This retrospective method offers valuable prognostic information when in-person frailty assessments are unavailable.
Area of Science:
- Gerontology and Geriatric Medicine
- Cardiovascular Medicine
- Health Services Research
Background:
- The relationship between claims-based frailty indices (CFIs) and validated, in-person frailty assessments in aortic valve disease is not well understood.
- CFIs may offer a method for retrospective frailty ascertainment when direct measurement is not feasible.
Purpose of the Study:
- To evaluate the association between a claims-based frailty index (Johns Hopkins CFI) and clinical outcomes in patients undergoing aortic valve procedures.
- To determine if CFIs can identify patients with worse frailty status and predict adverse events.
Main Methods:
- Adults aged ≥65 years from the US CoreValve Studies were linked to Medicare inpatient claims (2011-2015).
- The Johns Hopkins CFI, based on the Fried index, was generated for each participant.
- Association between CFI tertiles and outcomes (mortality, bleeding, MACE, hospitalization) was analyzed.
Main Results:
- Higher CFI tertiles correlated with greater impairments in nutrition, disability, cognition, and self-rated health.
- One-year all-cause mortality significantly increased with higher CFI tertiles (HR 1.73 for highest vs. lowest tertile, P<0.001).
- Secondary outcomes, including bleeding, major adverse cardiovascular and cerebrovascular events (MACE), and hospitalization, were more frequent in higher CFI tertiles, independent of clinical risk scores.
Conclusions:
- A claims-based frailty index (CFI) effectively identifies patients with worse frailty, disability, and cognitive/nutritional deficits in aortic valve disease.
- Higher CFI scores are independently associated with increased risks of mortality, hospitalization, bleeding, and MACE.
- While not a substitute for in-person assessments, CFIs provide valid and prognostically relevant frailty information for retrospective analysis.
Abstract:
Background In aortic valve disease, the relationship between claims-based frailty indices (CFIs) and validated measures of frailty constructed from in-person assessments is unclear but may be relevant for retrospective ascertainment of frailty status when otherwise unmeasured. Methods and Results We linked adults aged ≥65 years in the US CoreValve Studies (linkage rate, 67%; mean age, 82.7±6.2 years, 43.1% women), to Medicare inpatient claims, 2011 to 2015. The Johns Hopkins CFI, validated on the basis of the Fried index, was generated for each study participant, and the association between CFI tertile and trial outcomes was evaluated as part of the EXTEND-FRAILTY substudy. Among 2357 participants (64.9% frail), higher CFI tertile was associated with greater impairments in nutrition, disability, cognition, and self-rated health. The primary outcome of all-cause mortality at 1 year occurred in 19.3%, 23.1%, and 31.3% of those in tertiles 1 to 3, respectively (tertile 2 versus 1: hazard ratio, 1.22; 95% CI, 0.98-1.51; P=0.07; tertile 3 versus 1: hazard ratio, 1.73; 95% CI, 1.41-2.12; P<0.001). Secondary outcomes (bleeding, major adverse cardiovascular and cerebrovascular events, and hospitalization) were more frequent with increasing CFI tertile and persisted despite adjustment for age, sex, New York Heart Association class, and Society of Thoracic Surgeons risk score. Conclusions In linked Medicare and CoreValve study data, a CFI based on the Fried index consistently identified individuals with worse impairments in frailty, disability, cognitive dysfunction, and nutrition and a higher risk of death, hospitalization, bleeding, and major adverse cardiovascular and cerebrovascular events, independent of age and risk category. While not a surrogate for validated metrics of frailty using in-person assessments, use of this CFI to ascertain frailty status among patients with aortic valve disease may be valid and prognostically relevant information when otherwise not measured.


Related Concept Videos
 01:27
Heart Failure I: Introduction
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:26
Heart Failure III: Clinical Manifestations
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:29
Heart Failure II: Pathophysiology
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age