Related Experiment Video
Updated: Oct 18, 2025
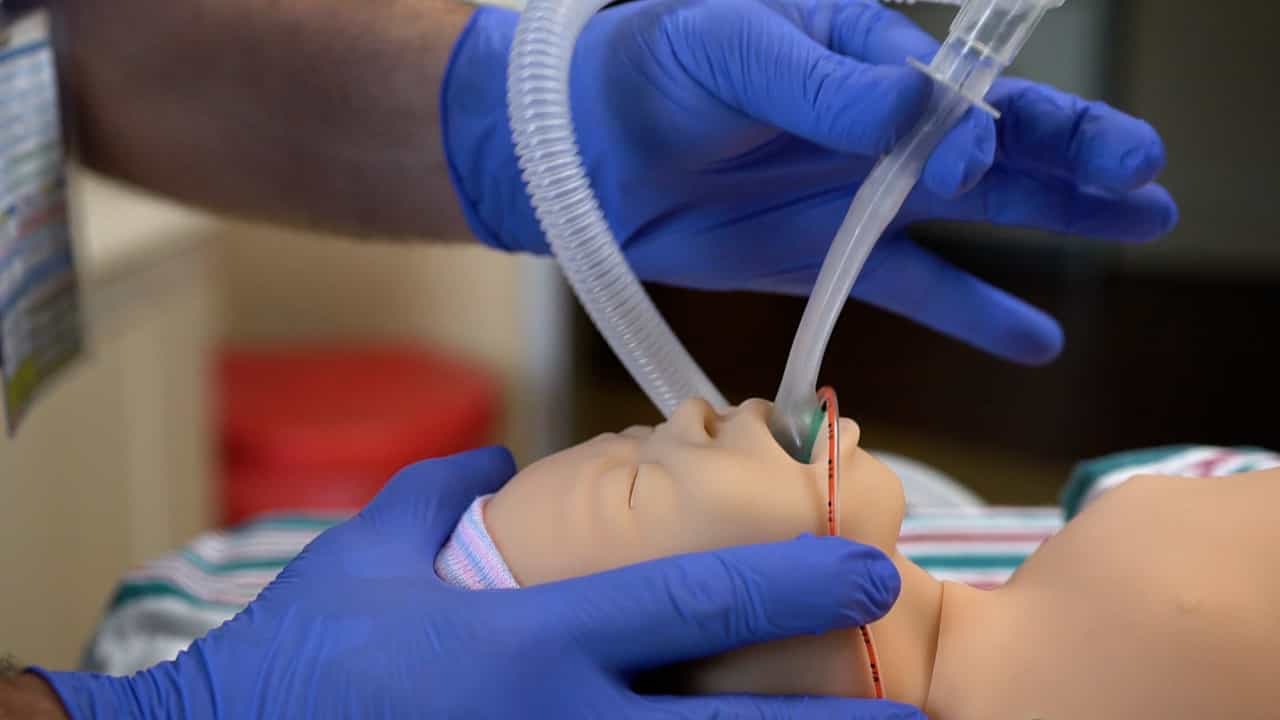

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Surfactant Administration Through Laryngeal or Supraglottic Airways
Scott O Guthrie1,2, Prem Fort3,4,2, Kari D Roberts5
1Department of Pediatrics, Division of Neonatology, Vanderbilt University School of Medicine, Nashville, TN.

Noninvasive ventilation is frequently used in the treatment of infants with respiratory distress syndrome. This practice is often effective in higher gestational age neonates, but can be difficult in those with lower gestational ages as surfactant deficiency can be severe. While noninvasive ventilation avoids the negative effects of intubation and ventilator-induced lung injury, failure of this mode of support does occur with relative frequency and is primarily caused by the poorly compliant, surfactant-deficient lung. Because of the potential problems associated with laryngoscopy and intubation, neonatologists have developed various methods to deliver surfactant in minimally invasive ways with the aim of improving the success of noninvasive ventilation. Methods of minimally invasive surfactant administration include various thin catheter techniques, aerosolization/nebulization, and the use of a laryngeal mask airway/supraglottic airway device. The clinician should recognize that currently the only US Food and Drug Administration-approved device to deliver surfactant is an endotracheal tube and all methods reviewed here are considered off-label use. This review will focus primarily on surfactant administration through laryngeal or supraglottic airways, providing a review of the history of this technique, animal and human trials, and comparison with other minimally invasive techniques. In addition, this review provides a step-by-step instruction guide on how to perform this procedure, including a multimedia tutorial to facilitate learning.
Noninvasive ventilation is frequently used in the treatment of infants with respiratory distress syndrome. This practice is often effective in higher gestational age neonates, but can be difficult in those with lower gestational ages as surfactant deficiency can be severe. While noninvasive ventilation avoids the negative effects of intubation and ventilator-induced lung injury, failure of this mode of support does occur with relative frequency and is primarily caused by the poorly compliant, surfactant-deficient lung. Because of the potential problems associated with laryngoscopy and intubation, neonatologists have developed various methods to deliver surfactant in minimally invasive ways with the aim of improving the success of noninvasive ventilation. Methods of minimally invasive surfactant administration include various thin catheter techniques, aerosolization/nebulization, and the use of a laryngeal mask airway/supraglottic airway device. The clinician should recognize that currently the only US Food and Drug Administration-approved device to deliver surfactant is an endotracheal tube and all methods reviewed here are considered off-label use. This review will focus primarily on surfactant administration through laryngeal or supraglottic airways, providing a review of the history of this technique, animal and human trials, and comparison with other minimally invasive techniques. In addition, this review provides a step-by-step instruction guide on how to perform this procedure, including a multimedia tutorial to facilitate learning.
More Related Videos

Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:05
Breathing
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:23
Inhaled Medications
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...