Related Experiment Video
Updated: Oct 18, 2025

Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Therapeutic Drug Monitoring of Vancomycin in Adult Patients with Methicillin-Resistant Staphylococcus aureus
Ryan Marko1, Julia Hajjar2, Vanessa Nzeribe3
1, PharmD, is with The Ottawa Hospital, Ottawa, Ontario.

Background:
Vancomycin remains widely used for methicillin-resistant Staphylococcus aureus (MRSA) infections; however, treatment failure rates up to 50% have been reported. At the authors' institution, monitoring of trough concentration is the standard of care for therapeutic drug monitoring of vancomycin. New guidelines support use of the ratio of 24-hour area under the concentration-time curve to minimum inhibitory concentration (AUC24/MIC) as the pharmacodynamic index most likely to predict outcomes in patients with MRSA-associated infections.
Objectives:
To determine the discordance rate between trough levels and AUC24/MIC values and how treatment failure and nephrotoxicity outcomes compare between those achieving and not achieving their pharmacodynamic targets.
Methods:
This retrospective cohort study involved patients with MRSA bacteremia or pneumonia admitted to the study hospital between March 1, 2014, and December 31, 2018, and treated with vancomycin. Data for trough concentrations were collected, and minimum concentrations (C min) were extrapolated. The AUC24/MIC values were determined using validated population pharmacokinetic models. The C min and AUC24/MIC values were characterized as below, within, or above pharmacodynamic targets (15-20 mg/L and 400-600, respectively). Discordance was defined as any instance where a patient's paired C min and AUC24/MIC values fell in different ranges (i.e., below, within, or above) relative to the target ranges. Predictors of treatment failure and nephrotoxicity were determined using logistic regression.
Results:
A total of 128 patients were included in the analyses. Of these, 73 (57%) received an initial vancomycin dose less than 15 mg/kg. The discordance rate between C min and AUC24/MIC values was 21% (27/128). Rates of treatment failure and nephrotoxicity were 34% (43/128) and 18% (23/128), respectively. No clinical variables were found to predict discordance. Logistic regression identified initiation of vancomycin after a positive culture result (odds ratio [OR] 4.41, 95% confidence interval [CI] 1.36-14.3) and achievement of target AUC24/MIC after 4 days (OR 3.48, 95% CI 1.39-8.70) as modifiable predictors of treatment failure.
Conclusions:
The relationship between vancomycin monitoring and outcome is likely confounded by inadequate empiric or initial dosing. Before any modification of practice with respect to vancomycin monitoring, empiric vancomycin dosing should be optimized.
Insights
Vancomycin trough levels and AUC24/MIC values showed 21% discordance in MRSA infections. Optimizing initial vancomycin dosing is crucial before altering monitoring practices to improve patient outcomes.
Area of Science:
- Pharmacology
- Infectious Diseases
- Clinical Pharmacy
Background:
- Vancomycin is a key treatment for MRSA infections, but high failure rates (up to 50%) necessitate optimized therapeutic drug monitoring.
- Current standard of care involves monitoring trough concentrations, while new guidelines suggest the 24-hour area under the concentration-time curve to minimum inhibitory concentration (AUC24/MIC) ratio is a better predictor of outcomes.
Purpose of the Study:
- To assess the discordance rate between vancomycin trough levels and AUC24/MIC values.
- To compare treatment failure and nephrotoxicity rates based on achieving pharmacodynamic targets.
Main Methods:
- Retrospective cohort study of 128 patients with MRSA bacteremia or pneumonia treated with vancomycin.
- Collected trough concentrations and extrapolated minimum concentrations (Cmin); determined AUC24/MIC using population pharmacokinetic models.
- Defined discordance as paired Cmin and AUC24/MIC values falling into different target ranges (below, within, or above).
Main Results:
- A 21% discordance rate was observed between Cmin and AUC24/MIC values.
- Treatment failure occurred in 34% of patients and nephrotoxicity in 18%.
- Initiation of vancomycin after a positive culture and achieving target AUC24/MIC after 4 days were modifiable predictors of treatment failure.
Conclusions:
- Inadequate empiric or initial vancomycin dosing may confound the relationship between monitoring strategies and patient outcomes.
- Optimization of empiric vancomycin dosing should be prioritized before any changes to current vancomycin monitoring practices are implemented.

Related Concept Videos
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:16
Therapeutic Drug Monitoring: Overview and Classification
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:20
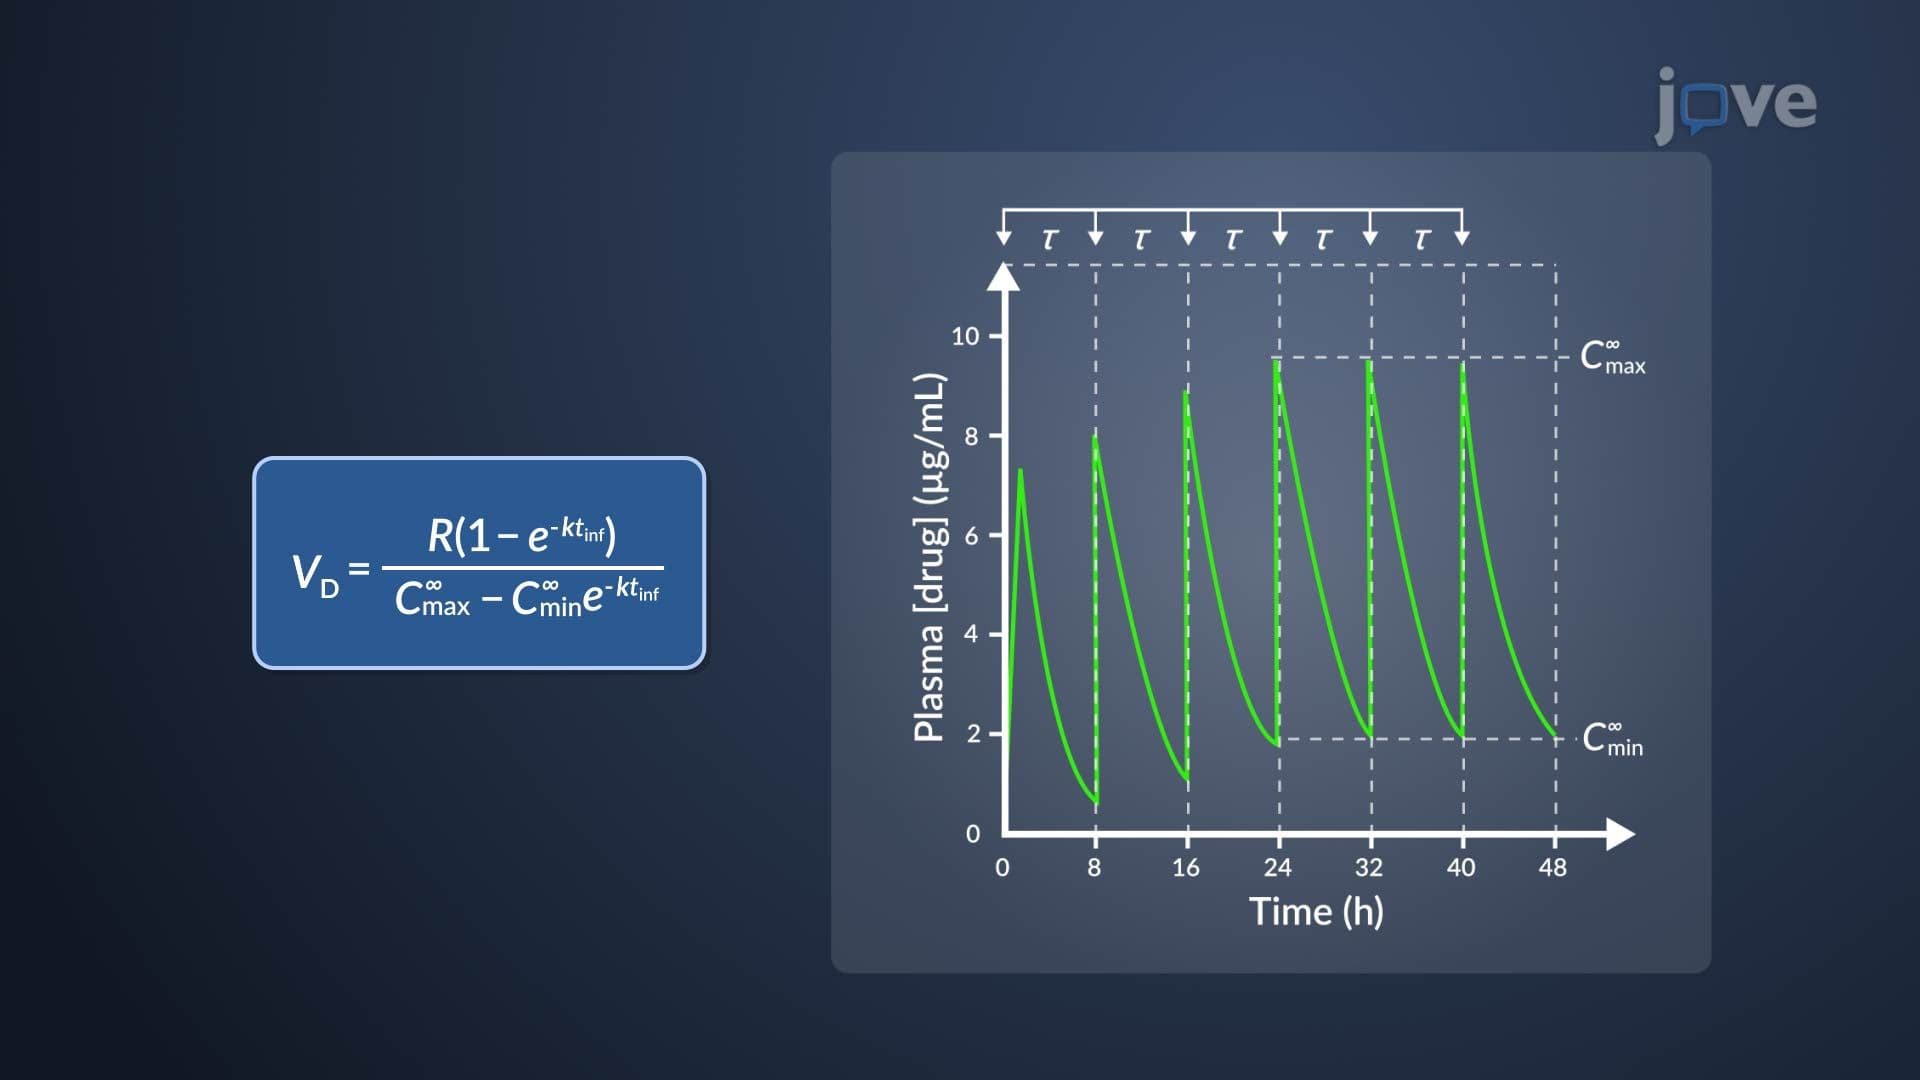
Estimation of k and VD of Aminoglycosides
 01:15
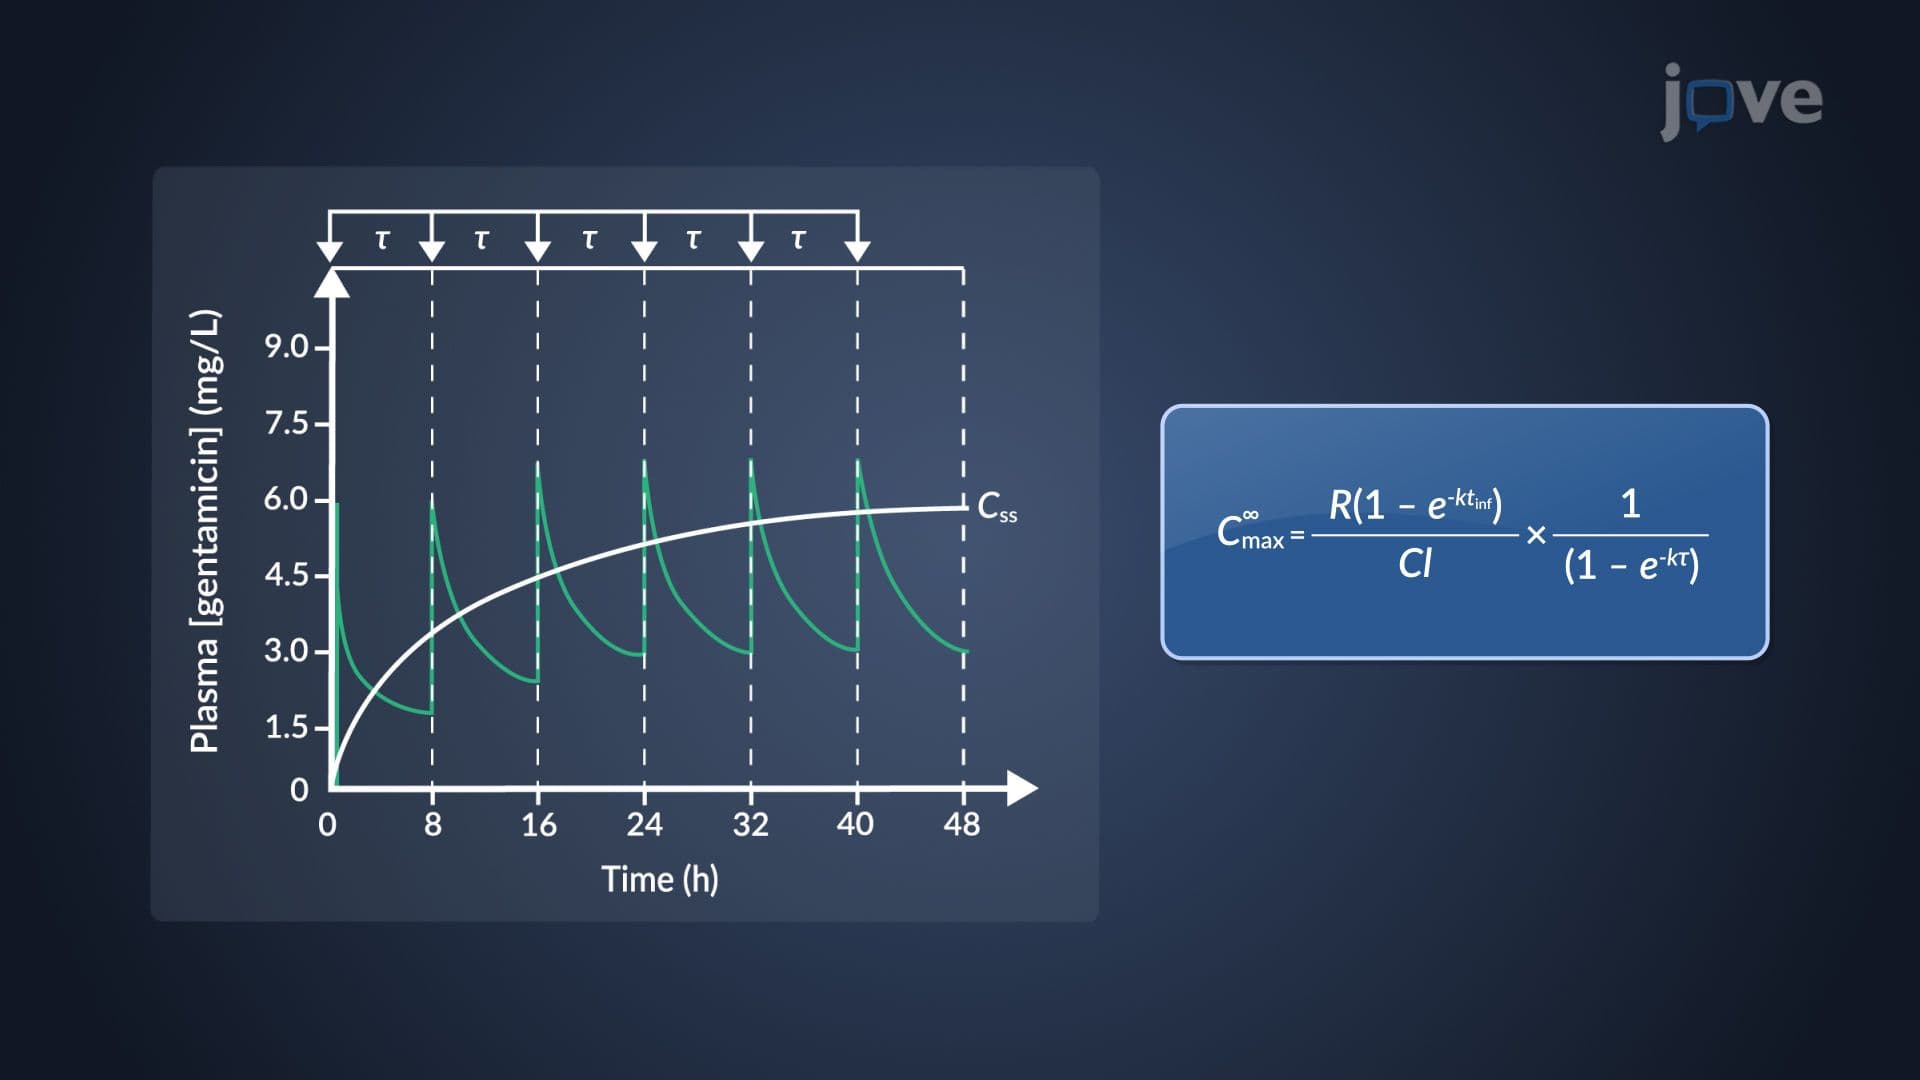
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:19
Pharmacovigilance
This process, termed pharmacovigilance, aims to detect, evaluate, and minimize harmful effects related to medication use. The data collection for pharmacovigilance depends on spontaneous reporting systems, where healthcare professionals or patients voluntarily report suspected ADRs.
In some cases, there...