Related Experiment Video
Updated: Oct 17, 2025


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Time Above All Else: Pharmacodynamic Analysis of β-Lactams in Critically Ill Patients
Katie B Landmesser1,2, Justin A Clark2, David S Burgess2
1Department of Pharmacy, University of Kentucky HealthCare, Lexington, Kentucky, USA.

Abstract:
β-Lactams are the most commonly used antibiotics in intensive care units (ICUs). As critically ill patients often experience pharmacokinetic aberrations, and rates of antimicrobial resistance vary between hospital settings, reliance on tertiary sources or package labeling to guide empiric dosing often results in suboptimal β-lactam exposure. The primary objective was to identify β-lactam regimens capable of achieving ≥90% cumulative fraction of response (CFR) against 7 Gram-negative pathogens within 4 ICUs at our institution. Unit-specific minimal inhibitory concentration (MIC) distribution data was used in combination with published pharmacokinetic parameters in critically ill patients to perform Monte Carlo simulations. The percentage of time for which the unbound concentration of antibiotic remained above the MIC (%ƒT > MIC) was used as the pharmacodynamic target: 70%ƒT >MIC for cefepime, 40%ƒT > MIC for meropenem, and 50%ƒT > MIC for piperacillin/tazobactam. Regimens were modeled to determine the likelihood of achieving ≥90% CFR. Overall, intermittently dosed cefepime, meropenem, and piperacillin/tazobactam failed to achieve ≥90% CFR for every organism. Cefepime 2 g intermittent bolus every 8 hours failed to achieve ≥90% CFR for Klebsiella pneumoniae or Enterobacter cloacae despite susceptibility rates exceeding 90%. Piperacillin/tazobactam 4.5 g prolonged infusion (PI) every 6 hours achieved <85% CFR for Pseudomonas aeruginosa and <50% CFR for Acinetobacter baumannii in every ICU. Meropenem 2 g PI every 8 hours and meropenem 2 g PI every 6 hours were the only regimens capable of achieving ≥90% CFR for P aeruginosa in all units. Use of Monte Carlo simulations, with incorporation of local MIC distribution data, provides a mechanism to effectively predict optimal agent and dose selection within specific hospital systems, thereby enhancing pharmacokinetic/pharmacodynamic optimization and improving clinical efficacy.
More Related Videos
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
 07:28
Metabolic Profiling to Determine Bactericidal or Bacteriostatic Effects of New Natural Products using Isothermal Microcalorimetry
Published on: October 29, 2020
Related Concept Videos
 01:20
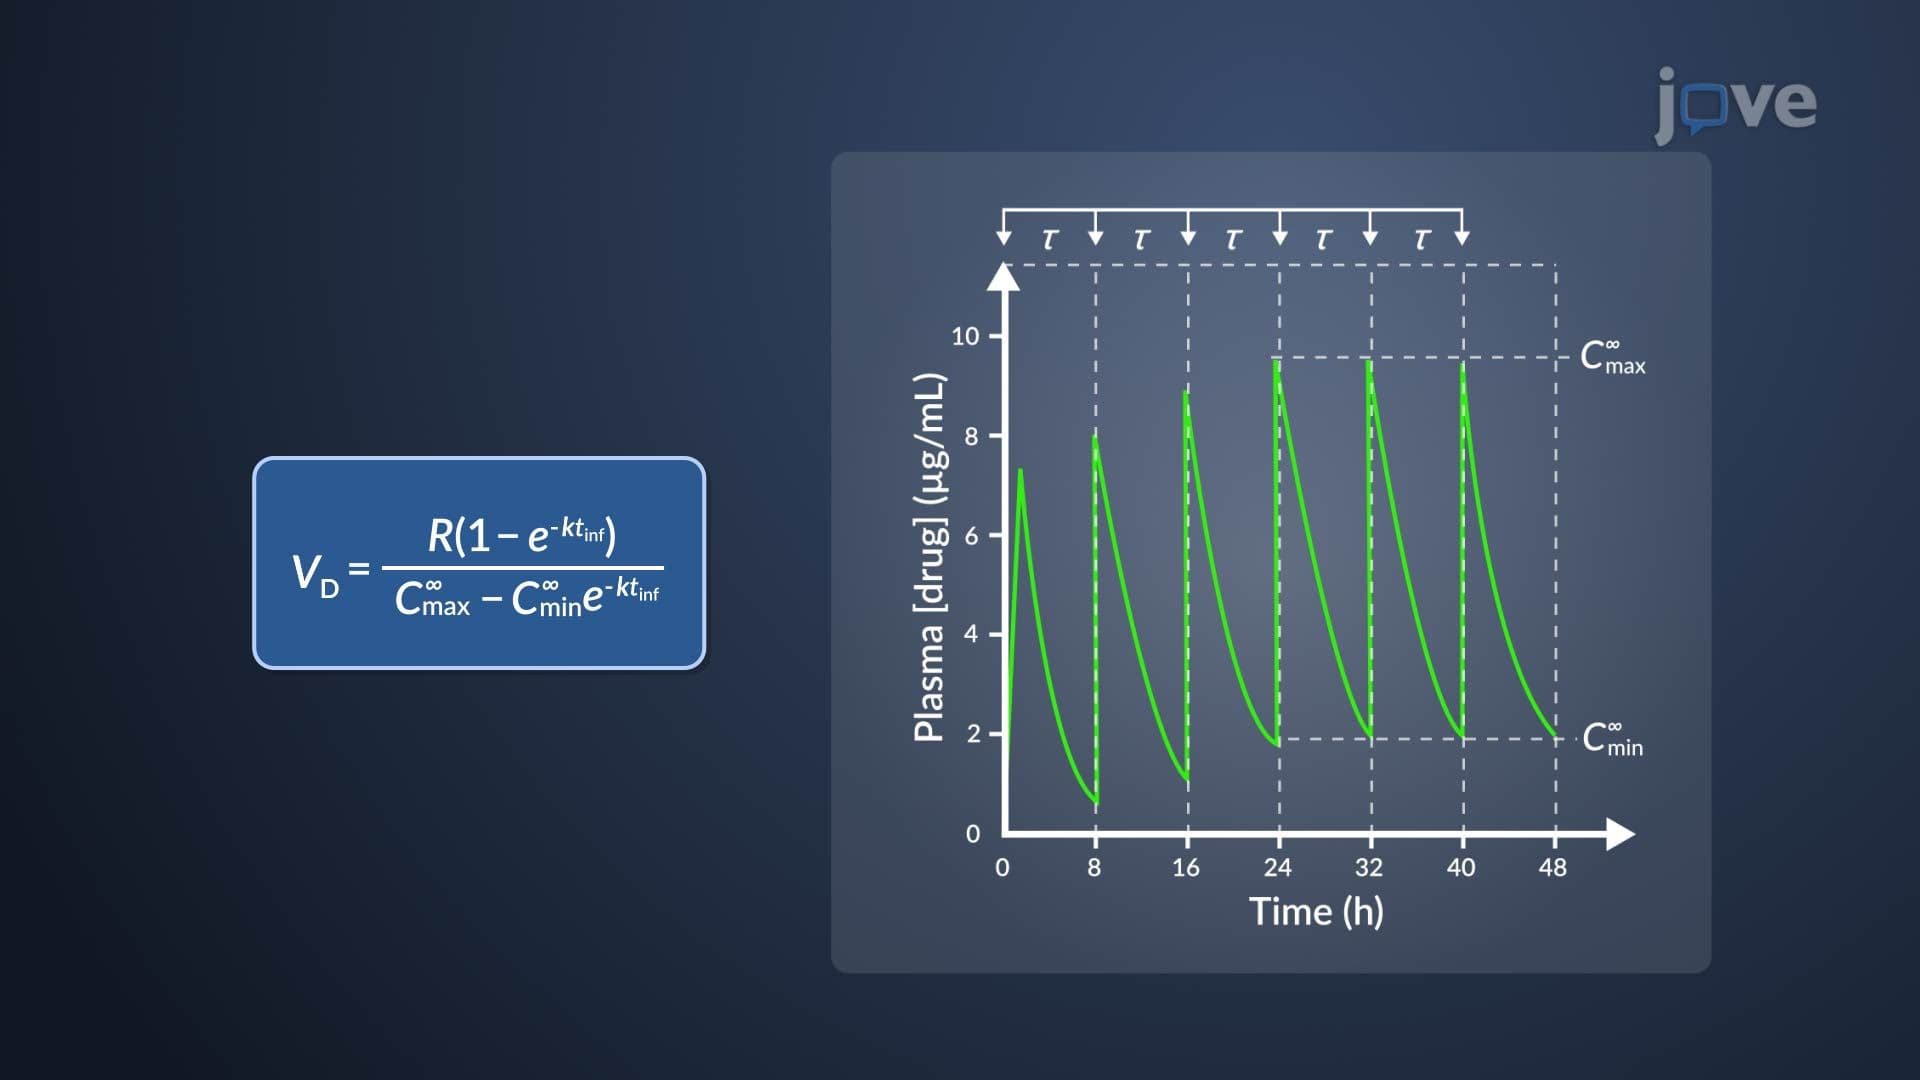
Estimation of k and VD of Aminoglycosides
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:20
Measurement of Bioavailability: Pharmacodynamic Methods