Jaundice in patients with COVID-19
Related Experiment Video
Updated: Oct 17, 2025
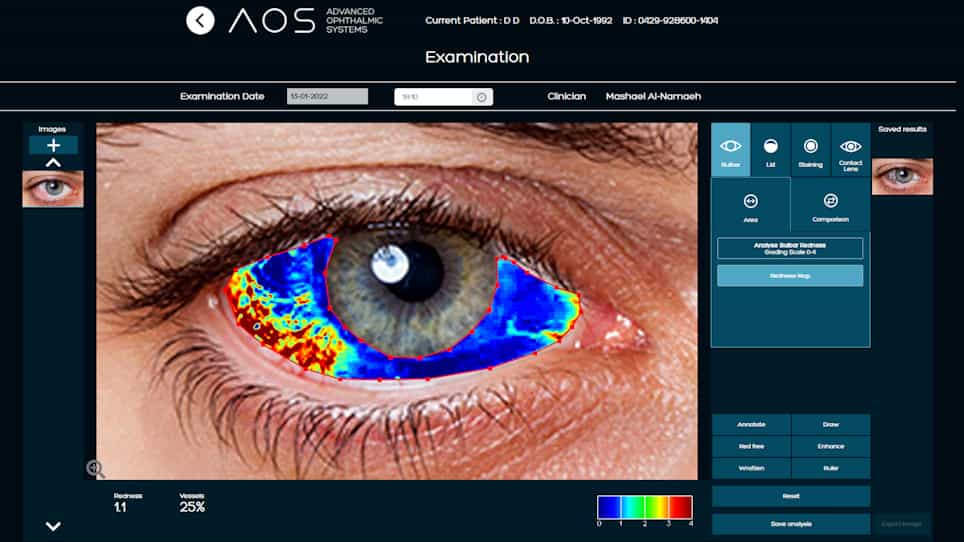
Comparing Objective Conjunctival Hyperemia Grading and the Ocular Surface Disease Index Score in Dry Eye Syndrome During COVID-19
Published on: May 25, 2022
Joshua M Bender1,2, Howard J Worman1,2
1Department of Medicine, Vagelos College of Physicians and Surgeons Columbia University New York New York USA.

Insights
Jaundice in patients with coronavirus disease 2019 (COVID-19) indicates a high mortality risk. Sepsis, inflammation, and hypoxic hepatitis are key causes of liver dysfunction leading to jaundice in these patients.
Area of Science:
- Hepatology
- Infectious Diseases
- Critical Care Medicine
Background:
- Liver injury is a known complication of COVID-19.
- The specific impact and causes of hepatic jaundice in COVID-19 patients remain under-investigated.
Purpose of the Study:
- To investigate the clinical outcomes and underlying causes of jaundice in hospitalized COVID-19 patients.
Main Methods:
- Retrospective analysis of 551 COVID-19 patients.
- Defined hepatic jaundice by serum bilirubin levels.
- Characterized liver injury patterns (cholestatic, mixed, hepatocellular).
Main Results:
- Jaundice (8.9%) was linked to significantly higher mortality (40.8%) and ICU admission (69.4%).
- Jaundiced patients exhibited more frequent fever, cytopenias, hypotension, hypoxemia, elevated creatinine, procalcitonin, and sepsis.
- Among those with elevated liver enzymes, cholestatic patterns predominated.
Conclusions:
- Hepatic jaundice is a critical indicator of poor prognosis in COVID-19.
- Sepsis, systemic inflammation, and hypoxic/ischemic hepatitis are primary drivers of liver dysfunction leading to jaundice in COVID-19.
Background And Aim:
While many studies have reported on liver injury in patients with coronavirus disease 2019 (COVID-19), none have specifically addressed the significance of hepatic jaundice. We aimed to determine the clinical consequences and etiologies of jaundice in patients with COVID-19.
Methods:
We retrospectively analyzed clinical features, laboratory abnormalities, and rates of survival and intensive care unit admission in 551 patients with COVID-19, hospitalized between 1 March 2020, and 31 May 2020 at a tertiary care academic medical center. Hepatic jaundice was defined as a serum total bilirubin concentration >2.5 mg/dL and a direct bilirubin concentration >0.3 mg/dL that was >25% of the total. Liver injury was characterized as cholestatic, mixed, or hepatocellular at the time of peak serum total bilirubin concentration by calculating the R factor.
Results:
Hepatic jaundice was present in 49 (8.9%) patients and associated with a mortality rate of 40.8% and intensive care unit admission rate of 69.4%, both significantly higher than for patients without jaundice. Jaundiced patients had an increased frequency of fever, leukopenia, leukocytosis, thrombocytopenia, hypotension, hypoxemia, elevated serum creatinine concentration, elevated serum procalcitonin concentration, and sepsis. Nine jaundiced patients had isolated hyperbilirubinemia. Of the 40 patients with abnormally elevated serum alanine aminotransferase or alkaline phosphatase activities, 62.5% had a cholestatic, 20.0% mixed, and 17.5% hepatocellular pattern of liver injury.
Conclusion:
Hepatic jaundice in patients with COVID-19 is associated with high mortality. The main etiologies of liver dysfunction leading to jaundice appear to be sepsis, severe systemic inflammation, and hypoxic/ischemic hepatitis.


Related Concept Videos
 01:14
Changes in Skin Color: Clinical Perspectives
Albinism
Albinism is a genetic disorder that affects (completely or partially) the coloring of skin, hair, and eyes. The defect is primarily...
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:24
Nephrotic Syndrome III : Nursing Management
 01:26
Nephrotic Syndrome II : Assessment and Medical Management