Related Experiment Video
Updated: Oct 17, 2025
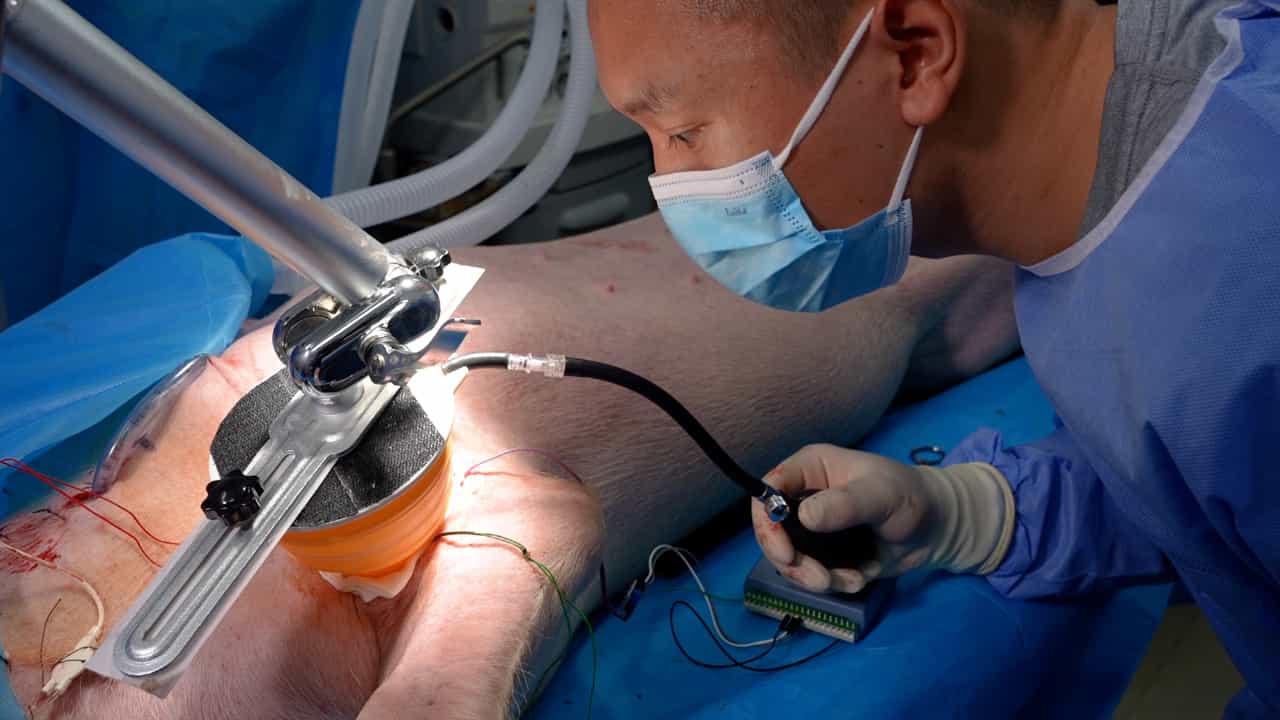
A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
Outcomes in high and low volume hospitals in patients with acute hematochezia in a cohort study
Naoki Ishii1, Naoyoshi Nagata2,3, Katsumasa Kobayashi4
1Division of Gastroenterology, Tokyo Shinagawa Hospital, 6-3-22 Higashi-Ooi, Shinagawa-ku, Tokyo, 140-8522, Japan. naoishi0328@gmail.com.

Outcomes of acute lower gastrointestinal bleeding have not been compared according to hospital capacity. We aimed to perform a propensity score-matched cohort study with path and mediation analyses for acute hematochezia patients. Hospitals were divided into high- versus low-volume hospitals for emergency medical services. Rebleeding and death within 30 days were compared. Computed tomography, early colonoscopy (colonoscopy performed within 24 h), and endoscopic therapies were included as mediators. A total of 2644 matched pairs were yielded. The rebleeding rate within 30 days was not significant between high- and low-volume hospitals (16% vs. 17%, P = 0.44). The mortality rate within 30 days was significantly higher in the high-volume cohort than in the low-volume cohort (1.7% vs. 0.8%, P = 0.003). Treatment at high-volume hospitals was not a significant factor for rebleeding (odds ratio [OR] = 0.91; 95% confidence interval [CI], 0.79-1.06; P = 0.23), but was significant for death within 30 days (OR = 2.03; 95% CI, 1.17-3.52; P = 0.012) on multivariate logistic regression after adjusting for patients' characteristics. Mediation effects were not observed, except for rebleeding within 30 days in high-volume hospitals through early colonoscopy. However, the direct effect of high-volume hospitals on rebleeding was not significant. High-volume hospitals did not improve the outcomes of acute hematochezia patients.
Outcomes of acute lower gastrointestinal bleeding have not been compared according to hospital capacity. We aimed to perform a propensity score-matched cohort study with path and mediation analyses for acute hematochezia patients. Hospitals were divided into high- versus low-volume hospitals for emergency medical services. Rebleeding and death within 30 days were compared. Computed tomography, early colonoscopy (colonoscopy performed within 24 h), and endoscopic therapies were included as mediators. A total of 2644 matched pairs were yielded. The rebleeding rate within 30 days was not significant between high- and low-volume hospitals (16% vs. 17%, P = 0.44). The mortality rate within 30 days was significantly higher in the high-volume cohort than in the low-volume cohort (1.7% vs. 0.8%, P = 0.003). Treatment at high-volume hospitals was not a significant factor for rebleeding (odds ratio [OR] = 0.91; 95% confidence interval [CI], 0.79-1.06; P = 0.23), but was significant for death within 30 days (OR = 2.03; 95% CI, 1.17-3.52; P = 0.012) on multivariate logistic regression after adjusting for patients' characteristics. Mediation effects were not observed, except for rebleeding within 30 days in high-volume hospitals through early colonoscopy. However, the direct effect of high-volume hospitals on rebleeding was not significant. High-volume hospitals did not improve the outcomes of acute hematochezia patients.


Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management