Related Experiment Video
Updated: Oct 16, 2025

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Decreased Global Myocardial Work Efficiency Correlates with Coronary Vasculopathy in Pediatric Heart Transplant
Sarah Pradhan1, Anna Mullikin1, Huaiyu Zang2
1The Heart Institute, Cincinnati Children's Hospital Medical Center, 3333 Burnet Avenue, Cincinnati, OH, 45229, USA.

Insights
Non-invasive global myocardial work efficiency (GWE) is decreased in pediatric heart transplant recipients with cardiac allograft vasculopathy (CAV). This finding suggests GWE may serve as a promising, non-invasive diagnostic tool for CAV.
Area of Science:
- Cardiology
- Pediatric Cardiology
- Transplant Medicine
Background:
- Cardiac allograft vasculopathy (CAV) is a major cause of late graft failure after heart transplantation.
- Coronary angiography, the current standard for CAV diagnosis, is invasive and carries risks.
- Non-invasive assessment of myocardial function, such as left ventricle global myocardial work (GMW) indices, has not been evaluated for CAV detection.
Purpose of the Study:
- To investigate the correlation between non-invasively derived left ventricle global myocardial work (GMW) indices and the presence of cardiac allograft vasculopathy (CAV) in pediatric heart transplant recipients.
- To evaluate the potential of GMW indices as a non-invasive diagnostic tool for CAV.
Main Methods:
- Prospective enrollment of 24 pediatric heart transplant patients and 24 age-matched healthy controls.
- Echocardiograms were performed, and left ventricle global myocardial work (GMW) indices, including global work efficiency (GWE), were derived using speckle-tracking echocardiography.
- Transplant patients underwent cardiac catheterization with coronary angiography to confirm the presence or absence of CAV.
Main Results:
- Patients with CAV exhibited significantly decreased global work efficiency (GWE) compared to those without CAV.
- Both global work index and GWE were significantly lower in heart transplant recipients (with and without CAV) compared to healthy controls.
- Left ventricle global longitudinal strain (GLS) and ejection fraction did not differ significantly between the groups.
- A negative correlation was observed between GWE and the presence of CAV (r = -0.44).
Conclusions:
- Decreased global work efficiency (GWE) is associated with the presence of cardiac allograft vasculopathy (CAV) in pediatric heart transplant recipients.
- GWE shows potential as a non-invasive biomarker for detecting CAV, offering an alternative to invasive coronary angiography.
- Further research is warranted to validate GMW indices as a routine diagnostic tool for CAV in this population.
Abstract:
Coronary angiography remains the standard for diagnosis of cardiac transplant vasculopathy (CAV), but it is invasive. Non-invasively derived left ventricle (LV) global myocardial work (GMW) indices have not been evaluated. We aimed to assess for correlations between LV GMW and the presence of CAV in a pediatric population. 24 heart transplant patients and 24 normal controls were prospectively enrolled. Patients were age-matched into groups with: orthotopic heart transplant and CAV (OHT-CAV; 6 patients, 33% male, mean age 13.5 years [SD 4.2]), orthotopic heart transplant without CAV (OHT; 18 patients, 67% male, mean age 11.1 years [SD 4.8]), and normal healthy controls (42% male, mean age 12.8 years [SD 5.0]). Transplant patients underwent cardiac catheterization with coronary angiography within 3 months of echocardiogram. Post-processing of echocardiograms with speckle-tracking echocardiography and derivation of GMW indices was performed. OHT-CAV patients had decreased global work efficiency (GWE) compared to OHT (mean difference = 7.01 [1.76, 12.25], adjusted p < 0.01). LV global longitudinal strain (GLS) and LV ejection fraction were not different between groups. Both global work index and GWE were decreased in OHT-CAV and OHT when compared to normal controls (OHT-CAV 1311.23 mmHg% vs OHT 1426.22 mmHg% vs controls 1802.81 mmHg%, adjusted p < 0.01; OHT-CAV 83.87% vs. OHT 90.87% vs. controls 95.41%, adjusted p < 0.01). GWE correlated negatively with the presence of CAV (r = - 0.44 [- 0.72, - 0.05]). This pilot study demonstrates decreased GWE correlates with pediatric CAV. This supports the need for further investigation of this promising diagnostic tool.
More Related Videos
 08:49
Author Spotlight: Enhancing Graft Viability Assessment Through Quantitative Metrics and Innovative Reservoir Systems
Published on: August 2, 2024
 08:21
Functional Assessment of the Donor Heart During Ex Situ Perfusion: Insights from Pressure-Volume Loops and Surface Echocardiography
Published on: October 11, 2022
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:29
Pathophysiology of Cardiac Performance
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:19
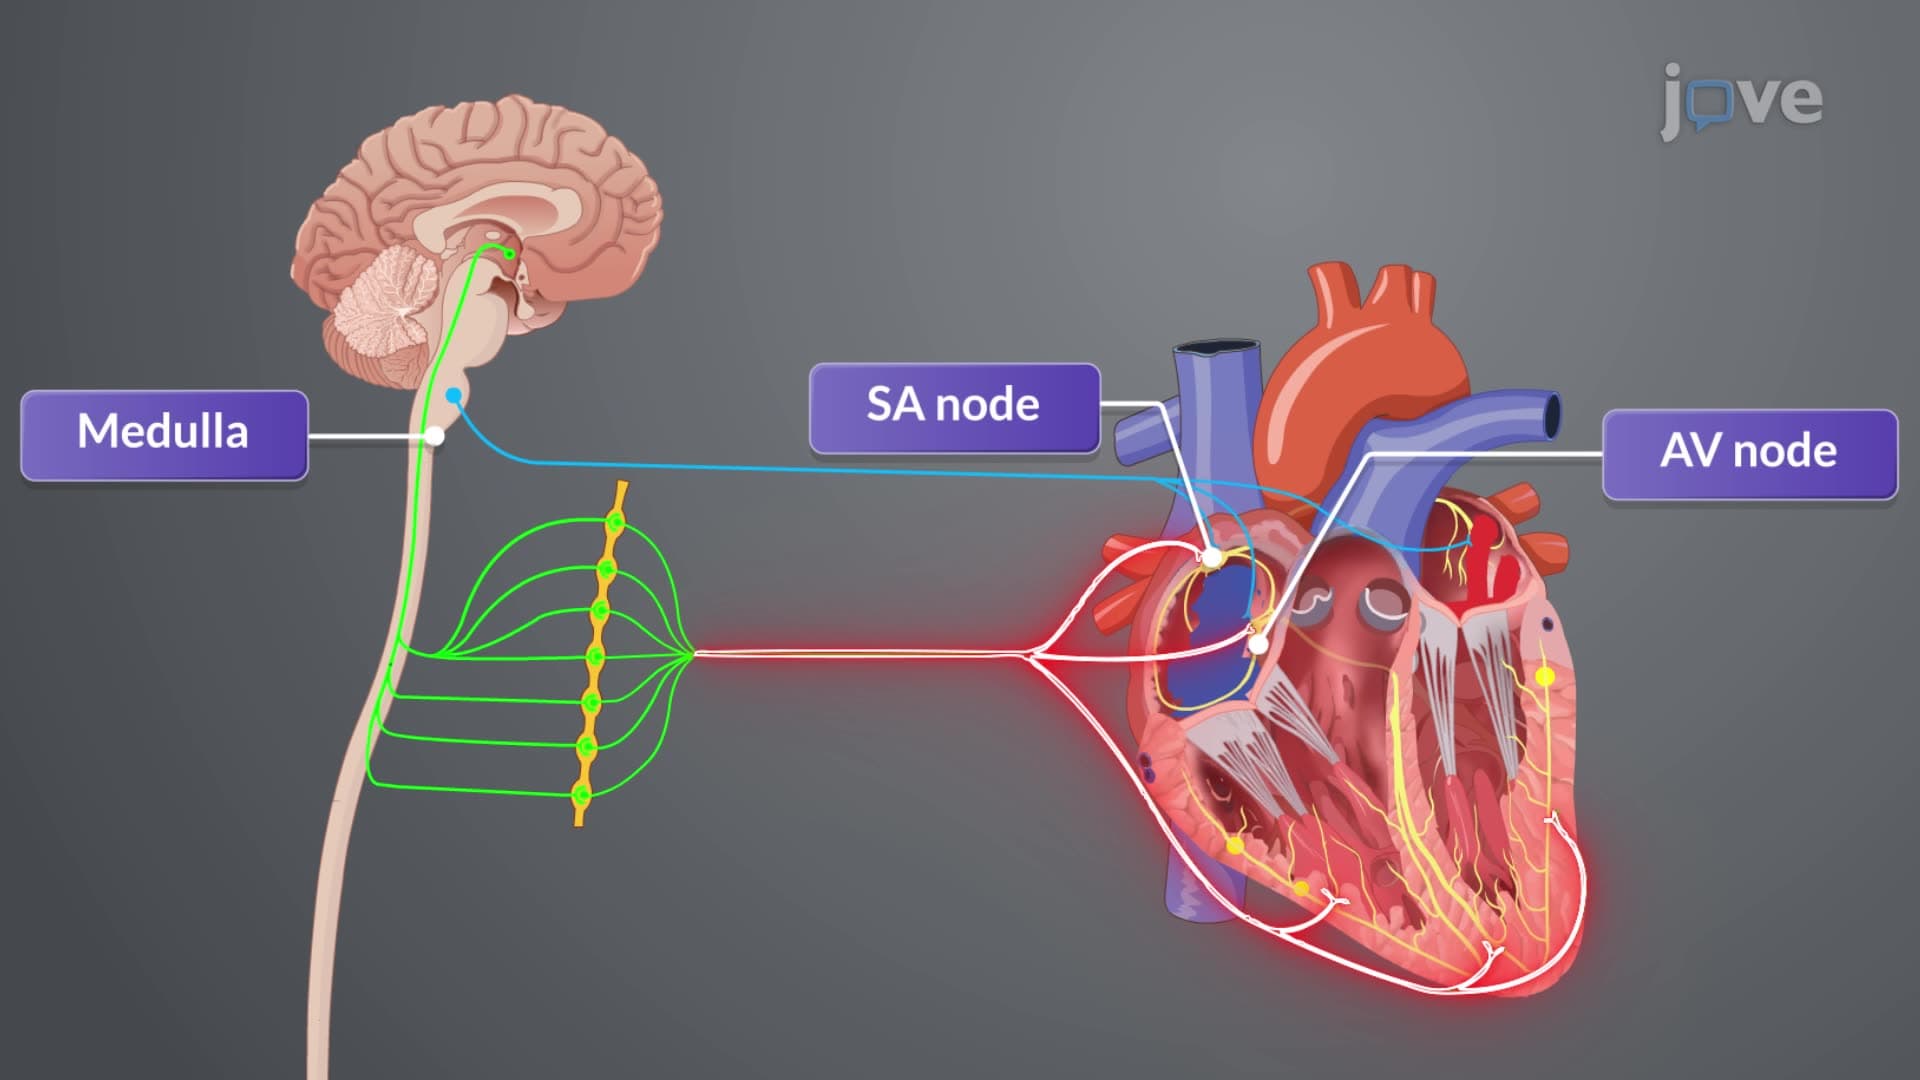
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...