Related Experiment Video
Updated: Oct 16, 2025
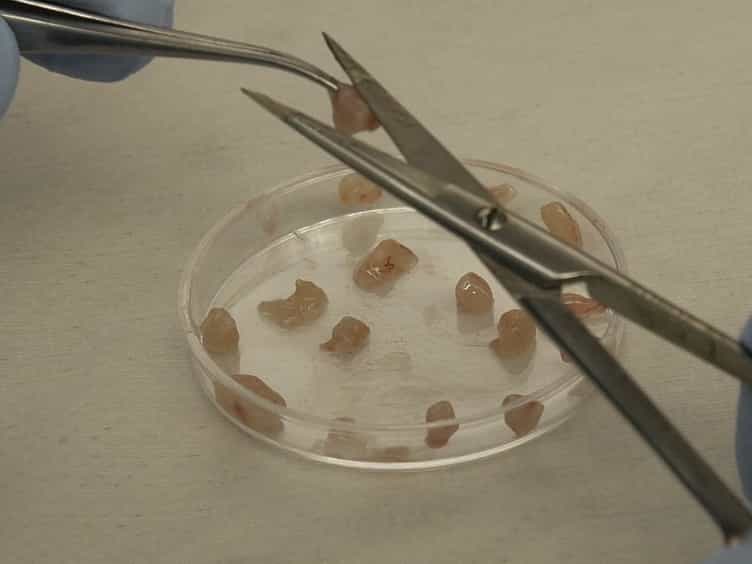

Development and Maintenance of a Preclinical Patient Derived Tumor Xenograft Model for the Investigation of Novel Anti-Cancer Therapies
Published on: September 30, 2016
Retrospective Comparative Analysis of KRAS G12C vs. Other KRAS Mutations in mCRC Patients Treated With First-Line
Riccardo Giampieri1,2, Alessio Lupi1, Pina Ziranu3
1Clinica Oncologica-Dipartimento Scienze Cliniche e Molecolari-Università Politecnica delle Marche, Ancona, Italy.

Background:
KRAS mutations in metastatic colorectal cancer (mCRC) define a subset of tumors that have primary resistance to anti-EGFR-based therapy. Data concerning whether different KRAS mutations may also have a prognostic value are lacking. Furthermore, novel KRAS G12C inhibitors are currently in development. The aim of our analysis was to compare response rates in patients treated with first-line chemotherapy doublet + Bevacizumab among different KRAS variants. Secondary end-points were progression free survival (PFS) and overall survival (OS).
Methods:
Patients with KRAS mutated mCRC treated with either FOLFIRI/FOLFOX/XELOX + Bevacizumab were eligible for enrollment. Patients whose tumor harbored NRAS mutations or that coexpressed also BRAF mutations were excluded from this retrospective analysis. Patients' individual data were collected from patients' records. Propensity score matching (nearest method, 1:2 ratio) was used to define the two different groups of patients for comparison (KRAS G12C mutated vs other KRAS variants). Eastern Cooperative Oncology Group Performance Status (ECOG PS), sex, metastatic site of involvement, synchronous vs metachronous metastatic disease, tumor sidedness, mucinous histology, primary tumor surgery, more than two lines of treatment for metastatic disease, and radical surgery of metastases were used as matching factors. Response rate (RR) was calculated by RECIST 1.1 criteria. Both progression free-survival and overall survival were calculated by Kaplan-Meier method. Categorical variables were compared by Fisher exact test for binomial variables and by chi-square test for all other instances. The level of statistical significance p was set at 0.05 for all tests.
Results:
A total of 120 patients were assessed in the final analysis. Out of the 120 patients, 15 (12%) were KRAS G12C mutated. In the whole cohort of patients, 59/120 (49%) had partial response (PR), 42/120 (35%) had stable disease (SD), and 19/120 (16%) had progressive disease (PD) as the best response. In KRAS G12C patients, 4/15 (27%) had PR, 6/15 (40%) had SD, and the remaining 5/15 (33%) had PD as the best response. In patients with other KRAS mutations, 55/105 (52%) had PR, 37/105 (35%) had SD, and the remaining 13/105 (12%) had PD as the best response. The difference in RR between the two groups of patients was statistically significant (p=0.017). On the other hand, no difference in PFS (p=0.76) and OS (p=0.56) was observed. After matching procedures, the difference in response rates between KRAS G12C mutated patients vs the matched cohort of patients with other KRAS mutations remained statistically significant (p=0.016). KRAS G12C mutations were not associated with differences in sites of metastatic involvement, sex, and ECOG PS. On the other hand, synchronous vs metachronous metastatic disease (p=0.039), age > 75 years (p=0.043), and mucinous histology (p=0.008) were more frequent in G12C mutated tumors.
Conclusions:
In our cohort of patients, it was observed that KRAS G12C mutations are associated with worse response rates compared to other KRAS variants when treated with standard chemotherapy doublet + Bevacizumab. On the other hand, both PFS and OS were not significantly different. Based on these findings, we believe that new treatment options focused on KRAS G12C inhibition should be tested mainly in first-line setting and in addition to standard chemotherapy doublet + Bevacizumab for mCRC patients, as they might "fill the gap" in response rates that was seen in our study.
Insights
Metastatic colorectal cancer (mCRC) patients with KRAS G12C mutations showed worse response rates to chemotherapy plus Bevacizumab compared to other KRAS variants. Progression-free survival and overall survival did not differ significantly between groups.
Area of Science:
- Oncology
- Molecular Biology
- Genetics
Background:
- KRAS mutations in metastatic colorectal cancer (mCRC) are linked to resistance to anti-EGFR therapy.
- Limited data exists on the prognostic value of different KRAS mutations.
- Novel KRAS G12C inhibitors are under development.
Purpose of the Study:
- To compare response rates in mCRC patients receiving first-line chemotherapy doublet plus Bevacizumab across different KRAS variants.
- To evaluate progression-free survival (PFS) and overall survival (OS) as secondary endpoints.
Main Methods:
- Retrospective analysis of 120 mCRC patients treated with chemotherapy (FOLFIRI/FOLFOX/XELOX) + Bevacizumab.
- Exclusion of patients with NRAS mutations or coexpressed BRAF mutations.
- Propensity score matching (1:2 ratio) to compare KRAS G12C mutated patients with other KRAS variants, controlling for clinical factors.
Main Results:
- KRAS G12C mutations (12%) were associated with significantly lower response rates (27% PR) compared to other KRAS variants (52% PR) (p=0.016).
- No significant differences were observed in progression-free survival (PFS) or overall survival (OS) between the groups.
- Synchronous metastasis, age >75 years, and mucinous histology were more frequent in KRAS G12C mutated tumors.
Conclusions:
- KRAS G12C mutations correlate with poorer response rates to first-line chemotherapy doublet + Bevacizumab in mCRC.
- PFS and OS were not significantly impacted by KRAS G12C status in this cohort.
- Targeted KRAS G12C inhibitors, potentially combined with standard chemotherapy, warrant investigation in the first-line setting for mCRC.


Related Concept Videos
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 01:21
Cancer Survival Analysis