Related Experiment Video
Updated: Oct 16, 2025
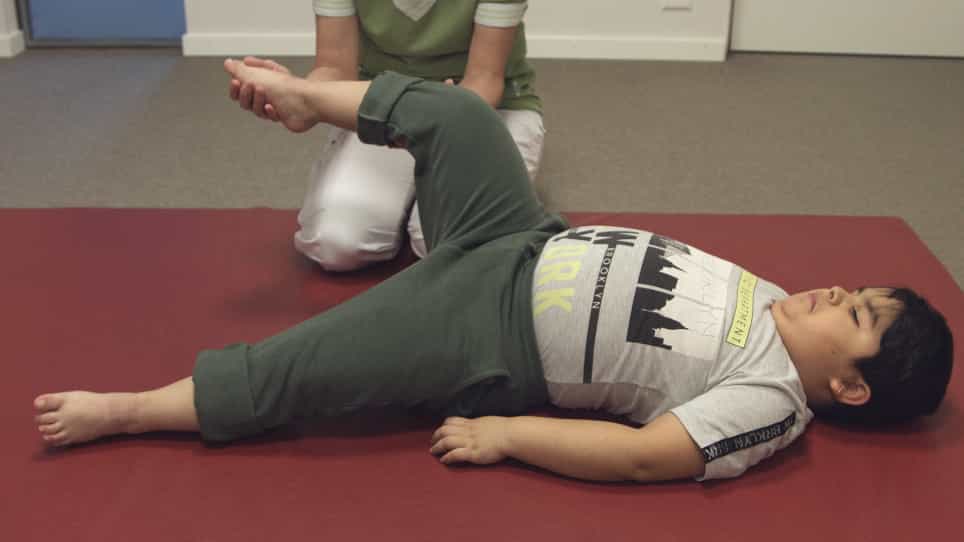

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Natural History of Facioscapulohumeral Dystrophy in Children: A 2-Year Follow-up
Jildou N Dijkstra1, Rianne J M Goselink1, Nens van Alfen1
1From the Departments of Neurology (J.N.D., N.v.A., B.G.M.v.E., N.C.V.) and Rehabilitation (I.J.M.d.G., M.P.), Donders Centre of Neuroscience, Department of Pediatric Neurology (J.N.D., C.E.E.), Amalia Children's Hospital, and Department of Ophthalmology (T.T.), Radboud University Medical Centre, Nijmegen, the Netherlands; Department of Neurology (R.J.M.G.), Jönköping, Region Jönköping County, and Department of Biomedical and Clinical Sciences (R.J.M.G.), Linköping University, Linköping, Sweden; and Department of Clinical Genetics (N.v.d.S.), Leiden University Medical Centre, the Netherlands.

Insights
Facioscapulohumeral dystrophy (FSHD) in children progresses slowly but varies. Key indicators for monitoring FSHD progression include clinical scores and muscle ultrasonography, crucial for future treatment trials.
Area of Science:
- Neurology
- Genetics
- Pediatrics
Background:
- Limited data exists on the natural history of facioscapulohumeral dystrophy (FSHD) in children.
- Understanding childhood FSHD progression is vital for patient care and clinical trial readiness.
Purpose of the Study:
- To describe the disease course of FSHD in children.
- To identify reliable outcome measures for childhood FSHD progression.
Main Methods:
- Prospective cohort study of 20 children with genetically confirmed FSHD (ages 2-17).
- Assessed muscle functioning, imaging, and quality of life over 2 years.
- Utilized the 6-minute walk test and muscle ultrasonography.
Main Results:
- Slowly progressive FSHD with variable rates; mean FSHD clinical score increased (p=0.003).
- Facial weakness increased from 16/20 to 19/20 children; trapezius and deltoid muscles most affected.
- Functional capacity improved; pain, fatigue, and decreased quality of life increased; muscle echogenicity progressed.
Conclusions:
- Childhood FSHD has a slowly progressive yet variable course.
- FSHD clinical score and muscle ultrasonography are promising outcome measures.
- Pain, fatigue, and quality of life impact require management; data aids counseling and trial design.
Background And Objectives:
Data on the natural history of facioscapulohumeral dystrophy (FSHD) in childhood are limited and critical for improved patient care and clinical trial readiness. Our objective was to describe the disease course of FSHD in children.
Methods:
We performed a nationwide, single-center, prospective cohort study of FSHD in childhood assessing muscle functioning, imaging, and quality of life over 2 years of follow-up.
Results:
We included 20 children with genetically confirmed FSHD who were 2 to 17 years of age. Overall, symptoms were slowly progressive, and the mean FSHD clinical score increased from 2.1 to 2.8 (p = 0.003). The rate of progression was highly variable. At baseline, 16 of 20 symptomatic children had facial weakness; after 2 years, facial weakness was observed in 19 of 20 children. Muscle strength did not change between baseline and follow-up. The most frequently and most severely affected muscles were the trapezius and deltoid. The functional exercise capacity, measured with the 6-minute walk test, improved. Systemic features were infrequent and nonprogressive. Weakness-associated complications such as lumbar hyperlordosis and dysarthria were common, and their prevalence increased during follow-up. Pain and fatigue were frequent complaints in children, and their prevalence also increased during follow-up. Muscle ultrasonography revealed a progressive increase in echogenicity.
Discussion:
FSHD in childhood has a slowly progressive but variable course over 2 years of follow-up. The most promising outcome measures to detect progression were the FSHD clinical score and muscle ultrasonography. Despite this disease progression, an improvement on functional capacity may still occur as the child grows up. Pain, fatigue, and a decreased quality of life were common symptoms and need to be addressed in the management of childhood FSHD. Our data can be used to counsel patients and as baseline measures for treatment trials in childhood FSHD.


Related Concept Videos
 01:21
Satellite Stem Cells and Muscular Dystrophy
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...