Related Experiment Video
Updated: Oct 15, 2025
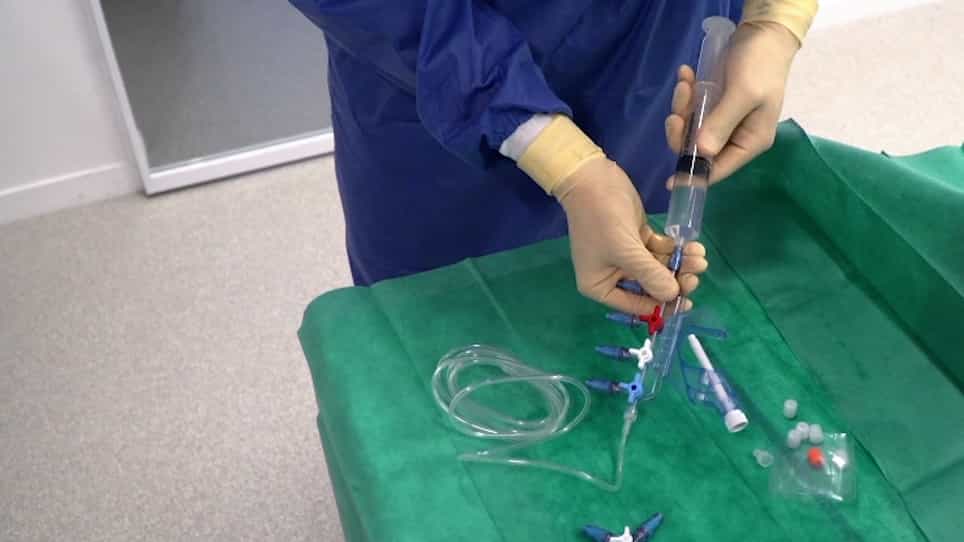
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Unnecessary removal of vascular access devices due to suspected infection in Australian intensive care units
India Pearse1, Amanda Corley1, Claire M Rickard1
1Alliance for Vascular Access Teaching and Research Group, Menzies Health Institute, Griffith University, Queensland, Australia; Nursing and Midwifery Research Centre, Royal Brisbane and Women's Hospital, Queensland, Australia; School of Nursing and Midwifery, Griffith University, Queensland, Australia; School of Nursing, Midwifery and Social Work, University of Queensland, Queensland, Australia.

Background:
Vascular access devices suspected of infection are often removed unnecessarily and frequently require replacement. The aim of this study was to identify the prevalence and economic impact of premature, unnecessary device removal due to suspected infection in adult patients admitted to the intensive care unit.
Methods:
Secondary data analysis of a prospectively collected data set detailing central venous catheters and peripheral arterial catheters in 1458 adult patients was conducted in nine Australian intensive care units. Data extracted from the parent database included patient demographics, device, and infection-specific data including the reason for device removal. Cost estimates were based on a recently published review of device utilisation and associated costs in Queensland public hospitals.
Results:
A total of 6144 central venous catheter days and 4696 arterial catheter days were studied. Median device dwell time was 7.2 (interquartile range: 5.6-9.0) days for central venous catheters and 6.5 (interquartile range: 4.8-8.5) days for arterial catheters. Device removal due to suspected infection occurred at a rate of 25.7 and 15.3 episodes/1000 catheter days in central venous and arterial catheters, respectively. Central venous and arterial catheter-related bloodstream infections occurred at a rate of 1.8 and 0.2 episodes/1000 catheter days, respectively. Central line-associated bloodstream infection occurred at a rate of 3.3 episodes/1000 catheter days. Local central venous and arterial catheter infection occurred at 0.16 and 0.02 episodes/1000 catheter days, respectively. The difference in incidence between devices suspected of infection and those responsible for infection resulted in AUD$67,087 unnecessarily spent on device replacement.
Conclusions:
Unnecessary device removal due to suspected infection presents a substantial clinical problem which is costly for the healthcare organisation and time-consuming for clinicians and places the patient at an increased risk of iatrogenic complications. There is a need for robust evidence and clinical practice guidelines to inform clinical decision-making to reduce unnecessary device removal.


Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
Endocarditis IV: Nursing Management
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:28
Asepsis
 01:23
Hand hygiene
Hand washing...