Related Experiment Video
Updated: Oct 15, 2025
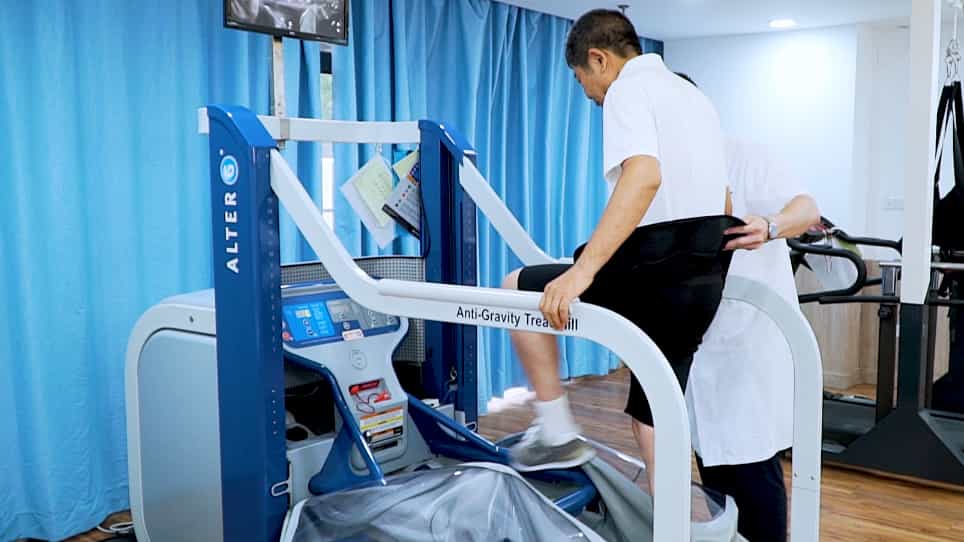

The Lower Body Positive Pressure Treadmill for Knee Osteoarthritis Rehabilitation
Published on: July 22, 2019
Moderators of the Effect of a Self-directed Digitally Delivered Exercise Program for People With Knee Osteoarthritis:
Rachel K Nelligan1, Rana S Hinman1, Fiona McManus2
1Centre for Health, Exercise and Sports Medicine, Department of Physiotherapy, School of Health Sciences, The University of Melbourne, Parkville, Australia.

Background:
A 24-week self-directed digitally delivered intervention was found to improve pain and function in people with knee osteoarthritis (OA). However, it is possible that this intervention may be better suited to certain subgroups of people with knee OA compared to others.
Objective:
The aim of this study was to explore whether certain individual baseline characteristics moderate the effects of a self-directed digitally delivered intervention on changes in pain and function over 24 weeks in people with knee OA.
Methods:
An exploratory analysis was conducted on data from a randomized controlled trial involving 206 people with a clinical diagnosis of knee OA. This trial compared a self-directed digitally delivered intervention comprising of web-based education, exercise, and physical activity program supported by automated exercise behavior change mobile phone text messages to web-based education alone (control). The primary outcomes were changes in overall knee pain (assessed on an 11-point numerical rating scale) and physical function (assessed using the Western Ontario and McMaster Universities Osteoarthritis Index function subscale [WOMAC]) at 24 weeks. Five baseline patient characteristics were selected as the potential moderators: (1) number of comorbidities, (2) number of other painful joints, (3) pain self-efficacy, (4) exercise self-efficacy, and (5) self-perceived importance of exercise. Separate linear regression models for each primary outcome and each potential moderator were fit, including treatment group, moderator, and interaction between treatment group and moderator, adjusting for the outcome at baseline.
Results:
There was evidence that pain self-efficacy moderated the effect of the intervention on physical function compared to the control at 24 weeks (interaction P=.02). Posthoc assessment of the mean change in WOMAC function by treatment arm showed that each 1-unit increase in baseline pain self-efficacy was associated with a 1.52 (95% CI 0.27 to 2.78) unit improvement in the control group. In contrast, a reduction of 0.62 (95% CI -1.93 to 0.68) units was observed in the intervention group with each unit increase in pain self-efficacy. There was only weak evidence that pain self-efficacy moderated the effect of the intervention on pain and that number of comorbidities, number of other painful joints, exercise self-efficacy, or exercise importance moderated the effect of the intervention on pain or function.
Conclusions:
With the exception of pain self-efficacy, which moderated changes in function but not pain, we found limited evidence that our selected baseline patient characteristics moderated intervention outcomes. This indicates that people with a range of baseline characteristics respond similarly to the unsupervised digitally delivered exercise intervention. As these findings are exploratory in nature, they require confirmation in future studies.
More Related Videos
 04:23
Author Spotlight: Using a Rabbit Model to Explore the Efficacy of Tuina in Treating Knee Osteoarthritis
Published on: August 25, 2023
 12:59
Improving Strength, Power, Muscle Aerobic Capacity, and Glucose Tolerance through Short-term Progressive Strength Training Among Elderly People
Published on: July 5, 2017