Related Experiment Video
Updated: Oct 14, 2025
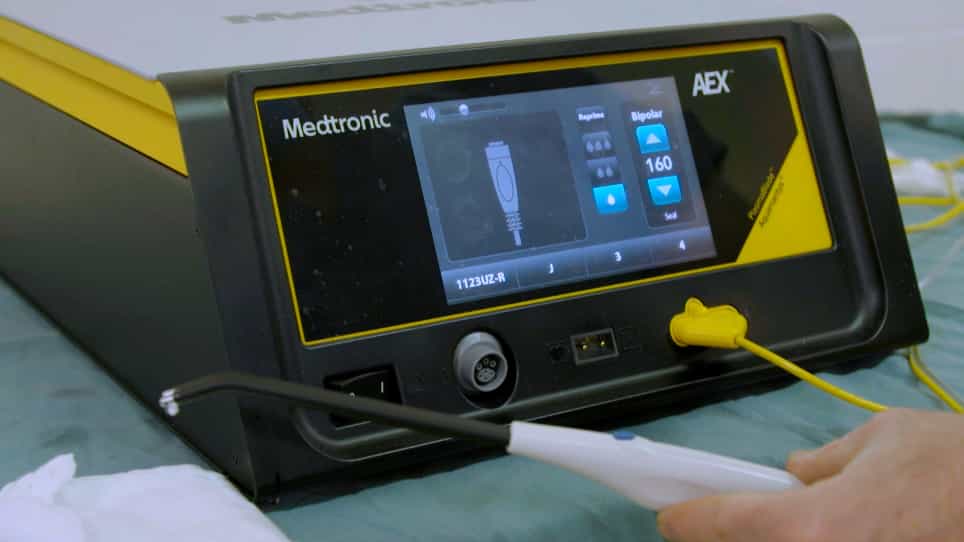

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Effects of Tranexamic Acid on Bleeding in Pediatric Surgeries: A Systematic Review and Meta-Analysis
Yiyong Wei1, Yajun Zhang2, Tao Jin3
1Department of Anesthesiology, Affiliated Hospital of Zunyi Medical University, Zunyi, China.

Insights
Tranexamic acid (TXA) significantly reduces blood loss and transfusion requirements in pediatric surgeries. This meta-analysis confirms TXA
Area of Science:
- Anesthesiology
- Pediatric Surgery
- Pharmacology
Background:
- Pediatric surgeries carry a risk of significant intraoperative blood loss.
- Managing blood loss is crucial for patient outcomes in pediatric surgical procedures.
Conclusions:
- Tranexamic acid is effective in managing bleeding during pediatric surgeries.
- TXA reduces the need for blood product transfusions in pediatric surgical patients.
- TXA offers a beneficial intervention for optimizing outcomes in pediatric surgery.
Abstract:
Background: Major pediatric surgeries can cause severe intraoperative blood loss. This meta-analysis aims to evaluate the efficacy of tranexamic acid (TXA) in pediatric surgeries. Methods: We searched PubMed, Embase, Web of Science, and Cochrane Library from the conception to March 31, 2021 to identify eligible randomized controlled trials (RCTs) that evaluated the efficacy of TXA in pediatric surgeries. Two reviewers choosed studies, evaluated quality, extracted data, and assessed the risk of bias independently. Mean difference (MD) was calculated as the summary statistic for continuous data. We used a random-effects model to measure mean effects. Data were generated from the corresponding 95% confidence interval (CI) using RevMan 5.3 software. Primary outcomes included intraoperative and postoperative blood loss, red blood cell (RBC) transfusion as well as fresh frozen plasma (FFP) transfusion. Results: Fifteen studies enrolling 1,332 patients were included in this study. The pooled outcomes demonstrated that TXA was associated with a decreased intraoperative (MD = -1.57 mL/kg, 95% CI, -2.54 to -0.60, P = 0.002) and postoperative (MD = -7.85 mL/kg, 95% CI, -10.52 to -5.19, P < 0.001) blood loss, a decreased intraoperative (MD = -7.08 mL/kg, 95% CI, -8.01 to -6.16, P < 0.001) and postoperative (MD = -5.30 mL/kg, 95% CI, -6.89 to -3.70, P < 0.001) RBC transfusion, as well as a decreased intraoperative (MD = -2.74 mL/kg, 95% CI, -4.54 to -0.94, P = 0.003) and postoperative (MD = -6.09 mL/kg, 95% CI, -8.26 to -3.91, P < 0.001) FFP transfusion in pediatric surgeries. However, no significant difference was noted between two groups in duration of surgery (MD = -12.51 min, 95% CI -36.65 to 11.63, P = 0.31). Outcomes of intraoperative and postoperative blood loss and the duration of surgery in included studies were not pooled due to the high heterogeneity. Conclusion: This meta-analysis demonstrated that TXA was beneficial for bleeding in pediatric surgeries.

Related Concept Videos
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Venous Thrombosis III: Interprofessional Care
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism