Related Experiment Video
Updated: Oct 14, 2025
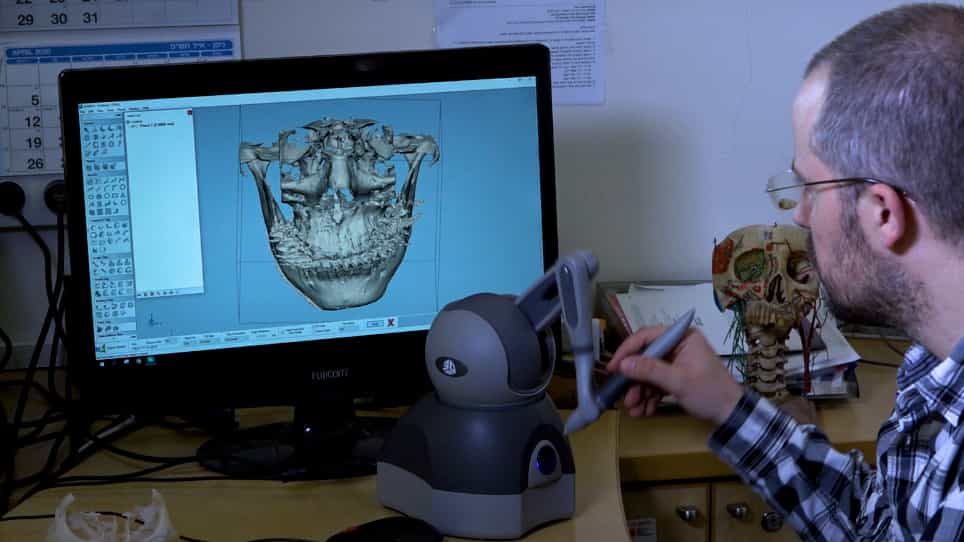

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Velopharyngeal Insufficiency in Craniofacial Microsomia: Prevalence, Diagnosis, and Treatment
Candace H Chan1, Allison C Hu1, Nirbhay S Jain1
1Division of Plastic and Reconstructive Surgery, University of California, Los Angeles, David Geffen School of Medicine.

Abstract:
The purpose of this study was to analyze the prevalence, diagnosis, and management of velopharyngeal insufficiency (VPI) in patients with craniofacial microsomia (CFM).Craniofacial microsomia patients 13 years of age and above treated at 2 centers from 1997 to 2019 were reviewed retrospectively for demographics, prevalence of VPI, and management of VPI. Patients with isolated microtia were excluded. Comparisons were made between patients with and without VPI using chi-square and independent samples t tests.Among 68 patients with CFM (63.2% male, mean 20.7 years of age), VPI was diagnosed in 19 patients (27.9%) at an average age of 7.2 years old. Among the total cohort, 61 patients had isolated CFM, of which 12 (19.6%) were diagnosed with VPI. Of the patients with isolated CFM and VPI, 8 patients (66.7%) were recommended for nasoendoscopy, of which only 2 patients completed. Seven isolated CFM patients (58.3%) underwent speech therapy, whereas none received VPI surgery. In contrast, 7 patients were diagnosed with both CFM and cleft lip and/or palate (CL/P), all of whom had VPI and were recommended for nasoendoscopy, with 5 (71.4%) completing nasoendoscopy, 6 (85.7%) undergoing speech therapy, and 6 (85.7%) undergoing corrective VPI surgery. Overall, we demonstrated that VPI was present in 27.9% of all CFM patients. On subset analysis, VPI was diagnosed in 20% of patients with isolated CFM and 100% of patients with CFM and CL/P. In addition, despite clinical diagnosis of VPI, a sizeable proportion of isolated CFM patients did not undergo therapy or surgical interventions.
More Related Videos

Related Concept Videos
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...