Related Experiment Video
Updated: Oct 14, 2025


Laser Capture Microdissection of Mouse Embryonic Cartilage and Bone for Gene Expression Analysis
Published on: December 18, 2019
Non-collagen pathogenic variants resulting in the osteogenesis imperfecta phenotype in children: a single-country
Patrick Thornley1, Nicholas Bishop2,3, Duncan Baker4
1The University of Sheffield Faculty of Medicine Dentistry and Health, Sheffield, UK.

Insights
Severe osteogenesis imperfecta (OI) in children is often caused by non-collagen gene variants. IFITM5, P3H1, SERPINF1, and BMP1 are frequently implicated, impacting clinical care for atypical OI cases.
Area of Science:
- Genetics
- Pediatrics
- Rare Diseases
Background:
- Severe, complex, and atypical osteogenesis imperfecta (OI) in children (0-18 years) in England is managed by a Highly Specialised Service (HSS OI).
- The majority of 'atypical' OI cases managed by the HSS OI have genetic origins not linked to COL1A1 or COL1A2.
- This study assesses the spectrum and frequency of non-collagen pathogenic variants causing OI within this national service.
Purpose of the Study:
- To evaluate the range and frequency of non-collagen pathogenic variants in children with atypical osteogenesis imperfecta (OI).
- To understand the genetic basis of severe and complex OI cases managed by the Highly Specialised Service (HSS OI).
Main Methods:
- Children meeting 'atypical' OI criteria within the HSS OI service database were identified.
- Genetic testing was performed at the Sheffield Diagnostic Genetics Service, and variant data were extracted and matched to patients.
- This service evaluation was registered with the Sheffield Children's Hospital Clinical Governance Department.
Main Results:
- Of 337 children in the HSS OI, 100 met 'atypical' criteria; 80 underwent genetic testing.
- Genetic changes were detected in 72 children, with 67 having variants in 13 known OI-causative genes.
- The most frequent genes affected were IFITM5 (22 children), P3H1 (12), SERPINF1 (8), and BMP1 (6).
Conclusions:
- Approximately 20% of children with severe OI forms have pathogenic variants in non-collagen genes.
- IFITM5 was the most commonly implicated gene, followed by the P3H1 complex genes.
- These findings offer insights into the genetic etiology of OI, potentially guiding clinical management.
Background/Objectives:
In England, children (0-18 years) with severe, complex and atypical osteogenesis imperfecta (OI) are managed by four centres (Birmingham, Bristol, London, Sheffield) in a 'Highly Specialised Service' (HSS OI); affected children with a genetic origin for their disease that is not in COL1A1 or COL1A2 form the majority of the 'atypical' group, which has set criteria for entry into the service. We have used the data from the service to assess the range and frequency of non-collagen pathogenic variants resulting in OI in a single country.
Methods:
Children with atypical OI were identified through the HSS OI service database. All genetic testing for children with OI in the service were undertaken at the Sheffield Diagnostic Genetics Service. Variant data were extracted and matched to individual patients. This study was done as part of a service evaluation project registered with the Sheffield Children's Hospital Clinical Governance Department.
Results:
One hundred of 337 children in the HSS met the 'atypical' criteria. Eighty have had genetic testing undertaken; 72 had genetic changes detected, 67 in 13 genes known to be causative for OI. The most frequently affected genes were IFITM5 (22), P3H1 (12), SERPINF1 (8) and BMP1 (6).
Conclusion:
Among children with more severe forms of OI (approximately one-third of all children with OI), around 20% have pathogenic variants in non-collagen genes. IFITM5 was the most commonly affected gene, followed by genes within the P3H1 complex. These data provide additional information regarding the likelihood of different genetic origins of the disease in children with OI, which may influence clinical care.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Osteoclasts in Bone Remodeling
 01:43
Incomplete Dominance
 01:33
Pleiotropy
 01:24
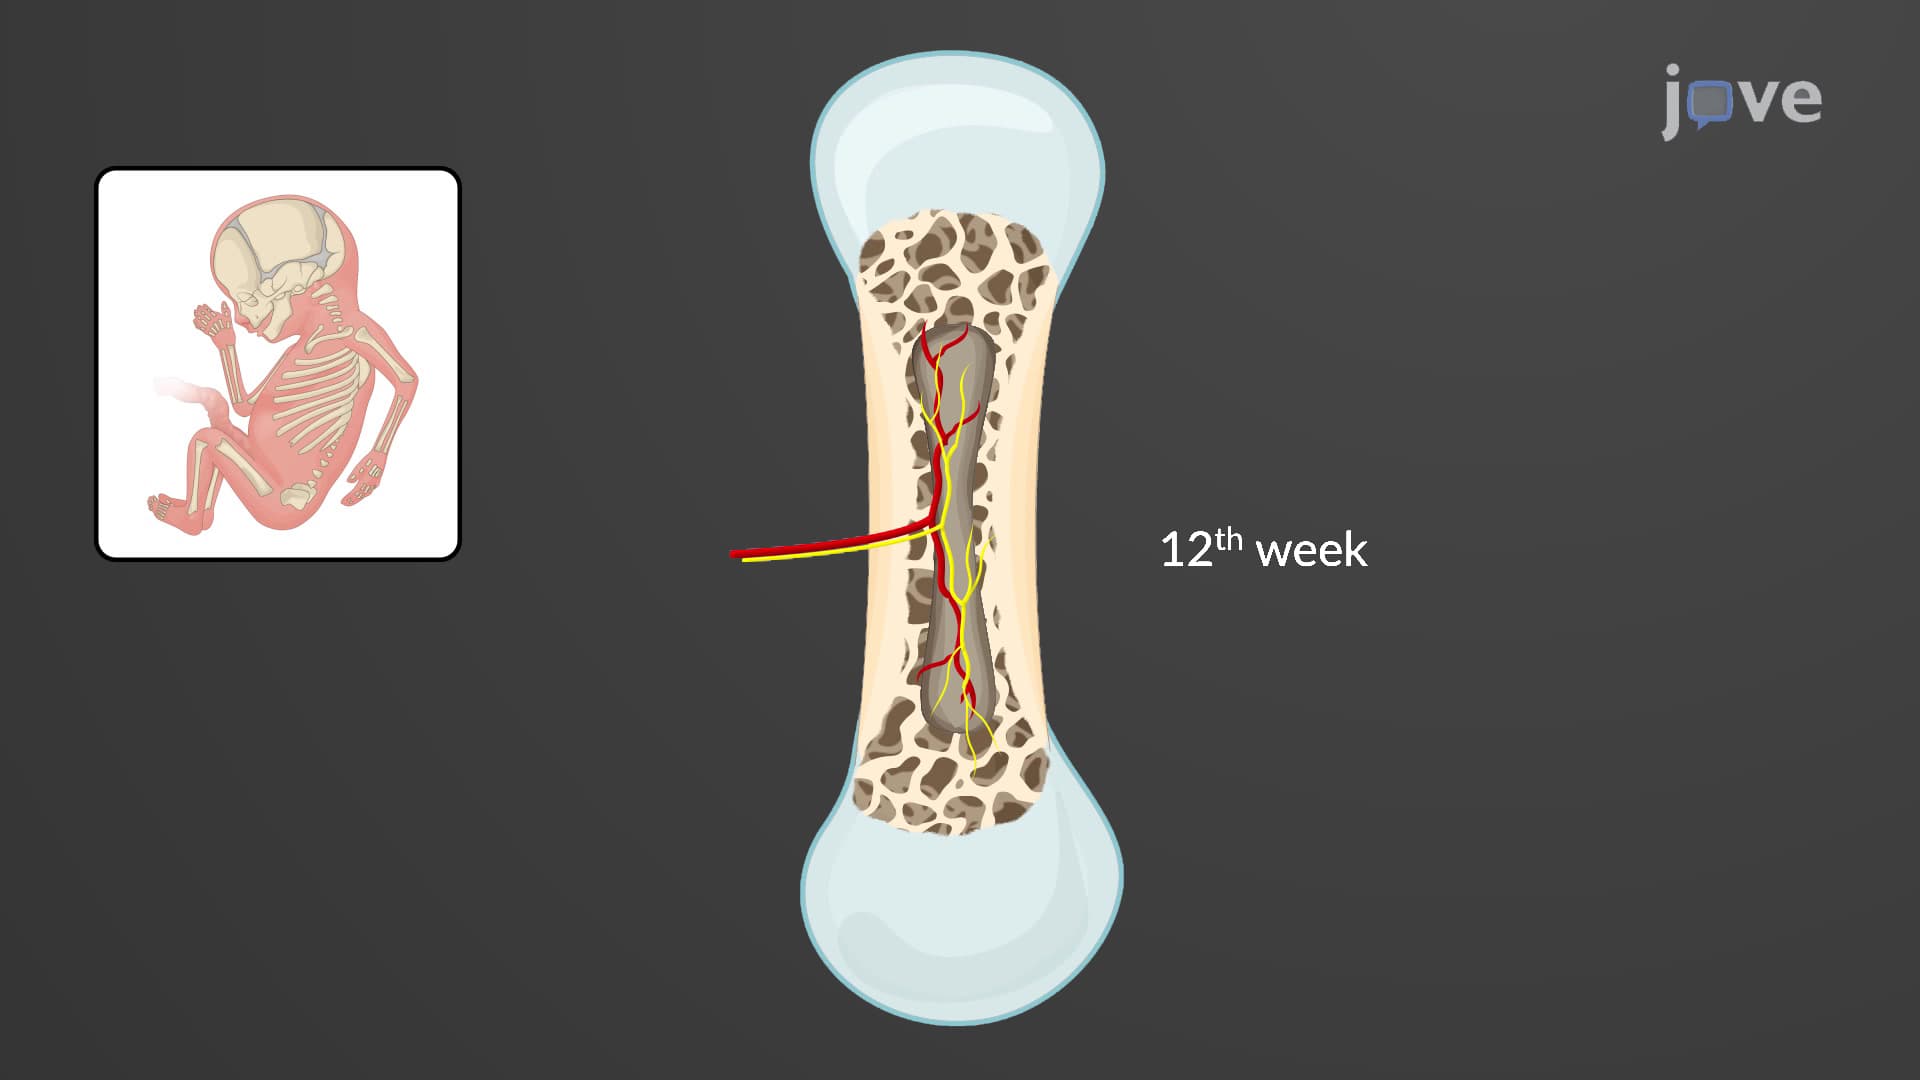
Bone Formation by Endochondral Ossification
 01:35
Pedigree Analysis