Related Experiment Video
Updated: Oct 13, 2025
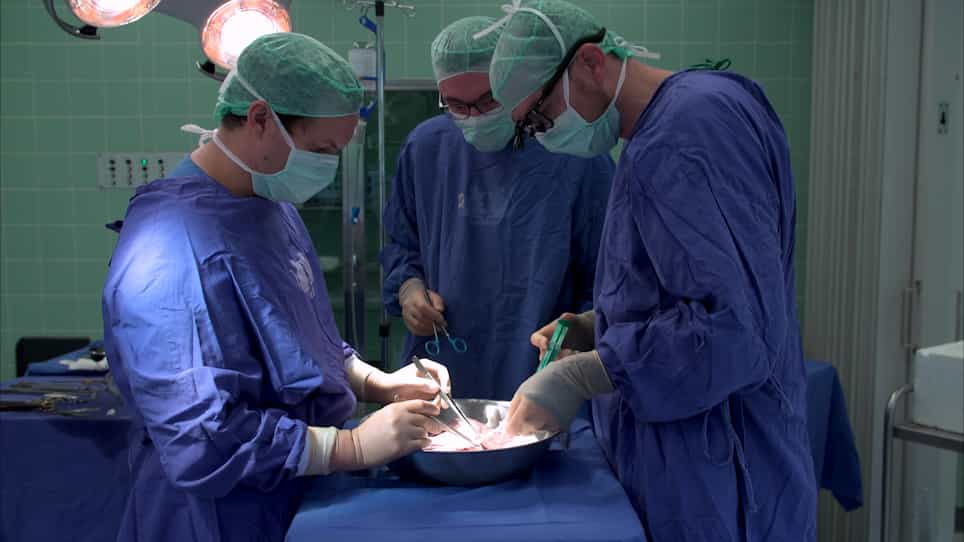
Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Impact of MELD 30-allocation policy on liver transplant outcomes in Italy
Matteo Ravaioli1, Quirino Lai2, Maurizio Sessa3
1Dipartimento di Chirurgia Generale e Trapianti, IRCCS, Azienda Ospedaliero-Universitaria di Bologna, Bologna, Italy; Dipartimento di Scienze Mediche e Chirurgiche (DIMEC), University of Bologna, Bologna, Italy.

Background & Aims:
In Italy, since August 2014, liver transplant (LT) candidates with model for end-stage liver disease (MELD) scores ≥30 receive national allocation priority. This multicenter cohort study aims to evaluate time on the waiting list, dropout rate, and graft survival before and after introducing the macro-area sharing policy.
Methods:
A total of 4,238 patients registered from 2010 to 2018 were enrolled and categorized into an ERA-1 Group (n = 2,013; before August 2014) and an ERA-2 Group (n = 2,225; during and after August 2014). A Cox proportional hazards model was used to estimate the hazard ratio (HR) of receiving a LT or death between the two eras. The Fine-Gray model was used to estimate the HR for dropout from the waiting list and graft loss, considering death as a competing risk event. A Fine-Gray model was also used to estimate risk factors of graft loss.
Results:
Patients with MELD ≥30 had a lower median time on the waiting list (4 vs.12 days, p <0.001) and a higher probability of being transplanted (HR 2.27; 95% CI 1.78-2.90; p = 0.001) in ERA-2 compared to ERA-1. The subgroup analysis on 3,515 LTs confirmed ERA-2 (odds ratio 0.56; 95% CI 0.46-0.68; p = 0.001) as a protective factor for better graft survival rate. The protective variables for lower dropouts on the waiting list were: ERA-2, high-volume centers, no competition centers, male recipients, and hepatocellular carcinoma. The protective variables for graft loss were high-volume center and ERA-2, while MELD ≥30 remained related to a higher risk of graft loss.
Conclusions:
The national MELD ≥30 priority allocation was associated with improved patient outcomes, although MELD ≥30 was associated with a higher risk of graft loss. Transplant center volumes and competition among centers may have a role in recipient prioritization and outcomes.
Clinical Trial Number:
NCT04530240 LAY SUMMARY: Italy introduced a new policy in 2014 to give national allocation priority to patients with a model for end-stage liver disease (MELD) score ≥30 (i.e. very sick patients). This policy has led to more liver transplants, fewer dropouts, and shorter waiting times for patients with MELD ≥30. However, a higher risk of graft loss still burdens these cases. Transplant center volumes and competition among centers may have a role in recipient prioritization and outcomes.

Related Concept Videos
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:28
Kidney Transplant I: Introduction