Related Experiment Video
Updated: Oct 13, 2025


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
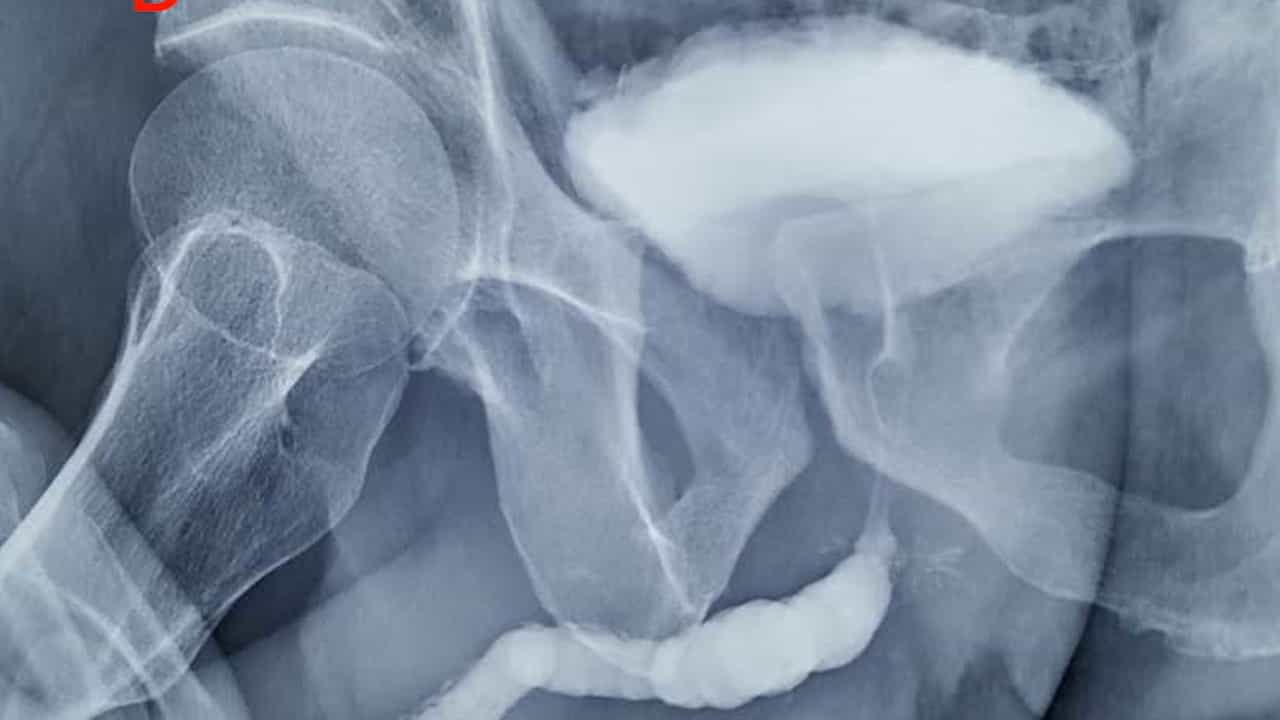
Pelvic Fracture Urethral Distraction Defects in Preschool Boys: How to Recognize and Manage?
Lin Wang1, Jiasheng Chen1, Rong Lv1
1Department of Urology, Shanghai Jiaotong University Affiliated Sixth People's Hospital, Shanghai, China; Shanghai Eastern Institute of Urologic Reconstruction, Shanghai, China.

Insights
Pelvic fracture urethral distraction defects (PFUDD) in young boys can be successfully treated with transperineal anastomotic urethroplasty. This technique achieved a 100% success rate in a small cohort, offering a promising solution for this challenging condition.
Area of Science:
- Pediatric Urology
- Trauma Surgery
- Reconstructive Urology
Background:
- Pelvic fracture urethral distraction defect (PFUDD) in preschool boys is a rare and challenging condition.
- Management requires specialized surgical expertise to restore urethral continuity and function.
Purpose of the Study:
- To report cases of PFUDD in preschool boys.
- To evaluate the efficacy of transperineal anastomotic urethroplasty for treating PFUDD in this age group.
Main Methods:
- Retrospective review of 8 preschool boys (<6 years) with PFUDD treated between 2010 and 2021.
- All patients underwent transperineal anastomotic urethroplasty, with a minimum 3-month interval post-trauma or failed intervention.
- One case involved combined urethroplasty and urethrorectal fistula repair.
Main Results:
- A 100% success rate was achieved in all 8 patients, defined by restored urethral patency and continuity without further intervention.
- No recurrence of stenosis or urinary fistulas were observed during a median follow-up of 65 months (range 3-135 months).
- One patient experienced stress urinary incontinence during high-intensity exercise; potency could not be assessed due to age.
Conclusions:
- Transperineal anastomotic urethroplasty is a highly effective strategy for managing PFUDD in preschool boys.
- This approach offers a high success rate and favorable outcomes, addressing a significant challenge in pediatric reconstructive urology.
Objective:
To share the cases of pelvic fracture urethral distraction defect (PFUDD) in preschool boys and evaluate the transperineal anastomotic urethroplasty strategy for the treatment of these cases.
Materials And Methods:
Between January 2010 and May 2021, 8 preschool boys (<6 years) with PFUDD underwent the transperineal anastomotic urethroplasty in our center were retrospectively reviewed. Etiology was traumatic pelvic fracture in all boys. The type of trauma included: fall injury in 1 and vehicle crush injury in 7. Urethroplasty was performed at least 3 months after initial trauma or the last failed intervention. One of them suffered from PFUDD associated with urethrorectal fistula received urethroplasty combined with fistula repair. A successful urethroplasty was defined as restoring the patency and continuity of urethra and no further interventions were needed.
Results:
Follow-up was obtained in all the 8 preschool boys for 3-135 (median: 65) months. The average age was 4.1 years old (range 1-5). After operation, the final success rate was 100%. Neither stenosis recurrence nor urinary fistulas were reported during follow-up. Of the 8 boys, 1 developed urinary incontinence, only occurring after high-intensity exercise such as running. Potency state could not be evaluated for all boys due to the young age. One boy reported having normal morning erection after a follow-up of 135 months.
Conclusion:
PFUDD in preschool boys is a challenge for both the urologist and parent. Our study preliminarily confirmed that the progressive anastomotic urethroplasty strategy can ensure a high success rate.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 03:37
Iatrogenic Injury Recapitulated: Electroexcision Technique for Urethral Stricture Modeling in Rats
Published on: October 11, 2024
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: