Related Experiment Video
Updated: Oct 13, 2025
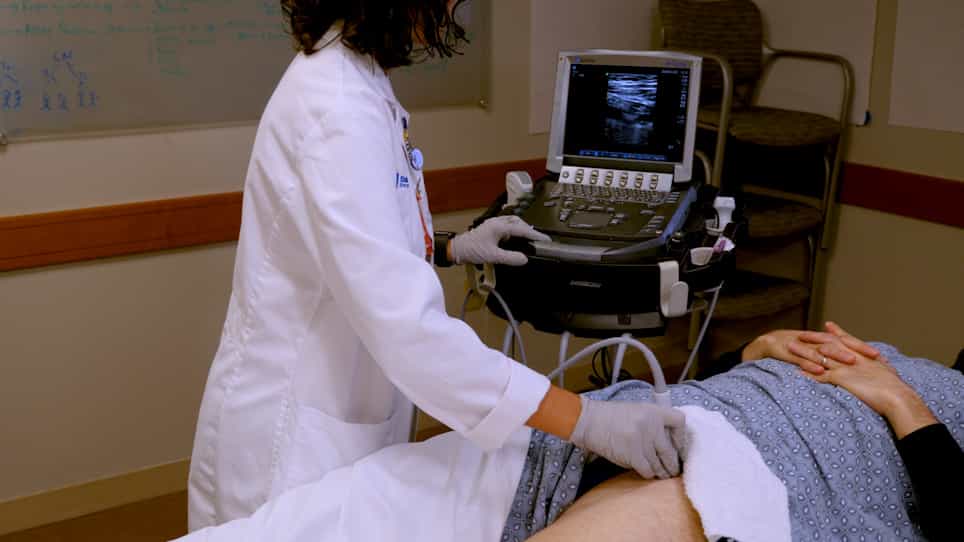
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
SOFA Score as a Reliable Tool to Detect High Risk for Venous Thrombosis in Patients With Critical Stage SARS-CoV-2
Giorgio Prouse1, Ludovica Ettorre1, Francesco Mongelli2
1Service of Vascular Surgery, Centro Vascolare Ticino, Ospedali Regionali di Lugano, Bellinzona e Locarno, Switzerland.

Abstract:
Background: Severe acute respiratory syndrome from coronavirus-2 (SARS-CoV-2) has been associated with an increased risk of venous thromboembolism (VTE). Different anticoagulation protocols have been applied in several studies in the absence of clear evidence. A reliable deep venous thrombosis (DVT) indicator in critical patients with SARS-CoV-2 could guide the anticoagulation treatment; however, it has not yet been identified, and clinical applicability of the most common markers is debatable. The aim of our study was to determine the actual incidence of DVT in critically ill SARS-CoV-2 patients and to find a reliable tool to identify patients who might benefit from therapeutic-intensity anticoagulation. Methods: From March 1, 2020 to May 31, 2020, all patients admitted to the intensive care unit (ICU) for SARS-CoV-2 at Ospedale Regionale di Locarno, Locarno, Switzerland, were prospectively enrolled and screened daily with ultrasound for DVT. Following international consensus, a higher-intensity thromboprophylaxis was administered to all patients who were not at increased risk for bleeding. Sepsis-induced coagulopathy (SIC) and sequential organ failure assessment (SOFA) scores were calculated and time-to-DVT event in a COX proportional-hazard regression model was performed. A receiver operating characteristic (ROC) curve was used to determine sensitivity and specificity and the Youden's Index to establish the best threshold. Results: A total of 96 patients were enrolled. Deep venous thrombosis was detected in 37% of patients. Sepsis-induced coagulopathy and SOFA scores were both correlated to DVT. A SIC score of 1 vs. ≥2 showed a close association with DVT, with sensitivity, specificity, and positive and negative predictive values of 90.0, 48.1, and 49.1, and 89.7%, respectively. Most significantly though, a SOFA score of 1 or 2 points was shown to be the most accurate value in predicting the absence of DVT, indicating no need for therapeutic-intensity anticoagulation. Its sensitivity, specificity, and positive and negative predictive values were 87.9, 100, and 100, and 93.7%, respectively. The D-dimer test showed lower sensitivity and specificity whereas platelet count and aPTT were not found to be correlated to DVT. Conclusions: Patients with SOFA scores of 1 or 2 are at low risk of developing DVT and do not require therapeutic-intensity anticoagulation. Conversely, patients with scores ≥3 are at high risk of developing DVT.
More Related Videos
 08:05
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:30
Venous Thrombosis I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies