Related Experiment Video
Updated: Oct 12, 2025


A Delayed Inoculation Model of Chronic Pseudomonas aeruginosa Wound Infection
Published on: February 20, 2020
Prehospital delay is an important risk factor for mortality in community-acquired bloodstream infection (CA-BSI): a
Martin Holmbom1,2, Maria Andersson2, Sören Berg3
1Department of Urology, and Department of Biomedical and Clinical Sciences, Linköping University, Linköping, Sweden martin.holmbom@regionostergotland.se.

Objectives:
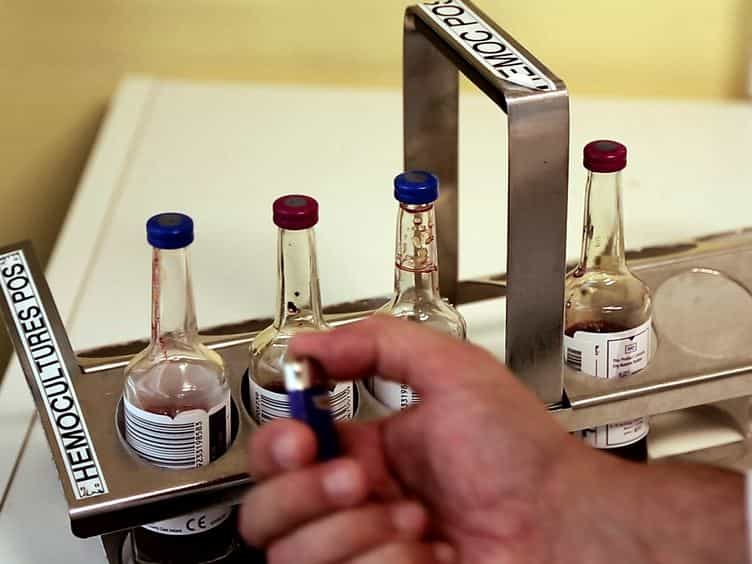
The aim of this study was to identify prehospital and early hospital risk factors associated with 30-day mortality in patients with blood culture-confirmed community-acquired bloodstream infection (CA-BSI) in Sweden.
Methods:
A retrospective case-control study of 1624 patients with CA-BSI (2015-2016), 195 non-survivors satisfying the inclusion criteria were matched 1:1 with 195 survivors for age, gender and microorganism. All forms of contact with a healthcare provider for symptoms of infection within 7 days prior CA-BSI episode were registered. Logistic regression was used to analyse risk factors for 30-day all-cause mortality.
Results:
Of the 390 patients, 61% (115 non-survivors and 121 survivors) sought prehospital contact. The median time from first prehospital contact till hospital admission was 13 hours (6-52) for non-survivors and 7 hours (3-24) for survivors (p<0.01). Several risk factors for 30-day all-cause mortality were identified: prehospital delay OR=1.26 (95% CI: 1.07 to 1.47), p<0.01; severity of illness (Sequential Organ Failure Assessment score) OR=1.60 (95% CI: 1.40 to 1.83), p<0.01; comorbidity score (updated Charlson Index) OR=1.13 (95% CI: 1.05 to 1.22), p<0.01 and inadequate empirical antimicrobial therapy OR=3.92 (95% CI: 1.64 to 9.33), p<0.01. In a multivariable model, prehospital delay >24 hours from first contact remained an important risk factor for 30-day all-cause mortality due to CA-BSI OR=6.17 (95% CI: 2.19 to 17.38), p<0.01.
Conclusion:
Prehospital delay and inappropriate empirical antibiotic therapy were found to be important risk factors for 30-day all-cause mortality associated with CA-BSI. Increased awareness and earlier detection of BSI in prehospital and early hospital care is critical for rapid initiation of adequate management and antibiotic treatment.
More Related Videos
Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:20
Infection
The chain begins with pathogens: bacteria, viruses, fungi, prions, or parasites such as protozoa helminths. These can be present on the skin as transient or resident flora, or they can be acquired from the environment. Identifying and treating the type of infection and...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...