Related Experiment Video
Updated: Oct 12, 2025
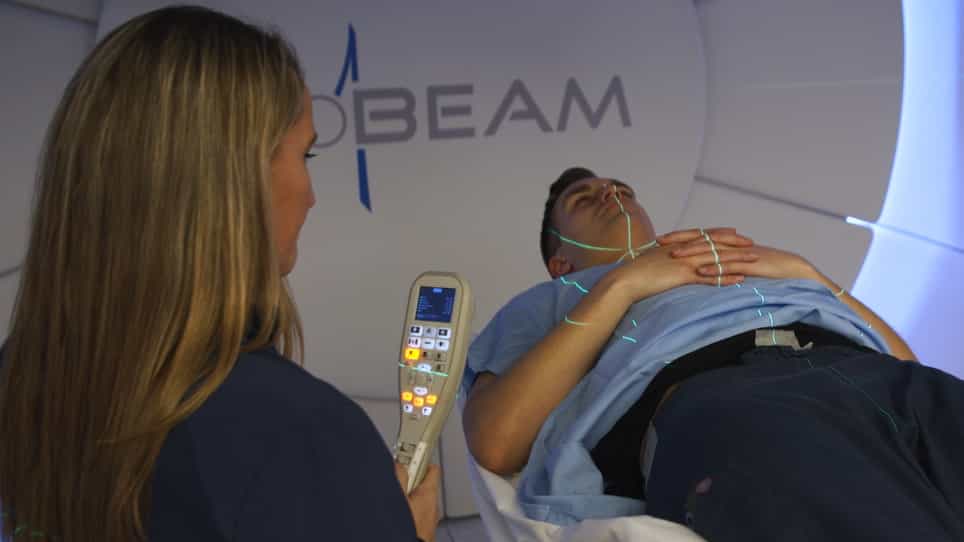

Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Normal tissue complication probability modeling to guide individual treatment planning in pediatric cranial proton
Mikaela Dell'Oro1,2, Puthenparampil Wilson2,3, Michala Short1
1Cancer Research Institute, University of South Australia, Adelaide, Australia.

Insights
Proton therapy (PT) reduces normal tissue complication probability (NTCP) compared to intensity-modulated radiation therapy (IMRT). Pediatric patient age and sex significantly impact NTCP, necessitating personalized treatment planning for cranial cancers.
Area of Science:
- Radiation Oncology
- Pediatric Oncology
- Radiobiology
Background:
- Proton therapy (PT) is the standard for pediatric cranial tumors, offering superior dose distribution over photon radiotherapy.
- Pediatric normal tissue complication probability (NTCP) data is limited, often relying on adult models.
- Patient age, sex, and intrinsic radiosensitivity (α/β ratio) may influence radiation response.
Purpose of the Study:
- To conduct sensitivity analyses of NTCP models for pediatric cranial radiotherapy.
- To determine the influence of radiosensitivity, age, and sex on NTCP.
- To predict cranial side-effects from intensity-modulated proton therapy (IMPT) and intensity-modulated radiotherapy (IMRT).
Main Methods:
- Retrospective optimization of IMPT and IMRT plans for pediatric cranial datasets (ages 5, 9, 13).
- Radiobiological modeling using Relative-Seriality and Lyman-Kutcher-Burman models in BioSuite Software.
- Sensitivity analyses varying TD50 to simulate sex-dependent radiosensitivity and α/β ratios.
Main Results:
- IMPT consistently yielded lower NTCP than IMRT across all models (p < 0.0001).
- Female patients may have underestimated risks for brainstem necrosis and cochlea tinnitus due to lower TD50.
- Sex and α/β ratio significantly influenced NTCP for brainstem necrosis and cochlea tinnitus (p < 0.0001).
Conclusions:
- Sensitivity analyses highlight the critical role of patient age and sex in pediatric cranial radiotherapy NTCP.
- Female pediatric patients may face up to double the risk of certain side-effects if radiosensitivity differences are not considered.
- Individualized NTCP modeling incorporating age and sex is crucial for optimizing pediatric cranial radiation therapy outcomes.
Purpose:
Proton therapy (PT) is broadly accepted as the gold standard of care for pediatric patients with cranial cancer. The superior dose distribution of PT compared to photon radiotherapy reduces normal tissue complication probability (NTCP) for organs at risk. As NTCPs for pediatric organs are not well understood, clinics generally base radiation response on adult data. However, there is evidence that radiation response strongly depends on the age and even sex of a patient. Furthermore, questions surround the influence of individual intrinsic radiosensitivity (α/β ratio) on pediatric NTCP. While the clinical pediatric NTCP data is scarce, radiobiological modeling and sensitivity analyses can be used to investigate the NTCP trends and its dependence on individual modeling parameters. The purpose of this study was to perform sensitivity analyses of NTCP models to ascertain the dependence of radiosensitivity, sex, and age of a child and predict cranial side-effects following intensity-modulated proton therapy (IMPT) and intensity-modulated radiotherapy (IMRT).
Methods:
Previously, six sex-matched pediatric cranial datasets (5, 9, and 13 years old) were planned in Varian Eclipse treatment planning system (13.7). Up to 108 scanning beam IMPT plans and 108 IMRT plans were retrospectively optimized for a range of simulated target volumes and locations. In this work, dose-volume histograms were extracted and imported into BioSuite Software for radiobiological modeling. Relative-Seriality and Lyman-Kutcher-Burman models were used to calculate NTCP values for toxicity endpoints, where TD50, (based on reported adult clinical data) was varied to simulate sex dependence of NTCP. Plausible parameter ranges, based on published literature for adults, were used in modeling. In addition to sensitivity analyses, a 20% difference in TD50 was used to represent the radiosensitivity between the sexes (with females considered more radiosensitive) for ease of data comparison as a function of parameters such as α/β ratio.
Results:
IMPT plans resulted in lower NTCP compared to IMRT across all models (p < 0.0001). For medulloblastoma treatment, the risk of brainstem necrosis (> 10%) and cochlea tinnitus (> 20%) among females could potentially be underestimated considering a lower TD50 value for females. Sensitivity analyses show that the difference in NTCP between sexes was significant (p < 0.0001). Similarly, both brainstem necrosis and cochlea tinnitus NTCP varied significantly (p < 0.0001) across tested α/β as a function of TD50 values (assumption being that TD50 values are 20% lower in females). If the true α/β of these pediatric tissues is higher than expected (α/β ∼ 3), the risk of tinnitus for IMRT can significantly increase (p < 0.0001).
Conclusion:
Due to the scarcity of pediatric NTCP data available, sensitivity analyses were performed using plausible ranges based on published adult data. In the clinical scenario where, if female pediatric patients were 20% more radiosensitive (lower TD50 value), they could be up to twice as likely to experience side-effects of brainstem necrosis and cochlea tinnitus compared to males, highlighting the need for considering the sex in NTCP models. Based on our sensitivity analyses, age and sex of a pediatric patient could significantly affect the resultant NTCP from cranial radiotherapy, especially at higher α/β values.

