Related Experiment Video
Updated: Oct 11, 2025


Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Gastric Adenocarcinoma of the Fundic Gland Type: A Case Report
Akinari Kakumoto1, Hajime Kuroda1, Tsengelmaa Jamiyan2
1Department of Diagnostic Pathology, Tokyo Women's Medical University, Medical Center East, Tokyo, Japan.

Abstract:
BACKGROUND Gastric adenocarcinoma of the fundic gland type (GAFG) is an extremely rare neoplasm that consists of a mixed proliferation of oxyntic and chief cells. Differential diagnosis of GAFG is difficult in the absence of infiltration. Here, we report a case of GAFG and discuss the clinicopathological features. CASE REPORT A 78-year-old man was diagnosed with gastritis and reflux esophagitis, status after esophagectomy for carcinoma of the esophagus in 2015. The patient underwent repeated gastric biopsies in 2017 and an atypical epithelium was observed, but no diagnosis was confirmed. There was no evidence of tumor extension in the submucosa. The tumor was resected via endoscopic mucosal resection, and pathological examination was performed. Microscopic findings revealed an oxyntic-type gastric mucosa with atypical dense or dilated glands with abundant pale basophilic cytoplasm and round nuclei with prominent nucleoli. The majority of the tumor cells resembled chief cells, suggesting they were derived from gastric fundic glands. However, the tumor appeared to have no submucosal infiltration or focal stromal desmoplastic reaction. Sections stained positive for MUC6 and pepsinogen-I in chief cells, and H+/K+ ATPase and PDGFRa in parietal cells, but were mostly negative for CDX2, chromogranin A, synaptophysin, and CD10. Sections stained for mib-1 expressed very low proliferative activity, with an average of 10%. Staining for TP53 overexpression was negative. CONCLUSIONS Immunostaining markers are a supportive tool for histological diagnosis of GAFG. However, if there is no infiltration, as in our case, it is difficult to consider it as a malignant tumor. Further elucidation is needed in the future, including an officially accepted diagnostic name.
More Related Videos


Related Concept Videos
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:25
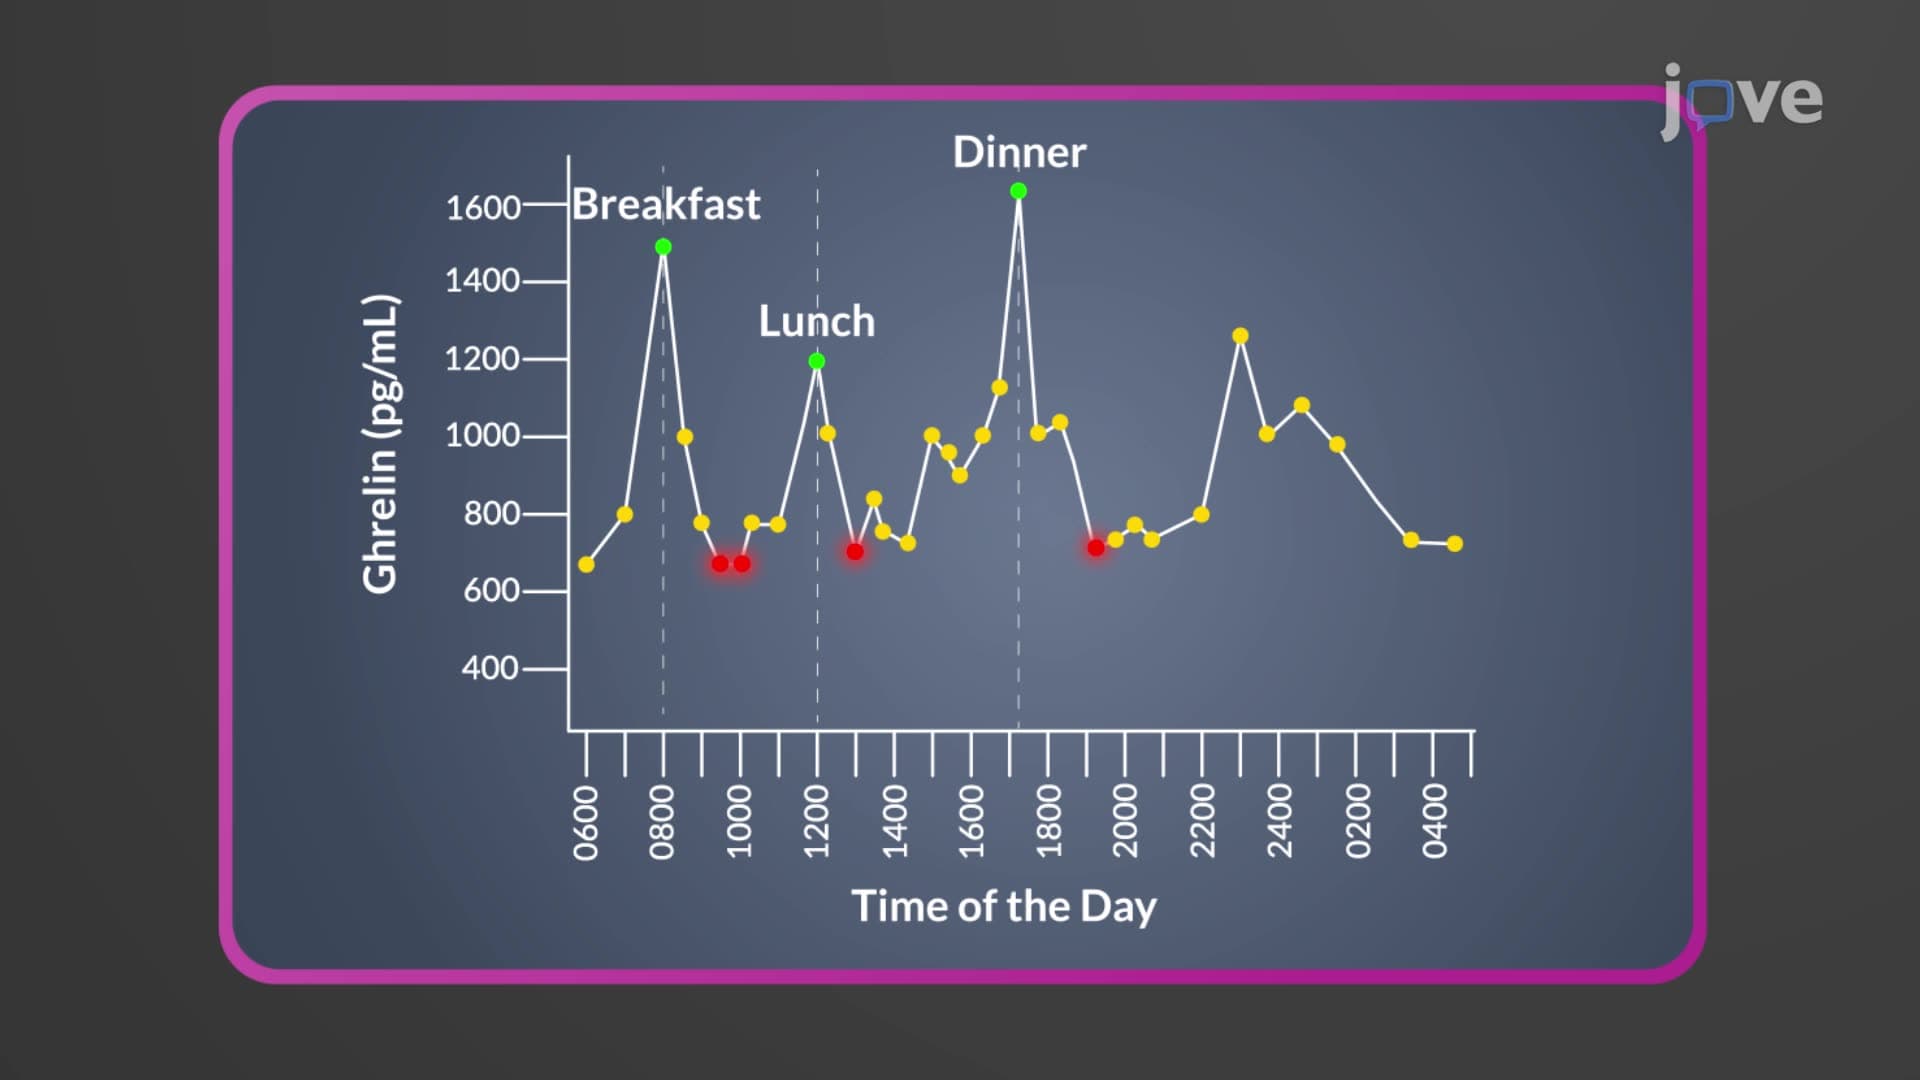
Hormones Secreted by the Stomach
Each of these hormones secreted by different enteroendocrine cells plays a unique role in digestion. Here are a few examples: