Related Experiment Video
Updated: Oct 11, 2025
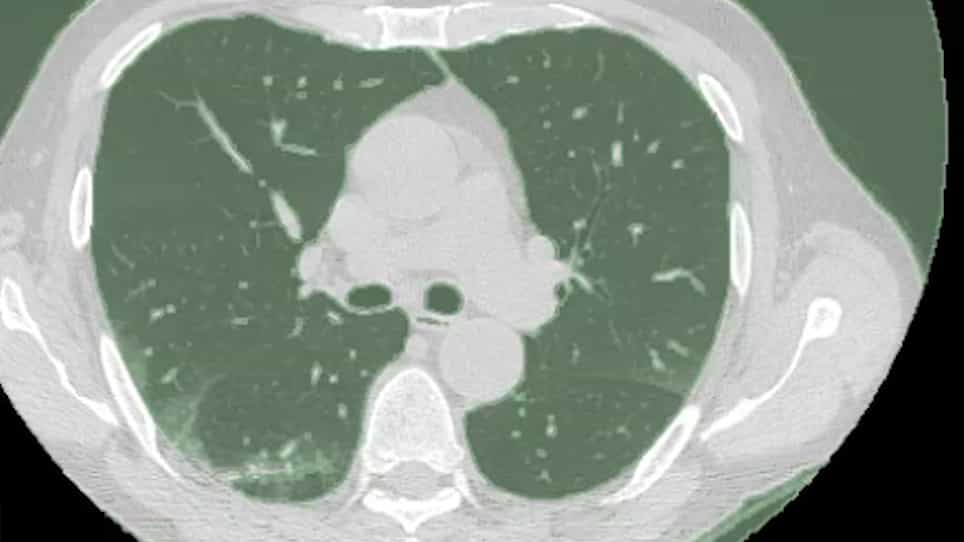

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Concurrent Cerebral, Splenic, and Renal Infarction in a Patient With COVID-19 Infection
Ricardo Rigual1, Gerardo Ruiz-Ares1, Jorge Rodriguez-Pardo1
1Departments of Neurology.

Insights
COVID-19 infection can cause arterial thrombosis, leading to multiple organ infarctions. Monitoring inflammatory markers like D-dimer aids in tailoring antithrombotic treatment for these severe thrombotic events.
Area of Science:
- Neurology
- Cardiology
- Infectious Diseases
Background:
- Thrombotic events are serious complications of COVID-19.
- Arterial thrombosis occurs in approximately 3% of COVID-19 patients.
- This case highlights concurrent cerebral and noncerebral infarction in a COVID-19 patient.
Observation:
- A 53-year-old male with COVID-19 pneumonia presented with stroke symptoms.
- Elevated inflammatory and coagulation markers (D-dimer, ferritin, IL-6, CRP) were noted.
- Neuroimaging revealed right middle cerebral artery occlusion; CT showed splenic and bilateral renal infarctions.
Findings:
- The patient underwent successful thrombolysis, mechanical thrombectomy, and splenic pseudoaneurysm embolization.
- Treatment included intermediate-dose anticoagulation, aspirin, and corticosteroids.
- Inflammatory markers normalized, leading to cessation of anticoagulation and continued aspirin therapy.
Implications:
- D-dimer and other inflammatory markers can guide individualized antithrombotic strategies in COVID-19.
- Further research is needed to understand COVID-19-related stroke mechanisms and optimal treatment.
- This case underscores the multifaceted thrombotic risks associated with COVID-19.
Introduction:
Thrombotic events are potentially devastating complications of coronavirus disease 2019 (COVID-19) infection. Although less common than venous thromboembolism, arterial thrombosis has been reported in COVID-19 cohorts in almost 3% of patients. We describe a patient with COVID-19 infection and concurrent cerebral and noncerebral infarction.
Case Report:
A 53-year-old man with history of COVID-19 pneumonia was admitted to a primary stroke center for speech disturbances and left hemiplegia. Urgent laboratory tests showed a great increase of inflammatory and coagulation parameters as D-dimer, ferritin, interleukin-6 and C-reactive protein. Neuroimaging found occlusion of the M1 segment of the right middle cerebral artery with early signs of ischemic stroke. He received intravenous thrombolysis and mechanical thrombectomy. Abdominal computed tomography discovered a splenic infarction with hemorrhagic transformation and bilateral renal infarction. Urgent angiography showed an associated splenic pseudoaneurysm, which was embolized without complications. He was treated with intermediate-dose anticoagulation (1 mg subcutaneous enoxaparin/kg/24 h), acetylsalicylic acid 100 mg and 5 days of intravenous corticosteroids. In the following days, inflammatory markers decreased so anticoagulant treatment was stopped and acetylsalicylic acid 300 mg was prescribed. His condition improved and he was discharged to a rehabilitation facility on hospital day 30.
Conclusion:
In this case, a patient with multiple thrombotic events in the acute phase of COVID-19 infection, the delimitation of the inflammatory state through analytical markers as D-dimer helped to individualize the antithrombotic treatment (full anticoagulation or anticoagulation at intermediate doses plus antiplatelet treatment as used in our patient) and its duration. However, more data are needed to better understand the mechanisms and treatment of stroke in patients with COVID-19 infection.


Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis