Related Experiment Video
Updated: Oct 11, 2025
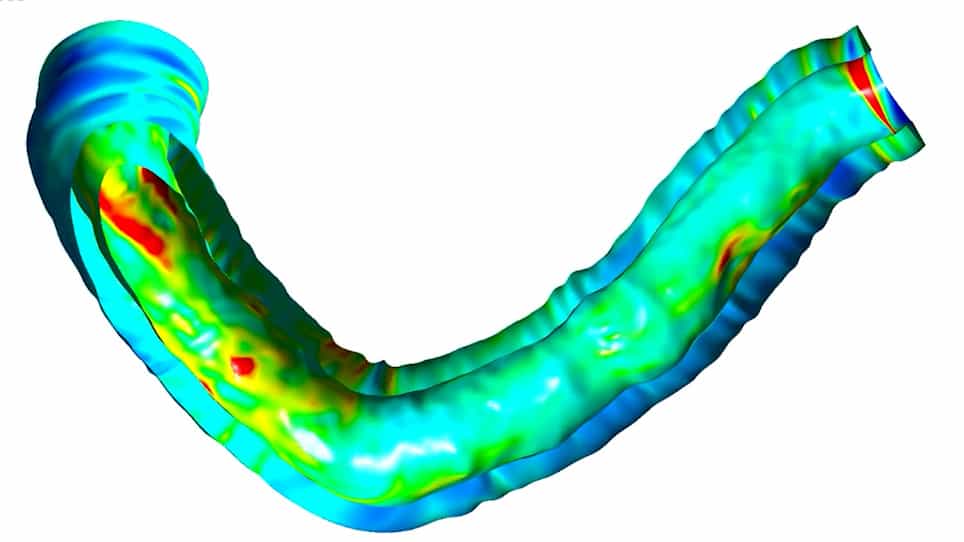

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
The Risk of Cardiovascular Diseases in Axial Spondyloarthritis. Current Insights
Eric Toussirot1,2,3,4
1INSERM CIC-1431 Centre Investigation Clinique, CHU de Besançon, Besançon, France.

Insights
Patients with axial spondyloarthritis (axSpA) face higher cardiovascular risks due to inflammation and NSAID use. Early detection and management, focusing on inflammation control and risk factors, are crucial for improving outcomes.
Area of Science:
- Rheumatology
- Cardiology
- Immunology
Background:
- Axial spondyloarthritis (axSpA) is associated with significantly increased cardiovascular (CV) risk, leading to higher CV mortality and morbidity.
- This elevated risk is attributed to a combination of traditional CV risk factors, chronic inflammation, and potentially non-steroidal anti-inflammatory drug (NSAID) use.
Purpose of the Study:
- To explore the multifaceted factors contributing to enhanced CV risk in axSpA patients.
- To discuss the role of various treatments, including NSAIDs and biologics, in modulating CV risk within this population.
- To highlight the importance of early CV risk detection and management in axSpA according to current recommendations.
Main Methods:
- Review of existing literature on cardiovascular comorbidity in axial spondyloarthritis.
- Analysis of the impact of inflammatory processes and pharmacological treatments (NSAIDs, TNF inhibitors, IL-17 inhibitors) on CV risk.
- Emphasis on non-invasive techniques for early detection of CV involvement.
Main Results:
- NSAIDs may have a detrimental effect on CV risk in axSpA, while TNF inhibitors show potential benefits, requiring further clinical validation.
- Limited data exist on CV comorbidity in non-radiographic axSpA compared to the radiographic form.
- Early, pre-clinical CV involvement in axSpA is detectable through non-invasive methods.
Conclusions:
- Current axSpA management, guided by EULAR recommendations, must integrate CV risk assessment and management.
- Rheumatologists are pivotal in identifying and managing CV risk, focusing on disease activity control, inflammation suppression, and managing traditional CV risk factors.
- Further research is needed to clarify the CV effects of IL-17 inhibitors and to gather more data on non-radiographic axSpA patients.
Abstract:
There is an increased cardiovascular (CV) risk in axial spondyloarthritis (axSpA), leading to increased CV mortality and morbidity in these patients. The factors that may explain this enhanced CV risk in axSpA are multiple, including traditional CV risk factors such as smoking, but also the inflammatory process and probably the use of non-steroidal anti-inflammatory drugs (NSAIDs). The CV involvement of axSpA may be detected at an early and pre-clinical stage, using non-invasive techniques. While NSAIDs play a deleterious role in the CV risk of axSpA, TNF inhibitors seem to have a beneficial impact, but this remains to be demonstrated in specific clinical studies. More data are needed to determine the potential effects of IL-17 inhibitors on the CV risk of axSpA. CV comorbidity has been mainly assessed in the radiographic form of axSpA, while limited data are available in patients with the non-radiographic form. The current management of axSpA must consider this CV comorbidity according to the EULAR recommendations. Rheumatologists play a determinant role in the detection of CV risk and current management of these patients is focused on the control of disease activity, suppression of inflammation, screening for and management of traditional CV risk factors, as well as the restriction of NSAID use.
More Related Videos
 04:47
Author Spotlight: Evaluating Traditional Chinese Therapy for Ankylosing Spondylitis in Mice
Published on: October 27, 2023
 12:23
Flow Cytometry Analysis of Immune Cell Subsets within the Murine Spleen, Bone Marrow, Lymph Nodes and Synovial Tissue in an Osteoarthritis Model
Published on: April 24, 2020
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:23
Rheumatic Heart Disease I: Introduction
 01:26
Atherosclerosis III: Management
 01:21
Rheumatic Heart Disease III: Medical Management
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests