Related Experiment Video
Updated: Oct 11, 2025
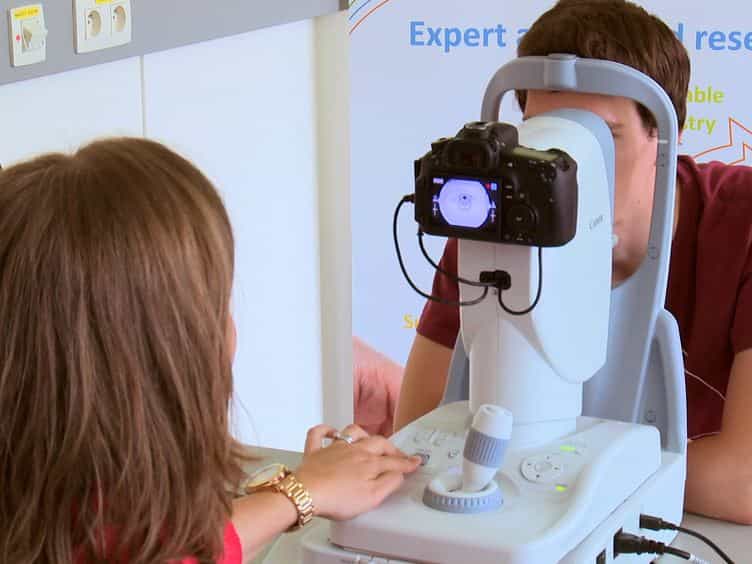
Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
Incorporation of Retinal Arteriolosclerosis into Risk Stratification of Blood Pressure Category According to the 2017
Satoshi Matsuoka1,2, Hidehiro Kaneko1,3, Tatsuya Kamon1
1The Department of Cardiovascular Medicine, The University of Tokyo.

Insights
Retinal arteriolosclerosis (RA) can improve cardiovascular disease (CVD) risk assessment in individuals classified by the 2017 ACC/AHA Blood Pressure (BP) guideline. Adding RA assessment enhances risk stratification, especially for stage 1 hypertension.
Area of Science:
- Ophthalmology
- Cardiology
- Public Health
Background:
- Cardiovascular disease (CVD) risk stratification relies on guidelines like the 2017 ACC/AHA Blood Pressure (BP) guideline.
- Retinal arteriolosclerosis (RA) is a potential indicator of systemic vascular damage.
- The utility of RA in refining CVD risk stratification within current BP guidelines is not fully established.
Purpose of the Study:
- To investigate if retinal arteriolosclerosis (RA) can enhance cardiovascular disease (CVD) risk stratification.
- To evaluate RA's role in individuals categorized by the 2017 ACC/AHA Blood Pressure (BP) guideline.
- To determine if RA presence modifies CVD risk associated with different BP categories.
Main Methods:
- A large cohort of 291,522 participants without prior CVD or BP medication use was analyzed.
- Participants were categorized into six groups based on BP levels (normal/elevated, stage 1 hypertension, stage 2 hypertension) and presence or absence of RA (Keith-Wagener-Barker grade ≥ 1).
- Multivariable Cox regression models assessed the association between BP categories, RA, and incident CVD events (MI, angina, stroke, HF) over a mean follow-up of 1,223 days.
Main Results:
- The risk of CVD events increased with higher BP categories, and this risk was significantly amplified by the presence of RA.
- Individuals with stage 1 hypertension and RA had a substantially higher hazard ratio for myocardial infarction (MI) compared to those with normal BP and no RA.
- Similar associations between RA and increased CVD risk were observed for stroke and heart failure (HF).
Conclusions:
- The presence of retinal arteriolosclerosis (RA) significantly modifies cardiovascular disease (CVD) risk stratification.
- Incorporating RA assessment can improve the accuracy of risk prediction for individuals under the 2017 ACC/AHA BP guideline.
- RA assessment is particularly valuable for refining risk in individuals classified with stage 1 hypertension.
Aim:
We investigated whether retinal arteriolosclerosis (RA) could be used for cardiovascular disease (CVD) risk stratification of individuals categorized according to the 2017 American College of Cardiology (ACC)/American Heart Association (AHA) Blood Pressure (BP) guideline.
Methods:
We studied 291,522 participants without a history of CVD and not taking any BP-lowering medications from the JMDC Claims Database. RA was defined as Keith-Wagener-Barker system grade ≥ 1. Each participant was classified into one of the six groups: (1) normal or elevated BP without RA, (2) normal or elevated BP with RA, (3) stage 1 hypertension without RA, (4) stage 1 hypertension with RA, (5) stage 2 hypertension without RA, and (6) stage 2 hypertension with RA.
Results:
Median (interquartile range) age was 46 (40-53) years, and 141,397 (48.5%) of the participants were men. During a mean follow-up of 1,223±830 days, 527 myocardial infarction (MI), 5,718 angina pectoris, 2,890 stroke, and 5,375 heart failure (HF) events occurred. Multivariable Cox regression analyses revealed that the risk of CVD increased with BP category, and this association was pronounced by the presence of RA. Compared with normal or elevated BP without RA, the hazard ratios (HRs) for MI (HR 1.17, 95% CI 0.93-1.47) were higher in stage 1 hypertension without RA. The HRs for MI further increased in stage 1 hypertension with RA (1.86 [1.17-2.95]). This association was present in stroke and HF.
Conclusion:
Incorporation of the assessment for RA may facilitate the CVD risk stratification of people classified based on the 2017 ACC/AHA BP guideline, particularly for those categorized in stage 1 hypertension.
Related Concept Videos
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:29
Hypertension II: Pathophysiology
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:28
Hypertension I: Introduction