Related Experiment Video
Updated: Oct 10, 2025
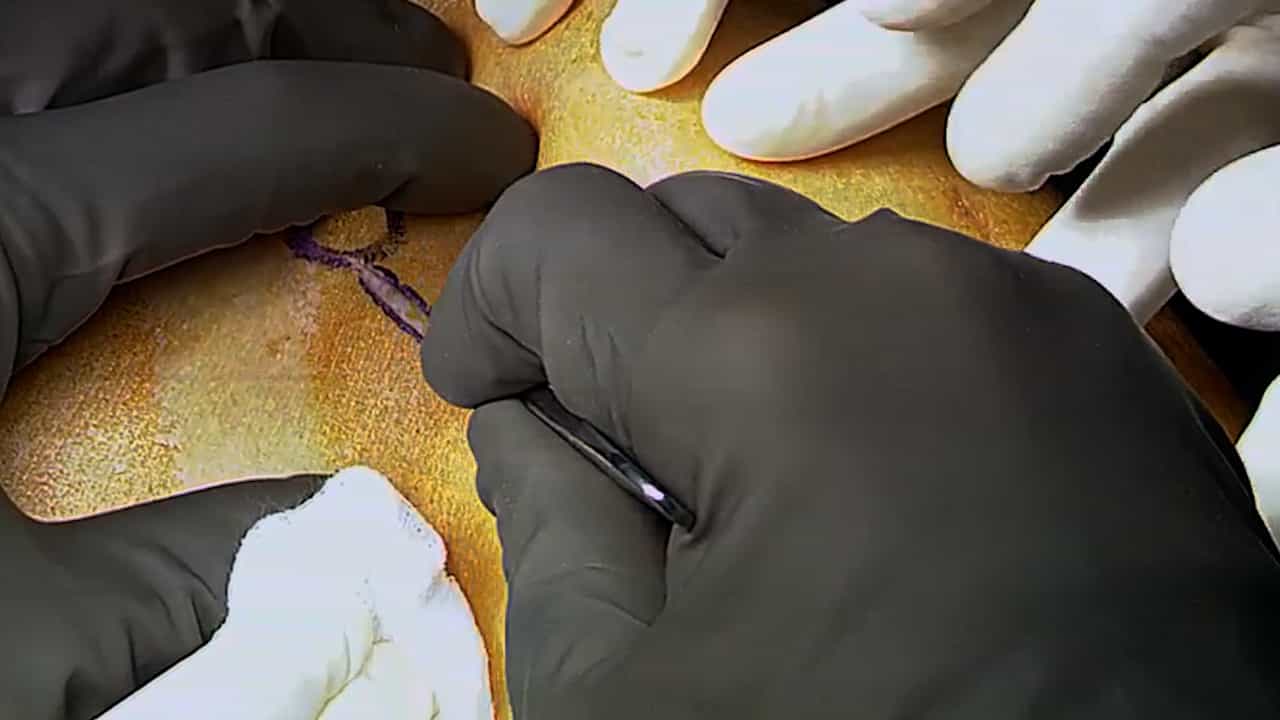

Anterior Capsular Reconstruction with Human Dermal Allograft for Irreparable Subscapularis Tears
Published on: May 9, 2025
Arthroscopic rotator cuff repair with biologically enhanced patch augmentation
Daniel P Berthold1,2, Patrick Garvin3, Michael R Mancini3
1Department of Orthopaedic Sports Medicine, Technical University of Munich, Ismaninger Str. 22, 81675, Munich, Germany. daniel.berthold@mri.tum.de.

Objective:
The purpose of this guide is to illustrate an arthroscopic rotator cuff repair (RCR) with two techniques for biologically enhanced patch augmentation.
Indications:
Massive rotator cuff tears (> 5 cm) and revision RCR.
Contraindications:
Active joint or systemic infection; severe fatty muscle atrophy; severe glenohumeral arthropathy; American Society of Anesthesiologists Physical Status (ASA PS) IV.
Surgical Technique:
Dermal allograft patch augmented with concentrated bone marrow aspirate (cBMA), platelet-rich plasma (PRP) and platelet-poor plasma (PPP); or Regeneten patch augmented with bursa, PRP, PPP, and autologous thrombin.
Postoperative Management:
A 30° abduction sling for 6 weeks; unrestricted active-assisted external rotation and forward elevation after 12 weeks; focus on restoration of scapular stability and strength.
Results:
A total of 22 patients received revision massive RCR using a dermal allograft patch enhanced with cBMA and PRP with a mean follow-up of 2.5 years (1.0-5.8 years). There was a significant improvement in the preoperative Simple Shoulder Test (SST). There was also a trend towards improved pain and American Shoulder and Elbow Surgeons (ASES) Shoulder Score. In this cohort, 45% reached the minimal clinically important difference (MCID), 41% achieved substantial clinical benefit (SCB), and 32% had a patient-acceptable symptomatic state (PASS) for the ASES score. Preliminary data using the Regeneten patch technique with bursa, PRP, PPP, and autologous thrombin was prospectively collected in five patients between 05/2020 and 03/2021 at the author's institution. Mean follow-up was 6.5 ± 1.3 (6-8 months). There was an improvement from preop to postop in pain, ASES, SANE, Constant-Murley (CM) score and active range of motion.