
Primary closure of superior partial sternal cleft in a 2-month-old girl: case report
Halil Ibrahim Tanriverdi1, Fulya Doğaneroğlu1, Abdülkadir Genç1
1Department of Pediatric Surgery, Manisa Celal Bayar University Medical School, Uncubozkoy, 45030, Yunusemre/Manisa, Turkey.

Background:
Sternal cleft is a quite rare malformation. It is seen 1 out of 100,000 live births and makes up less than 1% of all chest wall deformities, seen more often among females. The deformity can be partial or complete. Partial deformities can be superior or inferior. It is generally diagnosed at birth when paradoxical respiratory movements are seen. Patients are often asymptomatic when they are born and generally other abnormalities accompany. As sternal clefts can be repaired primarily at early ages, they are repaired using autologous or synthetic grafts in the following years. We present a 2-month-old girl with superior partial sternal cleft repaired primary and accompanying hemangiomas in this case report.
Case Presentation:
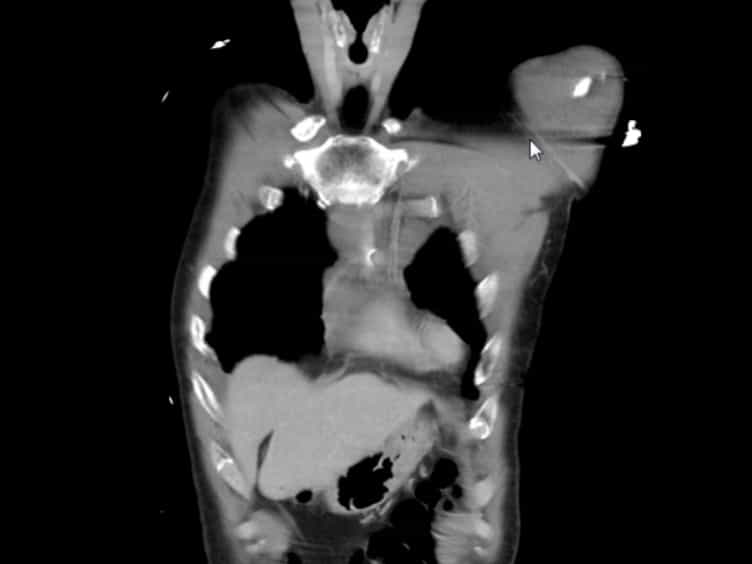
A girl who was born in another center and had a sternal cleft, who did not have any problems in the early period, was admitted to our hospital with respiratory distress at the age of 43 days. The patient was monitored with mechanical ventilator support, and there were hemangiomas around his left ear and lips. There were paradoxical respiratory movements in front of the heart, in the upper midline of the chest. Three-dimensional computed tomography showed that the upper part of the sternum did not develop, and there were hypoplasic sternal bars on both sides. It was evaluated as superior partial sternal cleft, and surgery was planned. In the operation, the sternal bars were released from the pericardium and pleura. The periosteum in the medial of both sternal bars was then released and connected in the midline, in front of the pericardium.
Conclusion:
Although neonates with a sternal cleft are asymptomatic at birth, respiratory symptoms may develop in later periods. In addition, because the structures are more flexible in the neonatal period, the primary repair of the cleft is easier and the risk of cardiac compression is lower. In our case, sternal bars could be approached primary, and no chondral grafts, patches, or steel wires were required.
More Related Videos
 20:33
A Case Series of Successful Abdominal Closure Utilizing a Novel Technique Combining a Mechanical Closure System with a Biologic Xenograft that Accelerates Wound Healing
Published on: July 4, 2019
 10:52
Closure of a Patent Foramen Ovale PFO: An Intervention Sequence
Published on: December 23, 2022
Related Concept Videos
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...