Related Experiment Video
Updated: Oct 10, 2025

Assessment of Resistance to Tyrosine Kinase Inhibitors by an Interrogation of Signal Transduction Pathways by Antibody Arrays
Published on: September 19, 2018
Resistance Profile and Structural Modeling of Next-Generation ROS1 Tyrosine Kinase Inhibitors
Clare Keddy1,2, Pushkar Shinde3, Kristen Jones1,2
1Division of Pediatric Hematology/Oncology, Department of Pediatrics, Oregon Health & Science University, Portland, Oregon.

Abstract:
ROS1 fusion proteins resulting from chromosomal rearrangements of the ROS1 gene are targetable oncogenic drivers in diverse cancers. Acquired resistance to targeted inhibitors curtails clinical benefit and response durability. Entrectinib, a NTRK/ROS1/ALK targeted tyrosine kinase inhibitor (TKI), was approved for the treatment of ROS1 fusion-positive non-small cell lung cancer (NSCLC) in 2019. In addition, lorlatinib and repotrectinib are actively being explored in the setting of treatment-naïve or crizotinib-resistant ROS1 fusion driven NSCLC. Here, we employed an unbiased forward mutagenesis screen in Ba/F3 CD74-ROS1 and EZR-ROS1 cells to identify resistance liabilities to entrectinib, lorlatinib, and repotrectinib. ROS1F2004C emerged as a recurrent entrectinib resistant mutation and ROS1G2032R was discovered in entrectinib and lorlatinib-resistant clones. Cell-based and modeling data show that entrectinib is a dual type I/II mode inhibitor, and thus liable to both types of resistant mutations. Comprehensive profiling of all clinically relevant kinase domain mutations showed that ROS1L2086F is broadly resistant to all type I inhibitors, but remains sensitive to type II inhibitors. ROS1F2004C/I/V are resistant to type I inhibitors, entrectinib and crizotinib, and type II inhibitor, cabozantinib, but retain sensitivity to the type I macrocyclic inhibitors. Development of new, more selective type II ROS1 inhibitor(s) or potentially cycling type I and type II inhibitors may be one way to expand durability of ROS1-targeted agents.
Insights
Acquired resistance to ROS1 inhibitors like entrectinib limits treatment durability in non-small cell lung cancer (NSCLC). This study identified specific ROS1 mutations conferring resistance, suggesting new therapeutic strategies involving type II inhibitors or inhibitor cycling.
Area of Science:
- Oncology
- Molecular Biology
- Genetics
Background:
- ROS1 fusions are oncogenic drivers in various cancers, particularly non-small cell lung cancer (NSCLC).
- Targeted tyrosine kinase inhibitors (TKIs) show efficacy against ROS1-driven cancers, but acquired resistance limits long-term clinical benefit.
- Entrectinib, lorlatinib, and repotrectinib are key TKIs used or investigated for ROS1-positive NSCLC.
Purpose of the Study:
- To identify novel resistance mutations to entrectinib, lorlatinib, and repotrectinib in ROS1 fusion-driven cancers.
- To understand the mechanisms of resistance to different classes of ROS1 inhibitors.
- To inform the development of next-generation inhibitors or treatment strategies to overcome resistance.
Main Methods:
- Utilized an unbiased forward mutagenesis screen in Ba/F3 cells engineered with CD74-ROS1 and EZR-ROS1 fusions.
- Exposed cells to entrectinib, lorlatinib, and repotrectinib to select for resistant clones.
- Characterized identified mutations (e.g., ROS1F2004C, ROS1G2032R, ROS1L2086F) through cell-based assays and modeling.
Main Results:
- Identified ROS1F2004C as a recurrent mutation conferring resistance to entrectinib.
- Discovered ROS1G2032R in clones resistant to both entrectinib and lorlatinib.
- Demonstrated that entrectinib acts as a dual type I/II inhibitor, susceptible to both resistance mutation types.
- Found ROS1L2086F confers broad resistance to type I inhibitors but retains sensitivity to type II inhibitors.
- Showed ROS1F2004C/I/V mutations confer resistance to type I (entrectinib, crizotinib) and type II (cabozantinib) inhibitors but remain sensitive to type I macrocyclic inhibitors.
Conclusions:
- Specific kinase domain mutations in ROS1 confer resistance to clinically relevant TKIs.
- Understanding inhibitor binding modes (type I vs. type II) is crucial for predicting resistance patterns.
- Developing selective type II ROS1 inhibitors or employing inhibitor cycling strategies may enhance treatment durability in ROS1-driven NSCLC.
More Related Videos

Related Concept Videos
 01:26
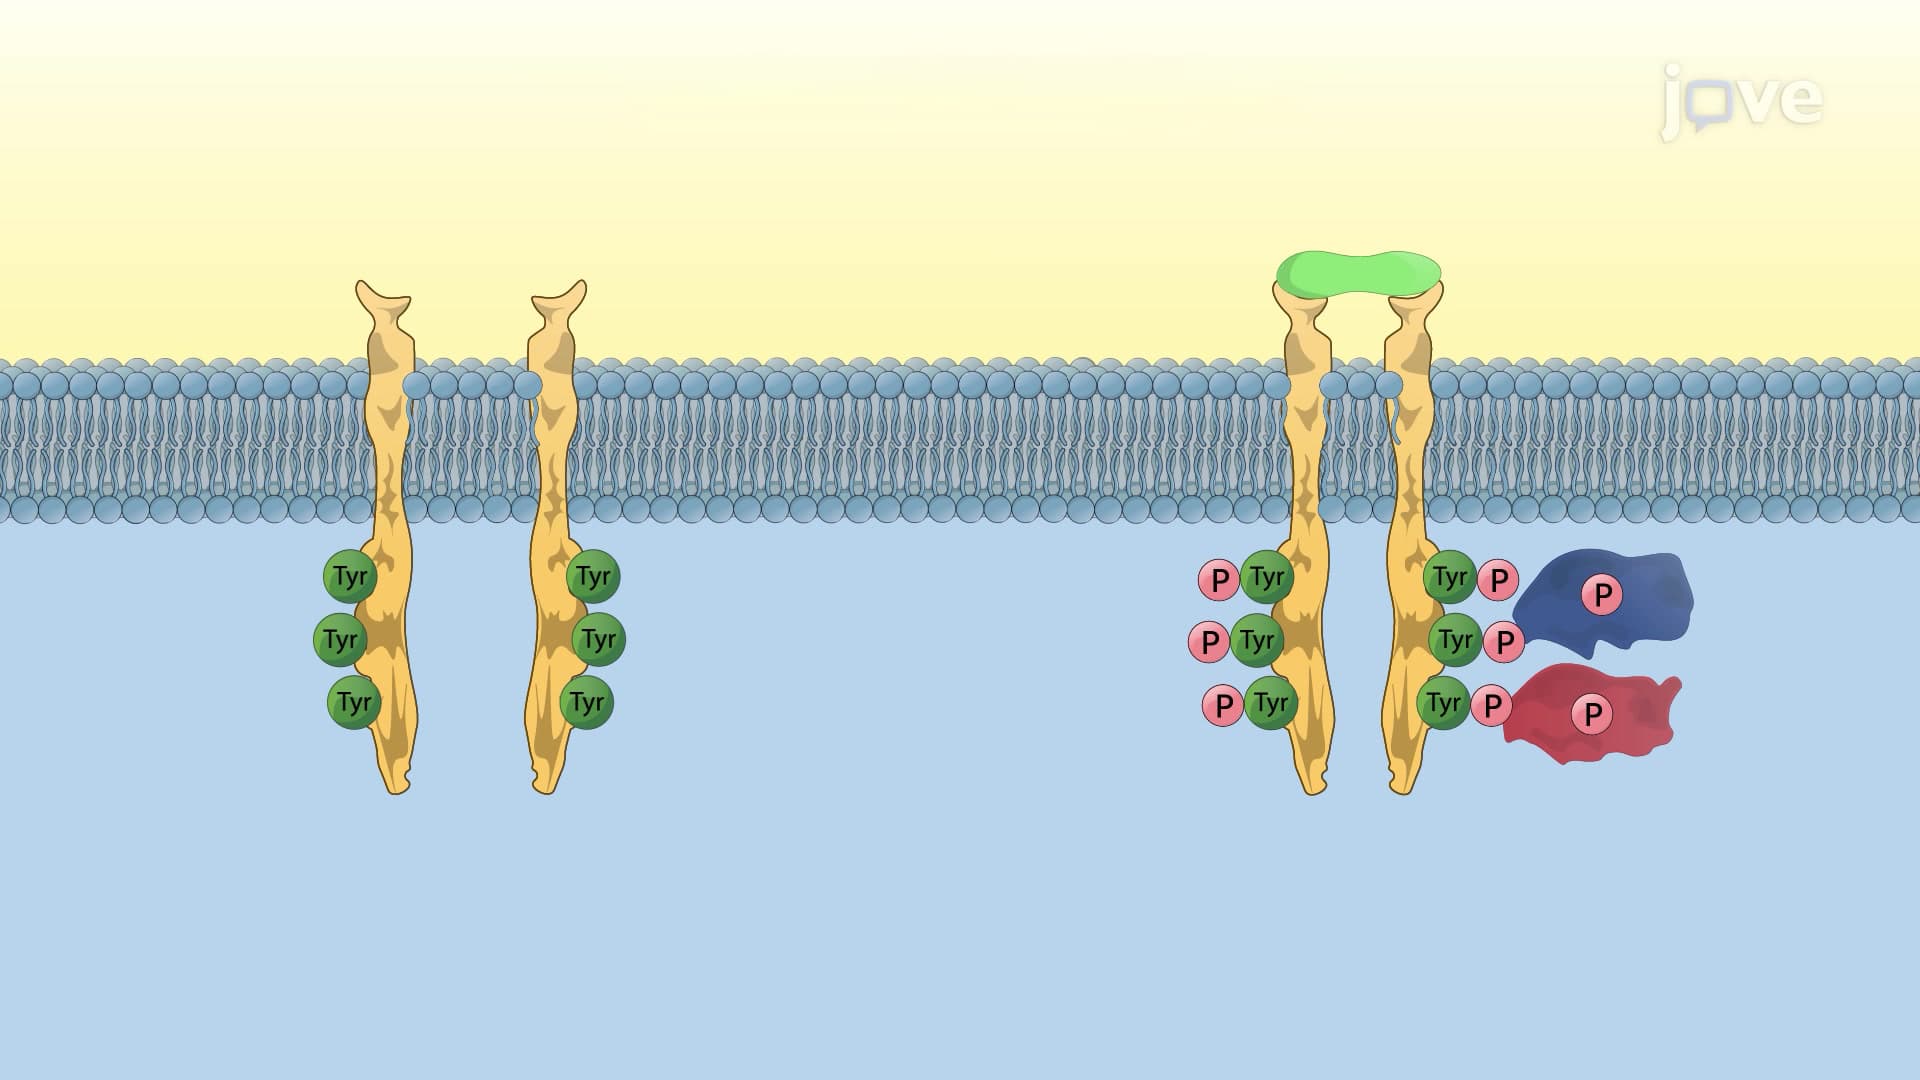
Receptor Tyrosine Kinases
 01:28
Structure-Activity Relationships and Drug Design
SAR studies the intricate relationship between a drug's chemical structure and biological activity. It focuses on understanding how modifications to a drug's structure can influence...