Related Experiment Video
Updated: Oct 9, 2025
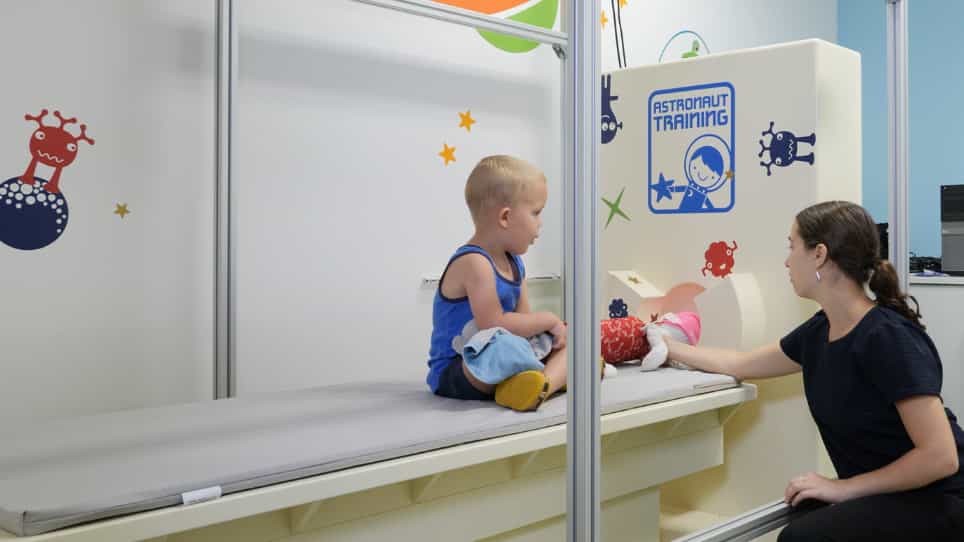

Studying Brain Function in Children Using Magnetoencephalography
Published on: April 8, 2019
School-aged children diagnosed with an FASD exhibit visuo-cortical network disturbance: A magnetoencephalography
Zinia Pervin1, John F L Pinner2, Lucinda Flynn2
1The Mind Research Network, A Division of Lovelace Biomedical Research Institute, Albuquerque, NM 87106, United States; Department of Biomedical Engineering, University of New Mexico, Albuquerque, NM 87131, United States.

Insights
Children with fetal alcohol spectrum disorders (FASD) show delayed visual responses and reduced neural activation. These brain differences, particularly with peripheral stimuli, may contribute to cognitive processing issues in FASD.
Area of Science:
- Neuroscience
- Developmental Psychology
- Medical Imaging
Background:
- Prenatal alcohol exposure (PAE) can lead to lifelong cognitive and neurobehavioral issues, often diagnosed as fetal alcohol spectrum disorders (FASD).
- Magnetoencephalography (MEG) offers high temporal precision for studying neural processing and functional connectivity, crucial for understanding developmental disorders.
- Visual perception impairments in children with FASD can significantly impact intellectual functioning and behavioral development during school years.
Purpose of the Study:
- To investigate visual processing in school-aged children with FASD using magnetoencephalography (MEG).
- To identify specific differences in visual evoked fields (latency and amplitude) between children with and without FASD.
Main Methods:
- Fifty children aged 8-13 years (with and without FASD) underwent MEG while performing a prosaccade task with central and peripheral visual stimuli.
- Source analysis using minimum norm estimation (MNE) was applied to MEG data.
- Visual evoked field latency and amplitude were measured in primary and visual association areas.
Main Results:
- Children with FASD exhibited delayed visual response latency in primary and visual association areas, significantly pronounced for peripheral stimuli (p ≤ 0.01).
- Reduced amplitude of visual evoked responses was observed in children with FASD for central stimuli (p ≤ 0.006).
- Impairments were noted across multiple visual areas, with peripheral stimuli revealing more prominent delays.
Conclusions:
- Children with FASD demonstrate significant visual processing deficits, including delayed responses to peripheral stimuli and reduced neural activation to central stimuli.
- These sensory processing abnormalities may underlie slower cognitive processing speeds due to intra-cortical network disturbances in children with FASD.
Abstract:
Children with prenatal alcohol exposure (PAE) often suffer from cognitive and neurobehavioral dysfunction throughout their lives, which may rise to a level of concern such that children receive a diagnosis under the fetal alcohol spectrum disorders (FASD) umbrella. Magnetoencephalography (MEG) contributes direct insight into neural processing and functional connectivity measures with temporal precision to understand cortical processing disorders that manifest during development. The impairment of perception may become more consequential among school-aged children with an FASD in the process of intellectual functioning and behavioral maturation. Fifty participants with the age range of 8-13 years participated in our study following parental informed consent and child assent. For each participant, visual responses were recorded using magnetoencephalography (MEG) while performing a prosaccade task with central stimuli (fovea centralis) and peripheral stimuli (left and right of central) presented on a screen, requiring participants to shift their gaze to the stimuli. After source analysis using minimum norm estimation (MNE), we investigated visual responses from each participant by measuring the latency and amplitude of visual evoked fields. Delayed peak latency of the visual response was identified in the primary visual area (calcarine fissure) and visual association areas (v2, v3) in young children with an FASD for both stimulus types (central and peripheral). But the difference in visual response latency was only statistically significant (p ≤ 0.01) for the peripheral (right) stimulus. We also observed reduced amplitude (p ≤ 0.006) of visual evoked response in children with an FASD for the central stimulus type in both primary and visual association areas. Multiple visual areas show impairment in children with an FASD, with visual delay and conduction disturbance more prominent in response to peripheral stimuli. Children with an FASD also exhibit significantly reduced amplitude of neural activation to central stimuli. These sensory deficits may lead to slow cognitive processing speed through continued intra-cortical network disturbance in children with an FASD.

