Related Experiment Video
Updated: Oct 9, 2025
Intravenous Microinjections of Zebrafish Larvae to Study Acute Kidney Injury
Published on: August 4, 2010
Exposure to an Extended-Interval, High-Dose Gentamicin Regimen in the Neonatal Period Is Not Associated With
Veronika Rypdal1,2, Sondre Jørandli3, Dagny Hemmingsen2,4
1Department of Pediatrics and Adolescence Medicine, University Hospital of North Norway, Tromsø, Norway.

Insights
Neonatal gentamicin exposure, even at high doses, did not show signs of kidney damage in schoolchildren. This study suggests the gentamicin regimen is safe for long-term kidney health in children.
Area of Science:
- Pediatric Nephrology
- Neonatal Pharmacology
- Clinical Toxicology
Background:
- Gentamicin is a critical antibiotic for neonatal infections.
- High-dose gentamicin regimens are sometimes necessary but raise concerns about potential long-term kidney toxicity.
- Assessing subclinical nephrotoxicity in school-aged children post-neonatal exposure is crucial for evaluating treatment safety.
Purpose of the Study:
- To evaluate the association between neonatal high-dose gentamicin exposure and subclinical nephrotoxicity in school-aged children.
- To identify potential long-term kidney injury using validated urine biomarkers and blood pressure measurements.
Main Methods:
- A cohort of 222 children exposed to three or more doses of gentamicin (6 mg/kg) as neonates was followed up in school age.
- Urine biomarkers including protein-creatinine ratio (PCR), albumin-creatinine ratio (ACR), kidney injury molecule-1 (KIM-1), and N-acetyl-beta-D-glucosaminidase (NAG-Cr) were assessed.
- Logistic, linear, and non-parametric kernel regression analyses were used to correlate gentamicin exposure (cumulative dose and trough plasma concentration) with biomarker levels.
Main Results:
- Only 6.8% of children (15 out of 222) exhibited one or two marginally abnormal urine biomarker values.
- No significant differences in gentamicin exposure, gestational age, or birth weight were found between children with abnormal versus normal biomarker results.
- Regression analyses revealed no association between gentamicin exposure metrics (cumulative dose or TPC) and urine biomarker values.
Conclusions:
- Extended-interval, high-dose gentamicin regimens in neonates were not associated with subclinical nephrotoxicity in school-aged children.
- The studied gentamicin treatment regimen appears safe concerning long-term kidney health.
- Further research may explore other potential long-term effects or specific subgroups if any.
Abstract:
Objectives: To assess the association between gentamicin exposure and subclinical signs of nephrotoxicity in school children who were exposed to a high-dose gentamicin regimen in the neonatal period. Methods: Children receiving three or more doses (6 mg/kg) of gentamicin as neonates were invited to a follow-up in school age. We evaluated potential signs of subclinical nephrotoxicity with four validated urine biomarkers: protein-creatinine ratio (PCR), albumin-creatinine ratio (ACR), kidney injury molecule-1 (KIM-1), and N-acetyl-beta-D-glucosaminidase (NAG) normalized for urine creatinine (NAG-Cr). In addition, blood pressure was measured. The measures of gentamicin exposure were cumulative dose (mg/kg) and highest trough plasma concentration (TPC) in mg/L. We used logistic and linear regression and non-parametric kernel regression to analyze the relationship between gentamicin exposure and the urine biomarkers. Results: A total of 222 gentamicin exposed children were included. As neonates, the children were exposed to a median (interquartile range-IQR) cumulative gentamicin dose of 36 (26-42) mg/kg and the median (IQR) TPC was 1.0 (0.7-1.3) mg/L. At follow-up, 15 children (6.8%) had either one abnormal urine biomarker value (13 children) or two abnormal urine biomarker values (2 children). These 17 biomarker values were all marginally above the suggested upper cutoff, and included the following markers; KIM-1 (n = 2), NAC-Cr (n = 5), ACR (n = 6), and PCR (n = 4). All other 207 children had normal sets of all four urine biomarkers. One child had hypertension. There were no differences in gentamicin exposure, gestational age (GA) at birth or birth weight between the group of 15 children with one or two abnormal urine biomarker values compared to the other 207 children who had normal biomarker values. Using different regression analyses, we did not find any association between gentamicin exposure (cumulative dose and/or TPC) and the urine biomarker values. Conclusions: Exposure to an extended-interval, high-dose gentamicin regimen in the neonatal period was not associated with signs of subclinical nephrotoxicity in schoolchildren. We therefore suggest that the gentamicin treatment regimen evaluated in this study is safe in terms of long-term nephrotoxicity. Clinical Trial Registration: ClinicalTrials.gov, identifier: NCT03253614.

Related Concept Videos
 01:15
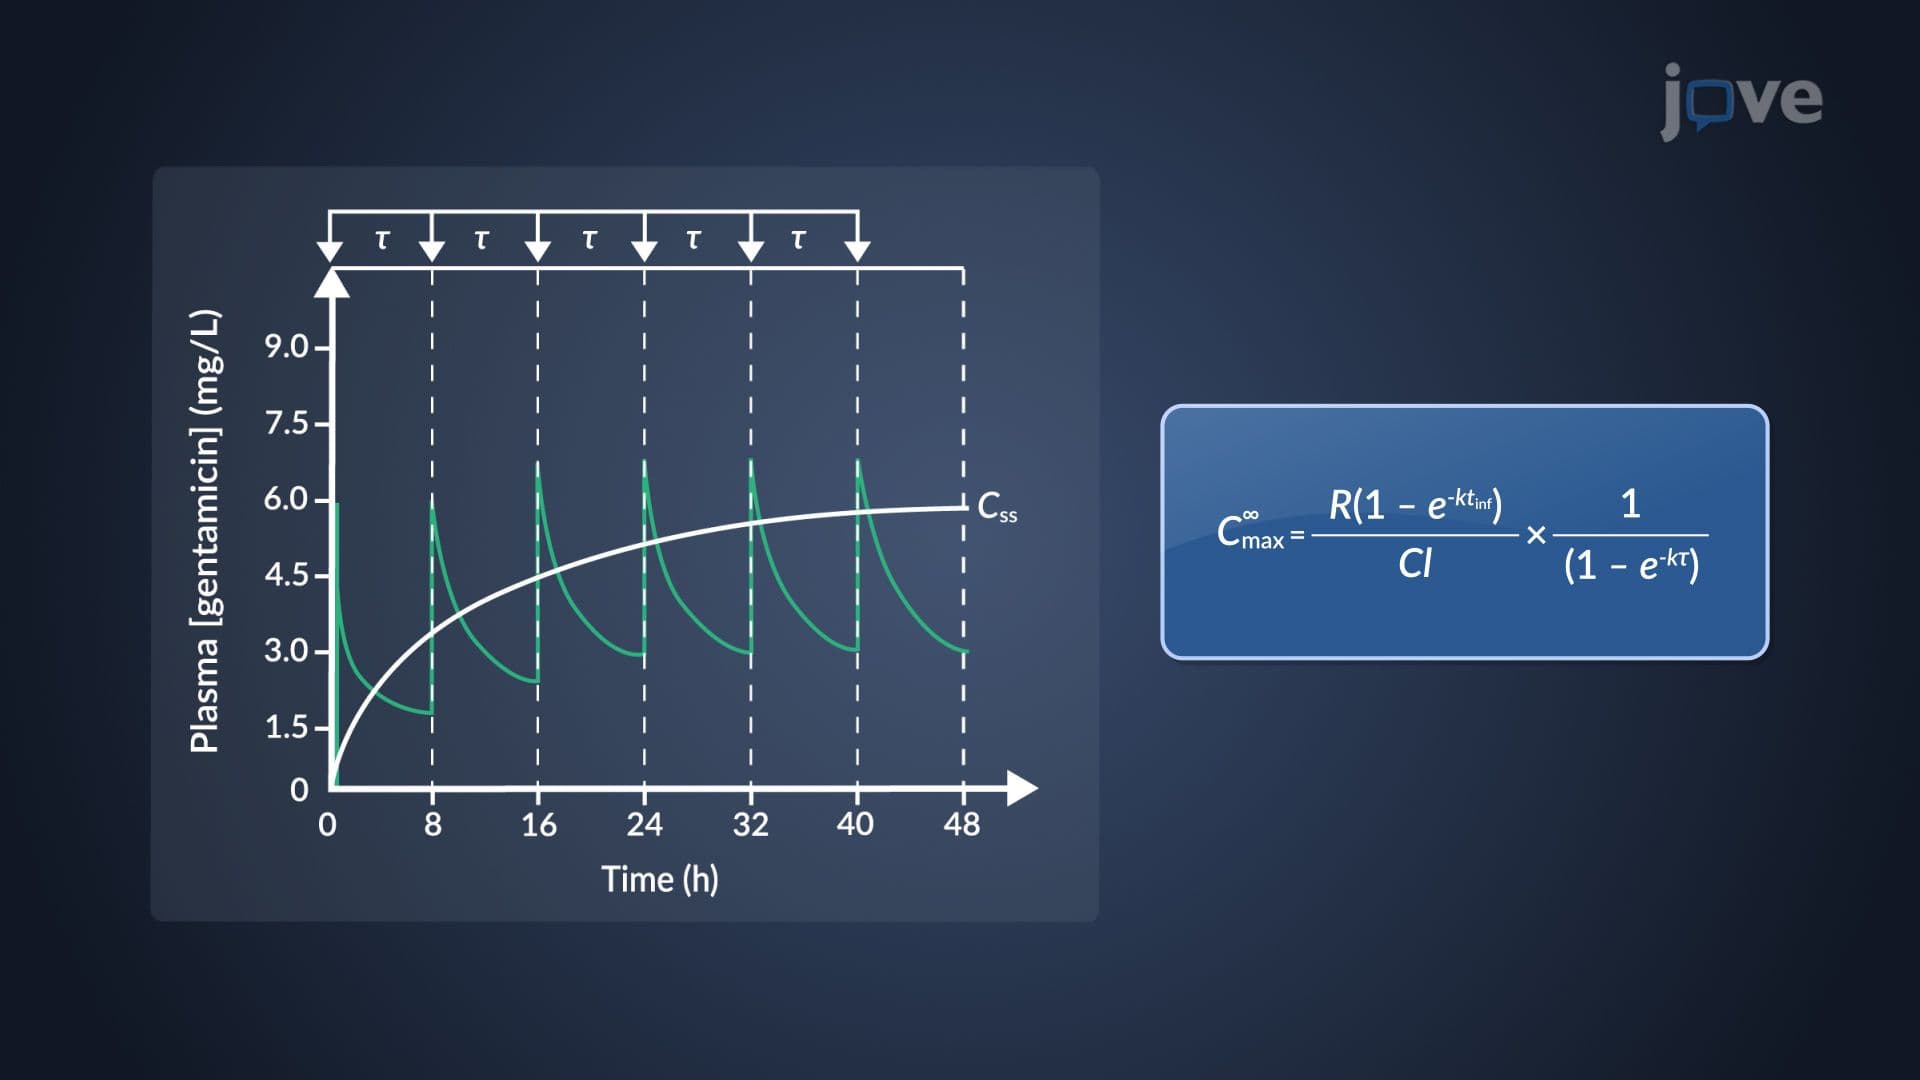
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:20
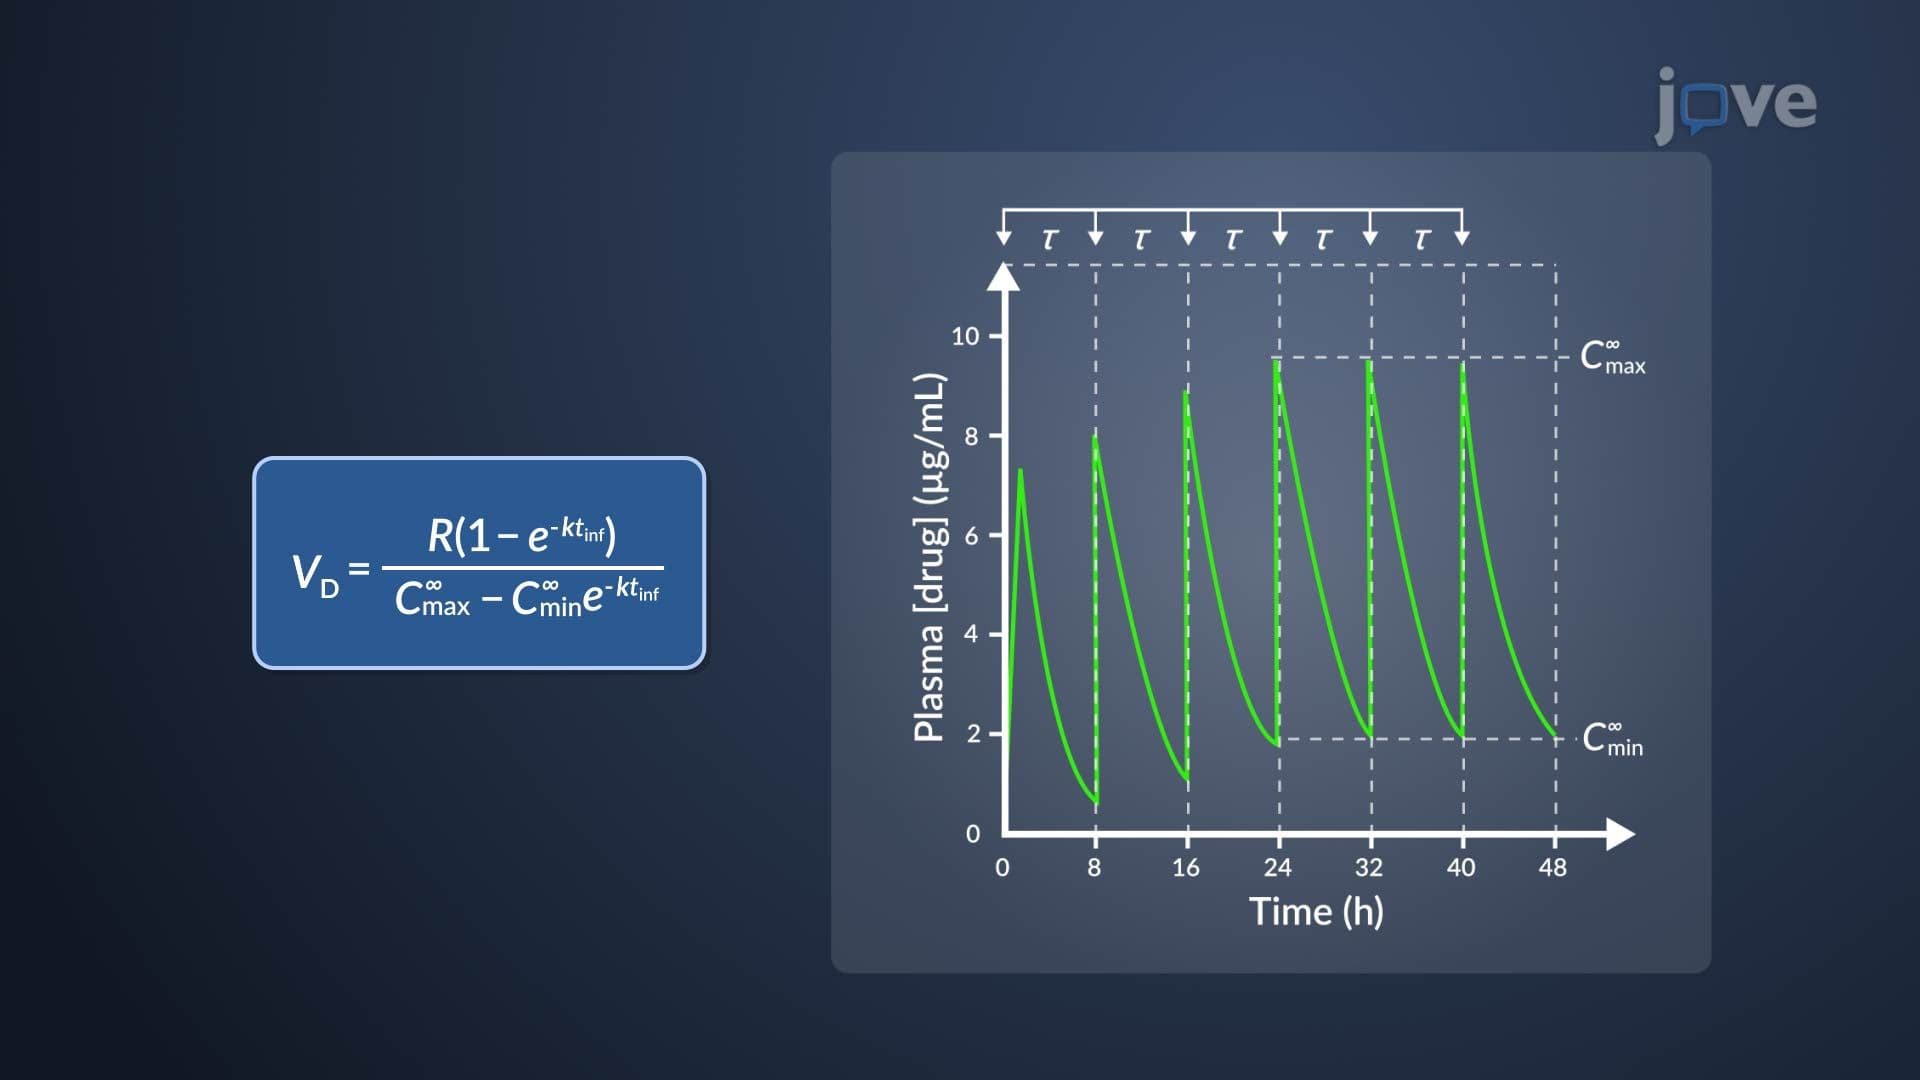
Estimation of k and VD of Aminoglycosides
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion