Related Experiment Video
Updated: Oct 9, 2025
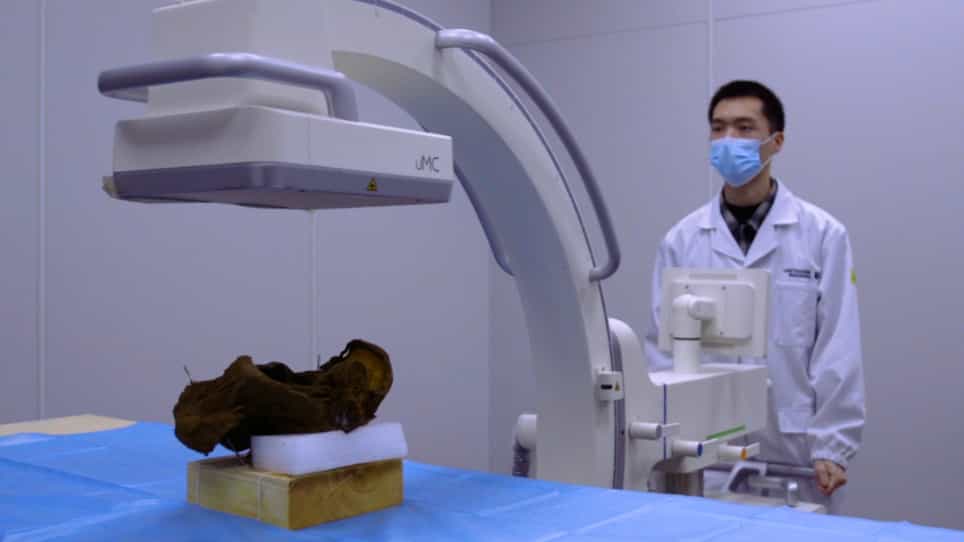

A Teleoperated Robotic System-Assisted Percutaneous Transiliac-Transsacral Screw Fixation Technique
Published on: January 6, 2023
Trauma transfers discharged from the emergency department-Is there a role for telemedicine?
Lindsay J Lindsey1, Lindsey S Rasmussen, Landon S Hendrickson
1From the Department of Surgery (L.J.L., K.E.S., R.O.K., A.C., R.M.A., A.M.C.), University of Oklahoma Health Sciences Center; Trauma Program (L.S.R.), University of Oklahoma Medical Center, OU Health; and University of Oklahoma College of Medicine (L.S.H., E.S.F., S.P.B.), Oklahoma City, OK.

Background:
As the only Level I trauma center in the state, our hospital has seen an increase in the number of traumas requiring transfer for a higher level of care, placing strain on an already strained health care system. Traumas that are transferred to our facility and subsequently discharged back home indicate a subset of patients who may not be appropriate to transfer. The aim of this study is to identify commonalities between patients who were transferred for a higher level of care but do not require inpatient status and to assess patients who may benefit from a telemedicine evaluation.
Methods:
A 2-year retrospective review of a prospective collected database of patients who were discharged from the ED following transfer to a Level I trauma center was conducted. Data included demographics, injuries, transferring facility, method of transport, activation criteria and level, additional imaging, consulting services, procedures, and disposition.
Results:
A total of 2,350 patients were transferred. Of those, 27% (632/2,350) were discharged home directly from the trauma bay. Of those patients, 36% (230/632) required complex bedside intervention or subspecialty consultation prior to discharge including complex laceration repairs 53%, ophthalmology examination 24%, splinting 18%, and joint reduction 5%. Sixty-four percent (402/632) of patients did not require complex bedside procedures prior to discharge. One hundred twenty hospitals transferred patients to our center during this period. The top 10 transferring facilities accounted for 40% (948/2,350) of our transfer volume.
Conclusion:
Our study demonstrates that patients who are transferred to our facility and subsequently discharged have a common pattern of injuries; typically, isolated hand and face/ophthalmology. This is likely attributed to the lack of resources in rural facilities to evaluate and develop treatment plans for these injuries; however, only 36% of discharged patients required a bedside procedure. Excluding Level I traumas, head and spine injuries, and patients requiring complex bedside procedures, there was a 13% inappropriate rate of transfer (310/2,350). Development and implementation of a telemedicine system could potentially reduce the transfer and ED discharge rate, thereby improving efficiency and allowing for reallocation of resources as appropriate.
Level Of Evidence:
Prognostic and Epidemiologic, Level III.


Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Types of Reports III: Telephone and Verbal Reports
Here's an overview of each type:
Telephone Orders
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:11
Secondary Healthcare System