Related Experiment Video
Updated: Oct 9, 2025


Full-root Aortic Valve Replacement by Stentless Aortic Xenografts in Patients with Small Aortic Roots
Published on: May 21, 2017
Impact of blood pressure on coronary perfusion and valvular hemodynamics after aortic valve replacement
Brennan J Vogl1, Yousef M Darestani2, Scott M Lilly3
1Department of Biomedical Engineering, Michigan Technological University, Houghton, Michigan, USA.

Insights
Lowering blood pressure (BP) after aortic valve replacement (AVR) can reduce coronary flow (CF) below physiological limits, even within guideline targets. Further research is needed to determine optimal BP management post-AVR.
Area of Science:
- Cardiovascular research
- Medical device engineering
- Hemodynamics
Background:
- Lower systolic and diastolic blood pressures (SBP/DBP) post-aortic valve replacement (AVR) are linked to increased mortality.
- Current guidelines suggest SBP < 120-130 mmHg and DBP < 80 mmHg, but the impact on coronary perfusion is unclear.
Purpose of the Study:
- To evaluate the effect of varying blood pressures on coronary perfusion and hemodynamics after aortic valve replacement.
- To compare the performance of different prosthetic aortic valves under simulated physiological conditions.
Main Methods:
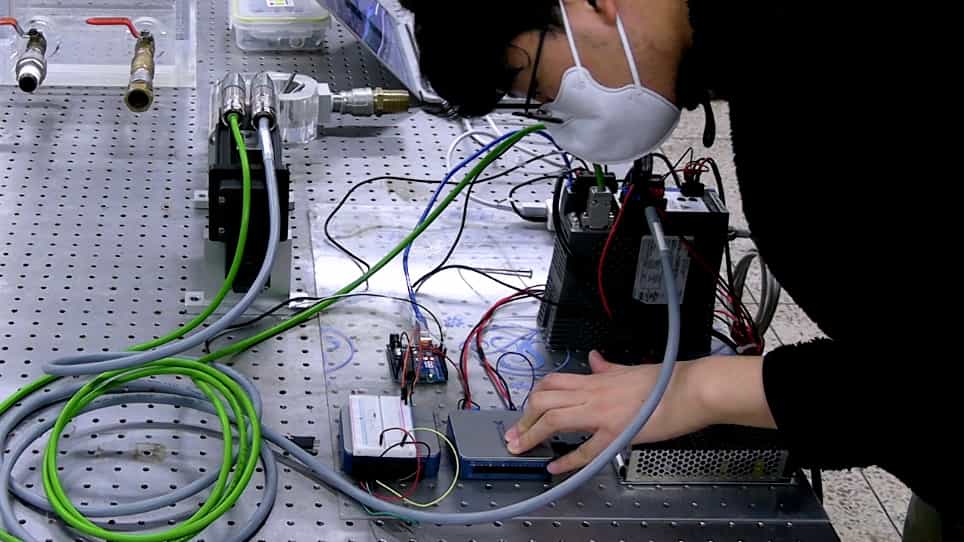
- Hemodynamic assessment of SAPIEN 3 transcatheter aortic valve (TAV), Evolut R TAV, and Magna Ease surgical aortic valve (SAV) in a pulsed left heart simulator.
- Simulations were conducted at varying SBP, DBP, and heart rates (60 and 120 bpm) with a constant cardiac output of 5 L/min.
- Calculated average coronary flow (CF), effective orifice areas (EOAs), and valvulo-arterial impedance (Zva).
Main Results:
- Coronary flow (CF) dropped below physiological limits at SBP < 120 mmHg and DBP < 60 mmHg for several valves at 60 bpm.
- Valvulo-arterial impedance (Zva) increased and effective orifice areas (EOAs) decreased with rising SBP and DBP.
- These trends were consistent at 120 bpm, with valve-dependent variations in CF reduction.
Conclusions:
- In vitro testing showed prosthetic aortic valves can lead to inadequate coronary flow when blood pressure is within target ranges.
- Findings highlight the critical need for further investigation into optimal blood pressure management strategies for patients post-aortic valve replacement.
Objective:
Our objective was to evaluate the impact of various blood pressures (BPs) on coronary perfusion and valvular hemodynamics following aortic valve replacement (AVR).
Background:
Lower systolic and diastolic (SBP/DBP) pressures from the recommended optimal target range of SBP < 120-130 mmHg and DBP < 80 mmHg after AVR have been independently associated with increased cardiovascular and all-cause mortality.
Methods:
The hemodynamic assessment of a 26 mm SAPIEN 3 transcatheter aortic valve (TAV), 29 mm Evolut R TAV, and 25 mm Magna Ease surgical aortic valve (SAV) was performed in a pulsed left heart simulator with varying SBP, DBP, and heart rate (HR) conditions (60 and 120 bpm) at 5 L/min cardiac output (CO). Average coronary flow (CF), effective orifice areas (EOAs), and valvulo-arterial impedance (Zva) were calculated.
Results:
At HR of 60 bpm, at SBP < 120 mmHg and DBP < 60 mmHg, CF decreased below the physiological lower limit with several different valves. Zva and EOA were found to increase and decrease respectively with increasing SBP and DBP. The same results were found with an HR of 120 bpm. The trends of CF variation with BP were similar in all valves however the drop below the lower physiological CF limit was valve dependent.
Conclusion:
In a controlled in vitro system, with different aortic valve prostheses in place, CF decreased below the physiologic minimum when SBP and DBP were in the range targeted by blood pressure guidelines. Combined with recent observations from patients treated with AVR, these findings underscore the need for additional studies to identify the optimal BP in patients treated with AVR for AS.

Related Concept Videos
 01:17
Aortic Regurgitation IV: Nursing Management
 01:25
Aortic Regurgitation III: Medical Management
 01:15
Aortic Regurgitation I: Introduction
 01:17
Measurement of Blood Pressure
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:23
Assessment of blood pressure in brachial artery(two-step method)