Related Experiment Video
Updated: Oct 8, 2025


Author Spotlight: Assessment of Cardiac Output Calculation by Thermodilution in Pigs for Effective Perfusion Flow During EVLP
Published on: June 28, 2024
Noninvasive echocardiographic cardiac power output predicts mortality in cardiac intensive care unit patients
Barry Burstein1, Vidhu Anand2, Bradley Ternus3
1Division of Pulmonary and Critical Care Medicine, Mayo Clinic, Rochester, MN.

Insights
Non-invasive echocardiographic cardiac power output (CPO) measurement can predict mortality in cardiac intensive care unit (CICU) patients. Higher CPO is linked to lower hospital mortality, especially in those with high lactate or vasopressor needs.
Area of Science:
- Cardiology
- Intensive Care Medicine
- Echocardiography
Background:
- Low cardiac power output (CPO), invasively measured, identifies critically ill patients at high risk.
- The study investigated the utility of non-invasive, echocardiographic CPO measurement in cardiac intensive care unit (CICU) patients.
Purpose of the Study:
- To determine if non-invasive echocardiographic CPO measurement is associated with mortality in CICU patients.
- To assess the prognostic value of echocardiographic CPO in a large cohort of critically ill cardiac patients.
Main Methods:
- Retrospective evaluation of 5,585 CICU patients (2007-2018) with echocardiography.
- Multivariable logistic regression used to analyze the association between CPO and adjusted hospital mortality.
Main Results:
- Mean CPO was 1.04 ± 0.37 W; 7.5% in-hospital mortality.
- Higher CPO was inversely associated with hospital mortality (OR 0.960 per 0.1 W, P = .03).
- This association held for patients with acute coronary syndrome, heart failure, and cardiogenic shock; mortality was highest with low CPO, reduced LVEF, vasopressors, or high lactate.
Conclusions:
- Echocardiographic CPO is inversely associated with hospital mortality in CICU patients.
- Routine calculation of CPO in CICU echocardiograms is recommended, particularly for high-risk patients.
Background:
Low cardiac power output (CPO), measured invasively, can identify critically ill patients at increased risk of adverse outcomes, including mortality. We sought to determine whether non-invasive, echocardiographic CPO measurement was associated with mortality in cardiac intensive care unit (CICU) patients.
Methods:
Patients admitted to CICU between 2007 and 2018 with echocardiography performed within one day (before or after) admission and who had available data necessary for calculation of CPO were evaluated. Multivariable logistic regression determined the relationship between CPO and adjusted hospital mortality.
Results:
A total of 5,585 patients (age of 68.3 ± 14.8 years, 36.7% female) were evaluated with admission diagnoses including acute coronary syndrome (ACS) in 56.7%, heart failure (HF) in 50.1%, cardiac arrest (CA) in 12.2%, shock in 15.5%, and cardiogenic shock (CS) in 12.8%. The mean left ventricular ejection fraction (LVEF) was 47.3 ± 16.2%, and the mean CPO was 1.04 ± 0.37 W. There were 419 in-hospital deaths (7.5%). CPO was inversely associated with the risk of hospital mortality, an association that was consistent among patients with ACS, HF, and CS. On multivariable analysis, higher CPO was associated with reduced hospital mortality (OR 0.960 per 0.1 W, 95CI 0.0.926-0.996, P = .03). Hospital mortality was particularly high in patients with low CPO coupled with reduced LVEF, increased vasopressor requirements, or higher admission lactate.
Conclusions:
Echocardiographic CPO was inversely associated with hospital mortality in unselected CICU patients, particularly among patients with increased lactate and vasopressor requirements. Routine calculation and reporting of CPO should be considered for echocardiograms performed in CICU patients.
More Related Videos
 08:19
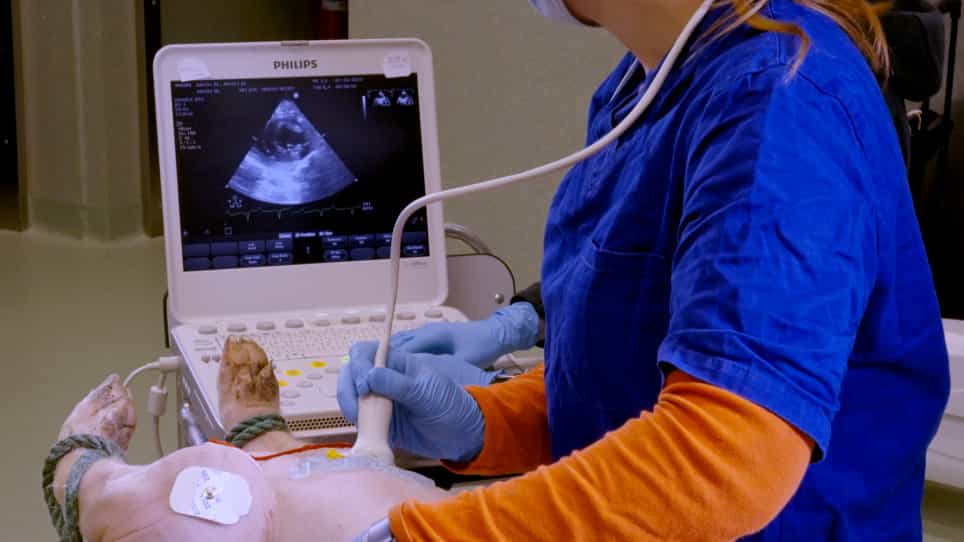
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
 03:40
Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
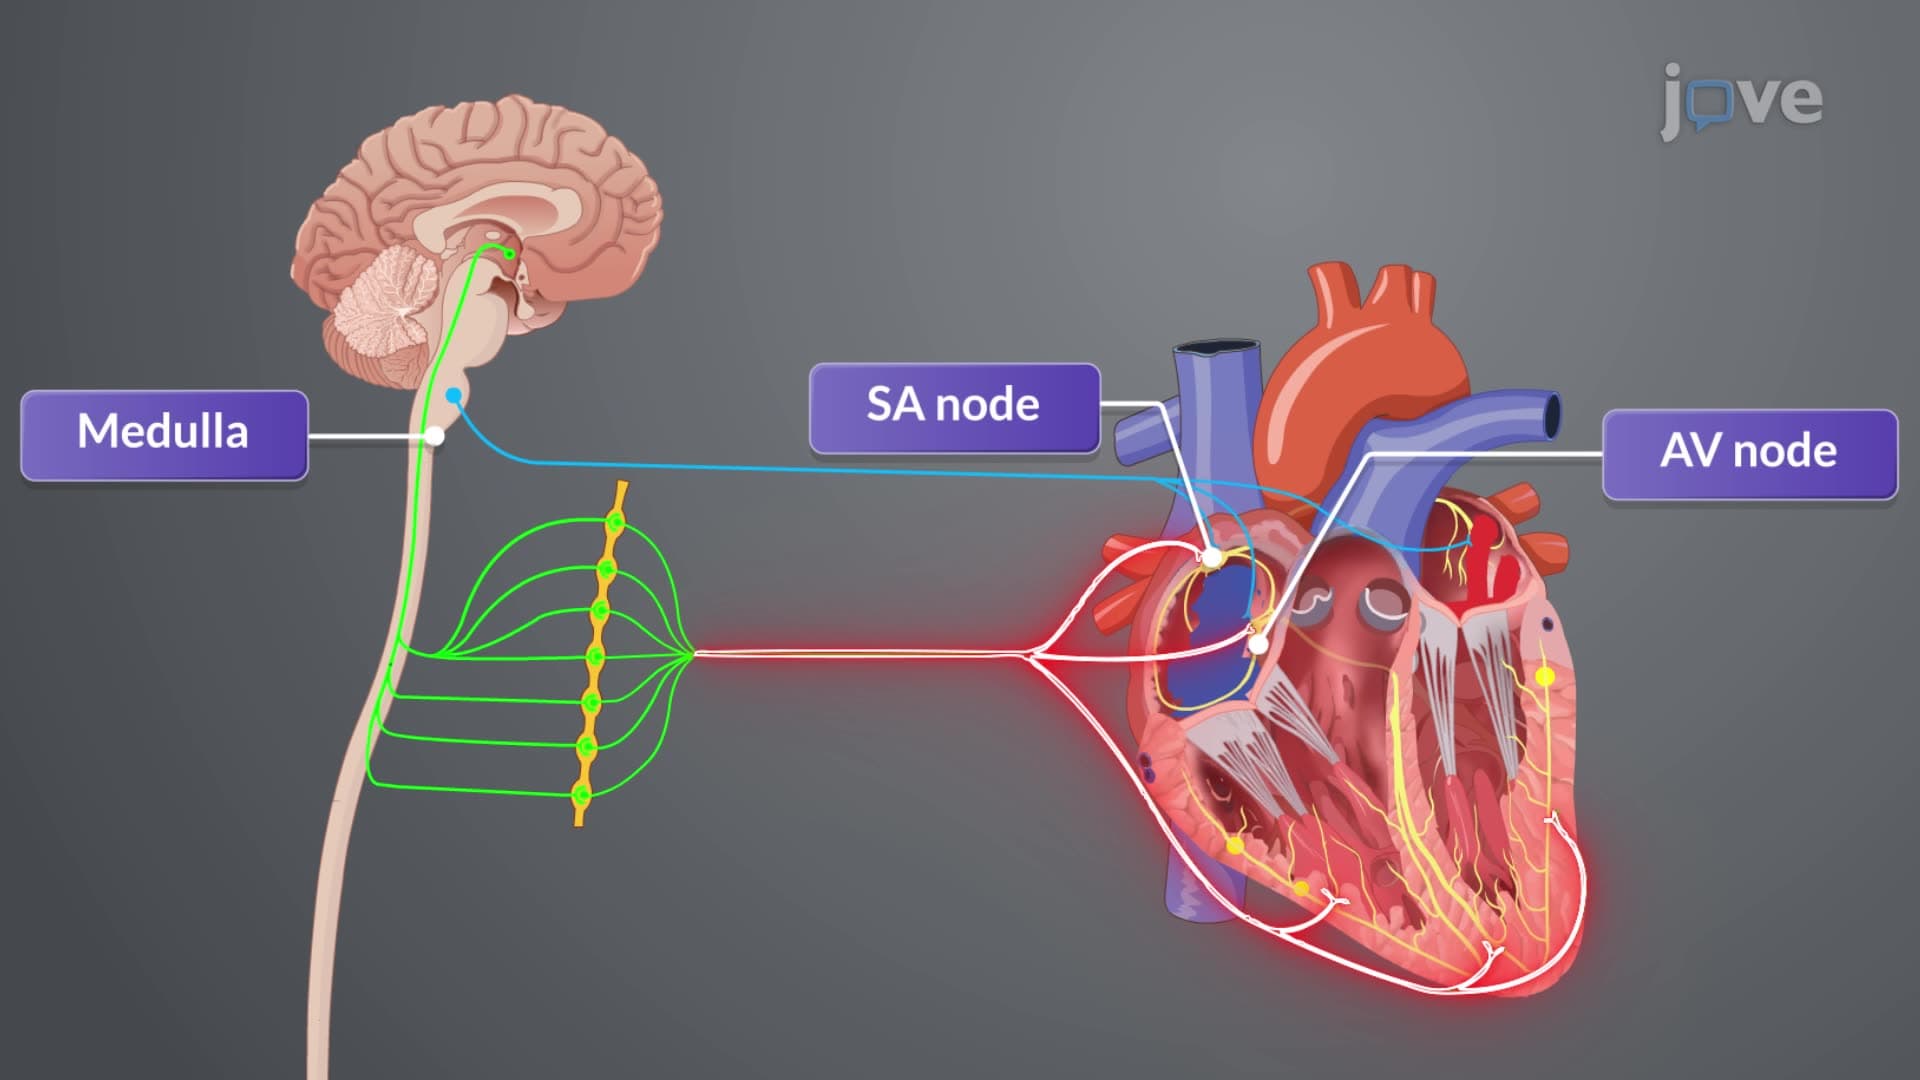
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...