Related Experiment Video
Updated: Oct 8, 2025


Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Risk Estimation of Infectious and Inflammatory Disorders in Hospitalized Patients With Acute Ischemic Stroke Using
Junhong Li1, Jingjing Huang1, Tingting Pang2
1Department of Neurology, The First Affiliated Hospital of Guangxi University of Chinese Medicine, Nanning, China.

Abstract:
Background: Infections after acute ischemic stroke are common and likely to complicate the clinical course and negatively affect patient outcomes. Despite the development of various risk factors and predictive models for infectious and inflammatory disorders (IAID) after stroke, more objective and easily obtainable predictors remain necessary. This study involves the development and validation of an accessible, accurate nomogram for predicting in-hospital IAID in patients with acute ischemic stroke (AIS). Methods: A retrospective cohort of 2,257 patients with AIS confirmed by neurological examination and radiography was assessed. The International Statistical Classification of Diseases and Health related Problem's definition was used for IAID. Data was obtained from two hospitals between January 2016 and March 2020. Results: The incidence of IAID was 19.8 and 20.8% in the derivation and validation cohorts, respectively. Using an absolute shrinkage and selection operator (LASSO) algorithm, four biochemical blood predictors and four clinical indicators were optimized from fifty-five features. Using a multivariable analysis, four predictors, namely age (adjusted odds ratio, 1.05; 95% confidence interval [CI], 1.038-1.062; p < 0.001), comatose state (28.033[4.706-536.403], p = 0.002), diabetes (0.417[0.27-0.649], p < 0.001), and congestive heart failure (CHF) (5.488[2.451-12.912], p < 0.001) were found to be risk factors for IAID. Furthermore, neutrophil, monocyte, hemoglobin, and high-sensitivity C-reactive protein were also found to be independently associated with IAID. Consequently, a reliable clinical-lab nomogram was constructed to predict IAID in our study (C-index value = 0.83). The results of the ROC analysis were consistent with the calibration curve analysis. The decision curve demonstrated that the clinical-lab model added more net benefit than either the lab-score or clinical models in differentiating IAID from AIS patients. Conclusions: The clinical-lab nomogram predicted IAID in patients with acute ischemic stroke. As a result, this nomogram can be used for identification of high-risk patients and to further guide clinical decisions.


Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:23
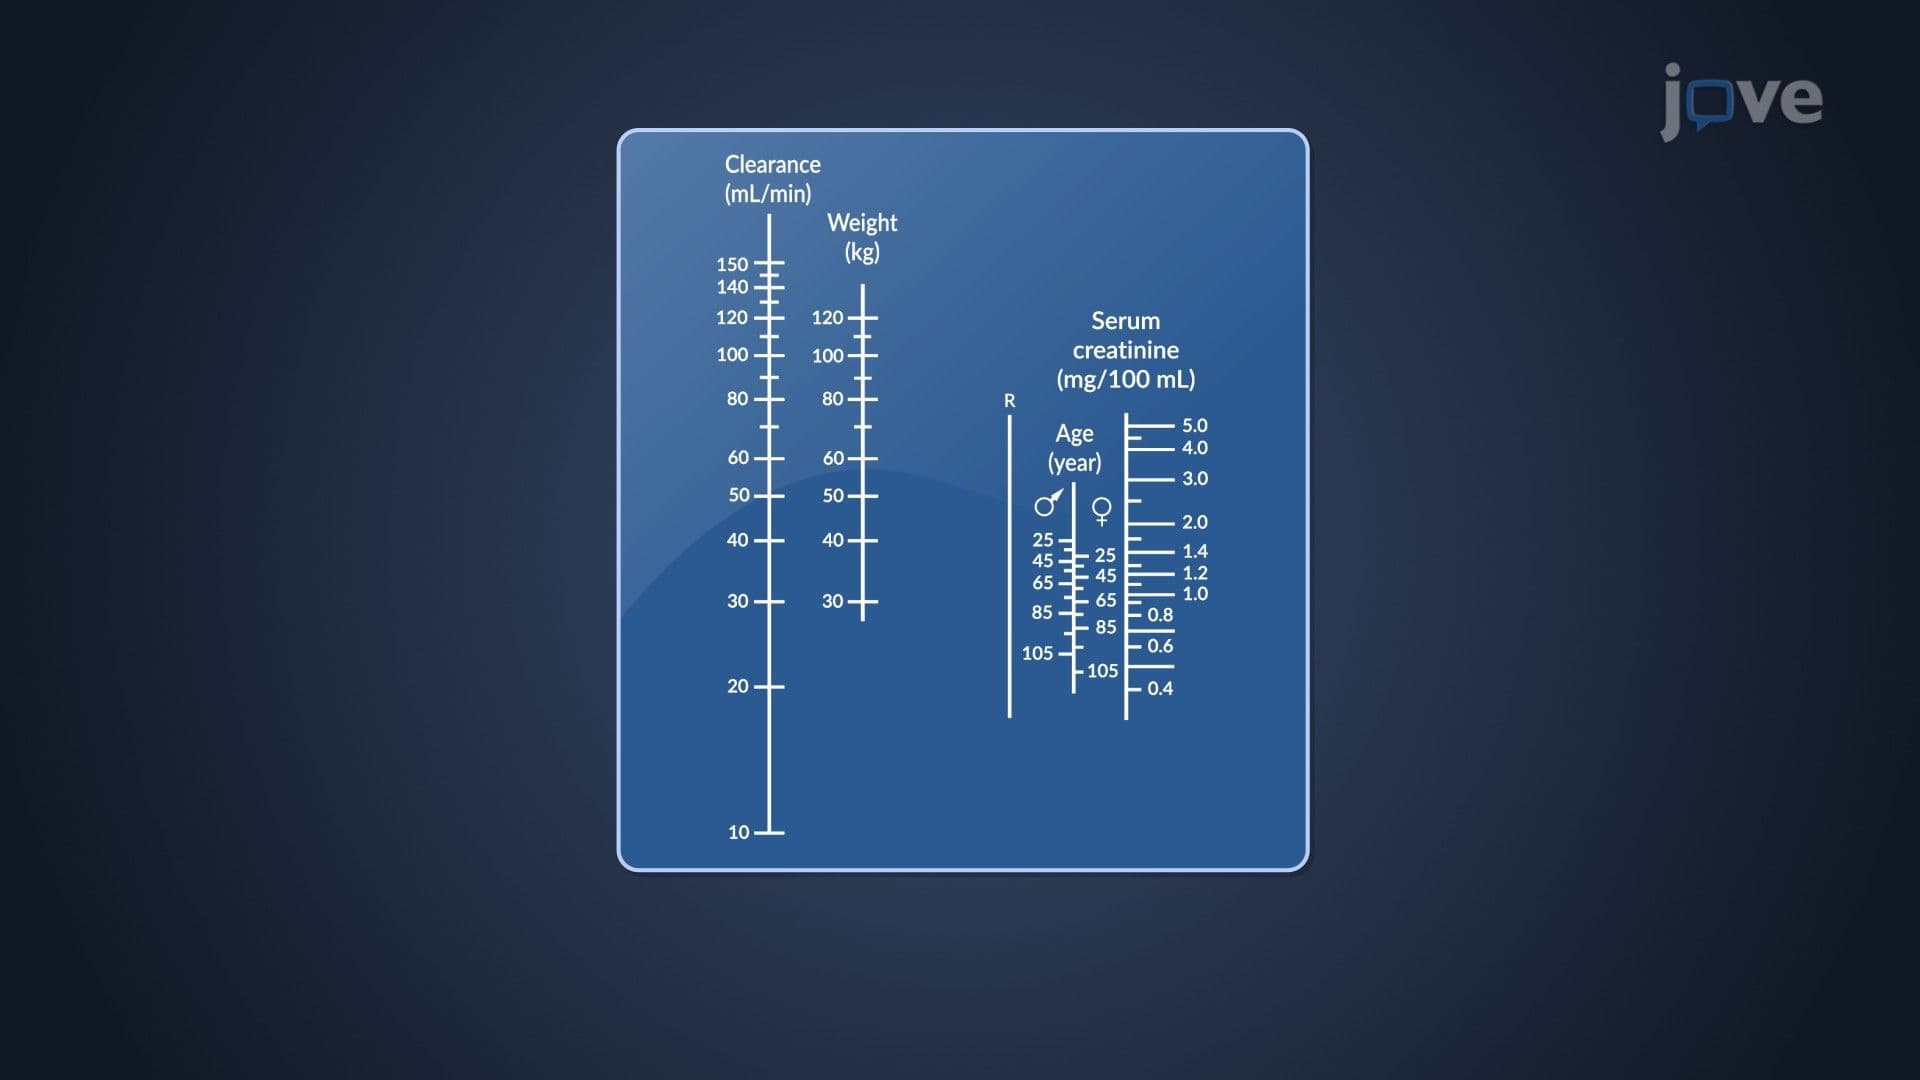
Dosage Regimen Designs: Nomograms and Tabulations
 01:22
Acute Kidney Injury I: Introduction
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration