Related Experiment Video
Updated: Oct 8, 2025
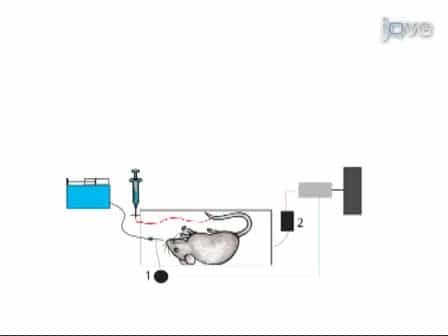

A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 13, 2010
Population Pharmacokinetics and Exposure-Response Relationships of Astegolimab in Patients With Severe Asthma
Naoki Kotani1,2, Michael Dolton1, Robin J Svensson3
1Genentech Inc., South San Francisco, California, USA.

Abstract:
Astegolimab is a fully human immunoglobulin G2 monoclonal antibody that binds to the ST2 receptor and blocks the interleukin-33 signaling. It was evaluated in patients with uncontrolled severe asthma in the phase 2b study (Zenyatta) at doses of 70, 210, and 490 mg subcutaneously every 4 weeks for 52 weeks. This work aimed to characterize astegolimab pharmacokinetics, identify influential covariates contributing to its interindividual variability, and make a descriptive assessment of the exposure-response relationships. A population pharmacokinetic model was developed using data from 368 patients in the Zenyatta study. Predicted average steady-state concentration was used in the subsequent exposure-response analyses, which evaluated efficacy (asthma exacerbation rate) and biomarker end points including forced expiratory volume in 1 second, fraction exhaled nitric oxide, blood eosinophils, and soluble ST2. A 2-compartment disposition model with first-order elimination and first-order absorption best described the astegolimab pharmacokinetics. The relative bioavailability for the 70-mg dose was 15.3% lower. Baseline body weight, estimated glomerular filtration rate, and eosinophils were statistically correlated with pharmacokinetic parameters, but only body weight had a clinically meaningful influence on the steady-state exposure (ratios exceeding 0.8-1.25). The exposure-response of efficacy and biomarkers were generally flat with a weak trend in favor of the highest dose/exposure. This study characterized astegolimab pharmacokinetics in patients with asthma and showed typical pharmacokinetic behavior as a monoclonal antibody-based drug. The exposure-response analyses suggested the highest dose tested in the Zenyatta study (490 mg every 4 weeks) performed close to the maximum effect, and no additional response may be expected above it.


Related Concept Videos
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce...
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes: