Related Experiment Video
Updated: Oct 8, 2025
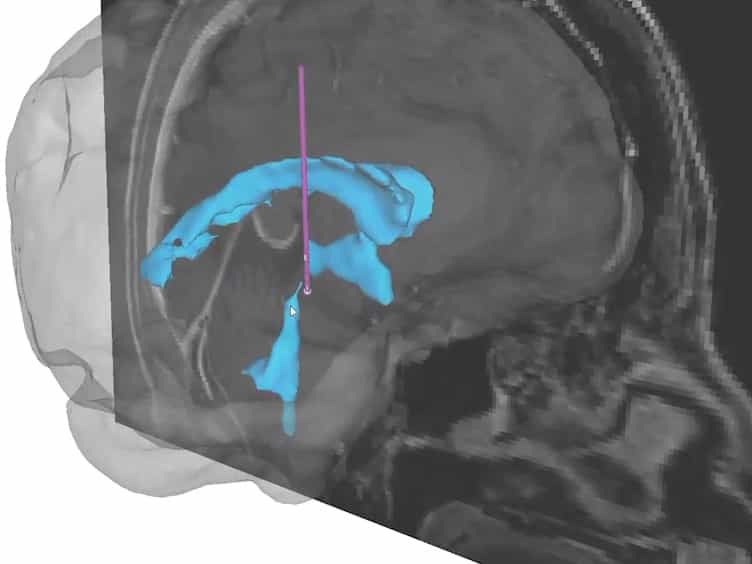
Targeting Neuronal Fiber Tracts for Deep Brain Stimulation Therapy Using Interactive, Patient-Specific Models
Published on: August 12, 2018
Economic evaluation of deep brain stimulation compared with vagus nerve stimulation and usual care for patients with
Hoi Yau Chan1, Ben F M Wijnen2,3, Marian H J M Majoie4,5,6,7
1Department of Health Services Research, Care and Public Health Research Institute, Maastricht University, Maastricht, the Netherlands.

Objectives:
This study was undertaken to estimate the cost-effectiveness of deep brain stimulation (DBS) compared with vagus nerve stimulation (VNS) and care as usual (CAU) for adult patients with refractory epilepsy from a health care perspective using a lifetime decision analytic model.
Methods:
A Markov decision analytic model was constructed to estimate the lifetime cost-effectiveness of DBS compared with VNS and CAU. Transition probabilities were estimated from a randomized controlled trial, and assumptions were made in consensus with an expert panel. Primary outcomes were expressed as incremental costs per quality-adjusted life-year (QALY) and per responder. Univariate and probabilistic sensitivity analyses were conducted to characterize parameter uncertainty.
Results:
In DBS, 28.4% of the patients were responders, with an average of 21.38 QALYs per patient and expected lifetime health care costs of €187 791. VNS had fewer responders (22.3%), fewer QALYs (20.70), and lower lifetime costs (€156 871). CAU had the fewest responders (6.2%), fewest QALYs (18.74), and lowest total health care costs (€64 670). When comparing with CAU, incremental cost-effectiveness ratios (ICERs) showed that costs per QALY gained were slightly lower for DBS (€46 640) than for VNS (€47 155). When comparing DBS with VNS, an incremental cost per additional QALY gained of €45 170 was found for DBS. Sensitivity analyses showed that ICERs were heavily dependent on assumptions regarding loss to follow-up in the respective clinical trial.
Significance:
This study suggests that, given current limited evidence, VNS and DBS are potentially cost-effective treatment strategies compared to CAU for patients with refractory epilepsy. However, results for DBS were heavily impacted by assumptions made to extrapolate nonresponse from the original trial. More stringent assumptions regarding nonresponse resulted in an ICER just above an acceptable willingness to pay threshold. Given the uncertainty surrounding the effectiveness of DBS and the large impact of assumptions related to nonresponse, further empirical research is needed to reduce uncertainty.
More Related Videos
 09:46
Analysis of Gene Expression Changes in the Rat Hippocampus After Deep Brain Stimulation of the Anterior Thalamic Nucleus
Published on: March 8, 2015
 09:16
A General Method for Evaluating Deep Brain Stimulation Effects on Intravenous Methamphetamine Self-Administration
Published on: January 22, 2016