Related Experiment Video
Updated: Oct 8, 2025
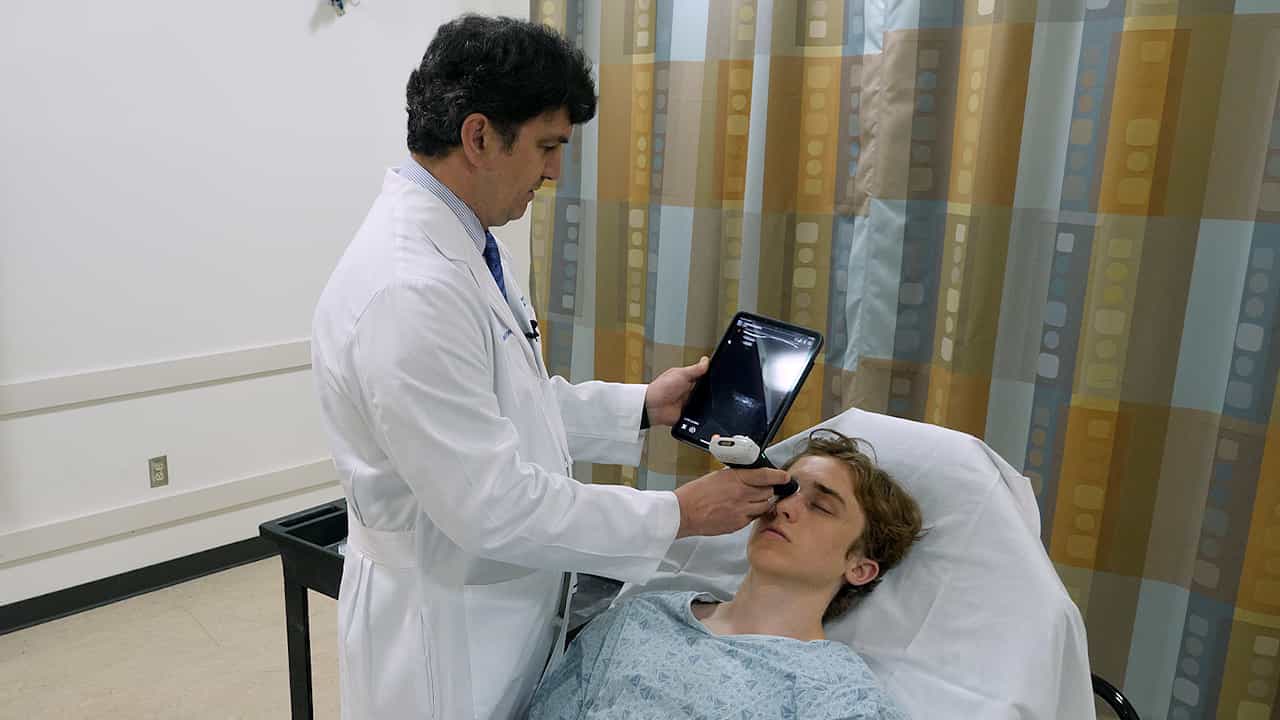
Optic Nerve Sheath Point of Care Ultrasound: Image Acquisition
Published on: August 18, 2023
Electrophysiological and fundoscopic detection of intracranial hypertension in craniosynostosis
Sohaib R Rufai1,2,3,4, Oliver R Marmoy1,2, Dorothy A Thompson1,2
1Clinical and Academic Department of Ophthalmology, Great Ormond Street Hospital for Children NHS Foundation Trust, London, WC1N 3JH, UK.

Insights
Fundoscopy reliably detects intracranial hypertension (IH) in craniosynostosis patients, but visual evoked potentials (VEPs) offer higher sensitivity, though with reduced specificity. Careful analysis of VEPs is crucial for accurate IH diagnosis.
Area of Science:
- Ophthalmology
- Neurology
- Pediatric Surgery
Background:
- Craniosynostosis requires surgical intervention, often involving spring-assisted posterior vault expansion (sPVE).
- Intracranial hypertension (IH) is a significant concern in these patients, potentially leading to visual complications.
- Accurate diagnostic methods for IH are essential for timely management.
Purpose of the Study:
- To evaluate the diagnostic accuracy of fundoscopy and visual evoked potentials (VEPs) in detecting intracranial hypertension (IH).
- To compare the sensitivity and specificity of fundoscopy versus VEPs for IH in children undergoing sPVE.
- To assess the correlation between diagnostic findings and final visual outcomes.
Main Methods:
- Retrospective diagnostic accuracy study of children with craniosynostosis undergoing sPVE.
- Intracranial pressure (ICP) monitoring (48-hour) was used as the gold standard for IH (mean ICP > 20 mmHg).
- Fundoscopy and VEP assessments were analyzed for sensitivity and specificity against IH diagnosis.
Main Results:
- Fundoscopy showed 32.1% sensitivity and 100% specificity for IH.
- Isolated VEPs had 58.3% sensitivity and 83.3% specificity.
- Longitudinal VEP analysis improved sensitivity but decreased specificity, with clinically significant deterioration showing 47.1% sensitivity and 100% specificity.
Conclusions:
- Fundoscopy is reliable for confirming IH when papilledema is present, but its absence does not rule out IH.
- VEP testing enhances sensitivity for IH detection but requires careful interpretation to balance sensitivity and specificity.
- Optimal diagnostic strategies may involve combining fundoscopy with nuanced VEP analysis for craniosynostosis patients.
Aims:
To assess the diagnostic accuracy of fundoscopy and visual evoked potentials (VEPs) in detecting intracranial hypertension (IH) in patients with craniosynostosis undergoing spring-assisted posterior vault expansion (sPVE).
Methods:
Children with craniosynostosis undergoing sPVE and 48-hour intracranial pressure (ICP) monitoring were included in this single-centre, retrospective, diagnostic accuracy study. Data for ICP, fundoscopy and VEPs were analysed. Primary outcome measures were papilloedema on fundoscopy, VEP assessments and IH, defined as mean ICP > 20 mmHg. Diagnostic indices were calculated for fundoscopy and VEPs against IH. Secondary outcome measures included final visual outcomes.
Results:
Fundoscopic examinations were available for 35 children and isolated VEPs for 30 children, 22 of whom had at least three serial VEPs. Sensitivity was 32.1% for fundoscopy (95% confidence intervals [CI]: 15.9-52.4) and 58.3% for isolated VEPs (95% CI 36.6-77.9). Specificity for IH was 100% for fundoscopy (95% CI: 59.0-100) and 83.3% for isolated VEPs (95% CI: 35.9-99.6). Where longitudinal deterioration was suspected from some prVEPs but not corroborated by all, sensitivity increased to 70.6% (95% CI: 44.0-89.7), while specificity decreased to 60% (95% CI: 14.7-94.7). Where longitudinal deterioration was clinically significant, sensitivity decreased to 47.1% (23.0-72.2) and specificity increased to 100% (47.8-100). Median final BCVA was 0.24 logMAR (n = 36). UK driving standard BCVA was achieved by 26 patients (72.2%), defined as ≥0.30 logMAR in the better eye.
Conclusion:
Papilloedema present on fundoscopy reliably indicated IH, but its absence did not exclude IH. VEP testing boosted sensitivity at the expense of specificity, depending on method of analysis.


