Related Experiment Video
Updated: Oct 8, 2025


X-ray Dose Reduction through Adaptive Exposure in Fluoroscopic Imaging
Published on: September 11, 2011
Technical note: Relationship between peak skin dose and fluoroscopic Ka,r : Clinical variations and application in
1Imaging Institute, Cleveland Clinic, Cleveland, Ohio, USA.

Background:
The reference point cumulative air kerma (Ka,r ) is a commonly used dose quantity for establishing substantial radiation dose levels (SRDLs) that can provide guidance for patient dose management actions following fluoroscopically guided procedures. However, the Ka,r may not correlate well with the patient peak skin dose (Dskin,max ) because the relationship between Ka,r and Dskin,max may vary widely due to clinical variations. Therefore, it may be prudent for institutions to establish different Ka,r -based SRDL values based on the clinical procedure type.
Purpose:
The present study investigates the relationship between Ka,r and Dskin,max for different clinical services and how that variation may overestimate or underestimate the need for patient follow-up. Additionally, the study suggests a possible framework for establishing Ka,r SRDLs based on the clinical data analysis.
Methods:
A retrospective analysis was performed for fluoroscopically guided interventions exceeding 5 Gy Ka,r . For each procedure, the patient Dskin,max was estimated and the ratio of Dskin,max to Ka,r (DKR) was calculated. Results were pooled into one of three clinical service categories: body interventions (n = 33), cardiac interventions (n = 81), or neurological (neuro) interventions (n = 44). The distributions in Ka,r , Dskin,max , and DKR were analyzed in aggregate and by the clinical service category.
Results:
The median Ka,r values for procedures exceeding 5 Gy were 6.0 Gy (95% CI [5.6, 6.4]) for body interventions, 5.8 Gy (95% CI [5.5, 6.0]) for cardiac interventions, and 6.3 Gy (95% CI [5.9, 6.6]) for neuro interventions. Dskin,max for the same procedure data sets were 5.0 Gy (95% CI [4.4, 5.6]) for body interventions, 5.5 Gy (95% CI [5.2, 5.8]) for cardiac interventions, and 3.7 Gy (95% CI [3.4, 4.0]) for neuro interventions. This resulted in median DKR values of 0.81 for body interventions, 0.91 for cardiac interventions, and 0.59 for neuro interventions.
Conclusions:
This study illustrates the need to understand the relationship between the reported Ka,r and the patient Dskin,max for different types of interventional procedures. This is especially important when an institution uses Ka,r as the parameter for establishing an SRDL threshold to identify patients who may require clinical follow-up. The implications of this research and a guide for how to implement these findings are elaborated on in the Discussion.
More Related Videos


Related Concept Videos
 01:25
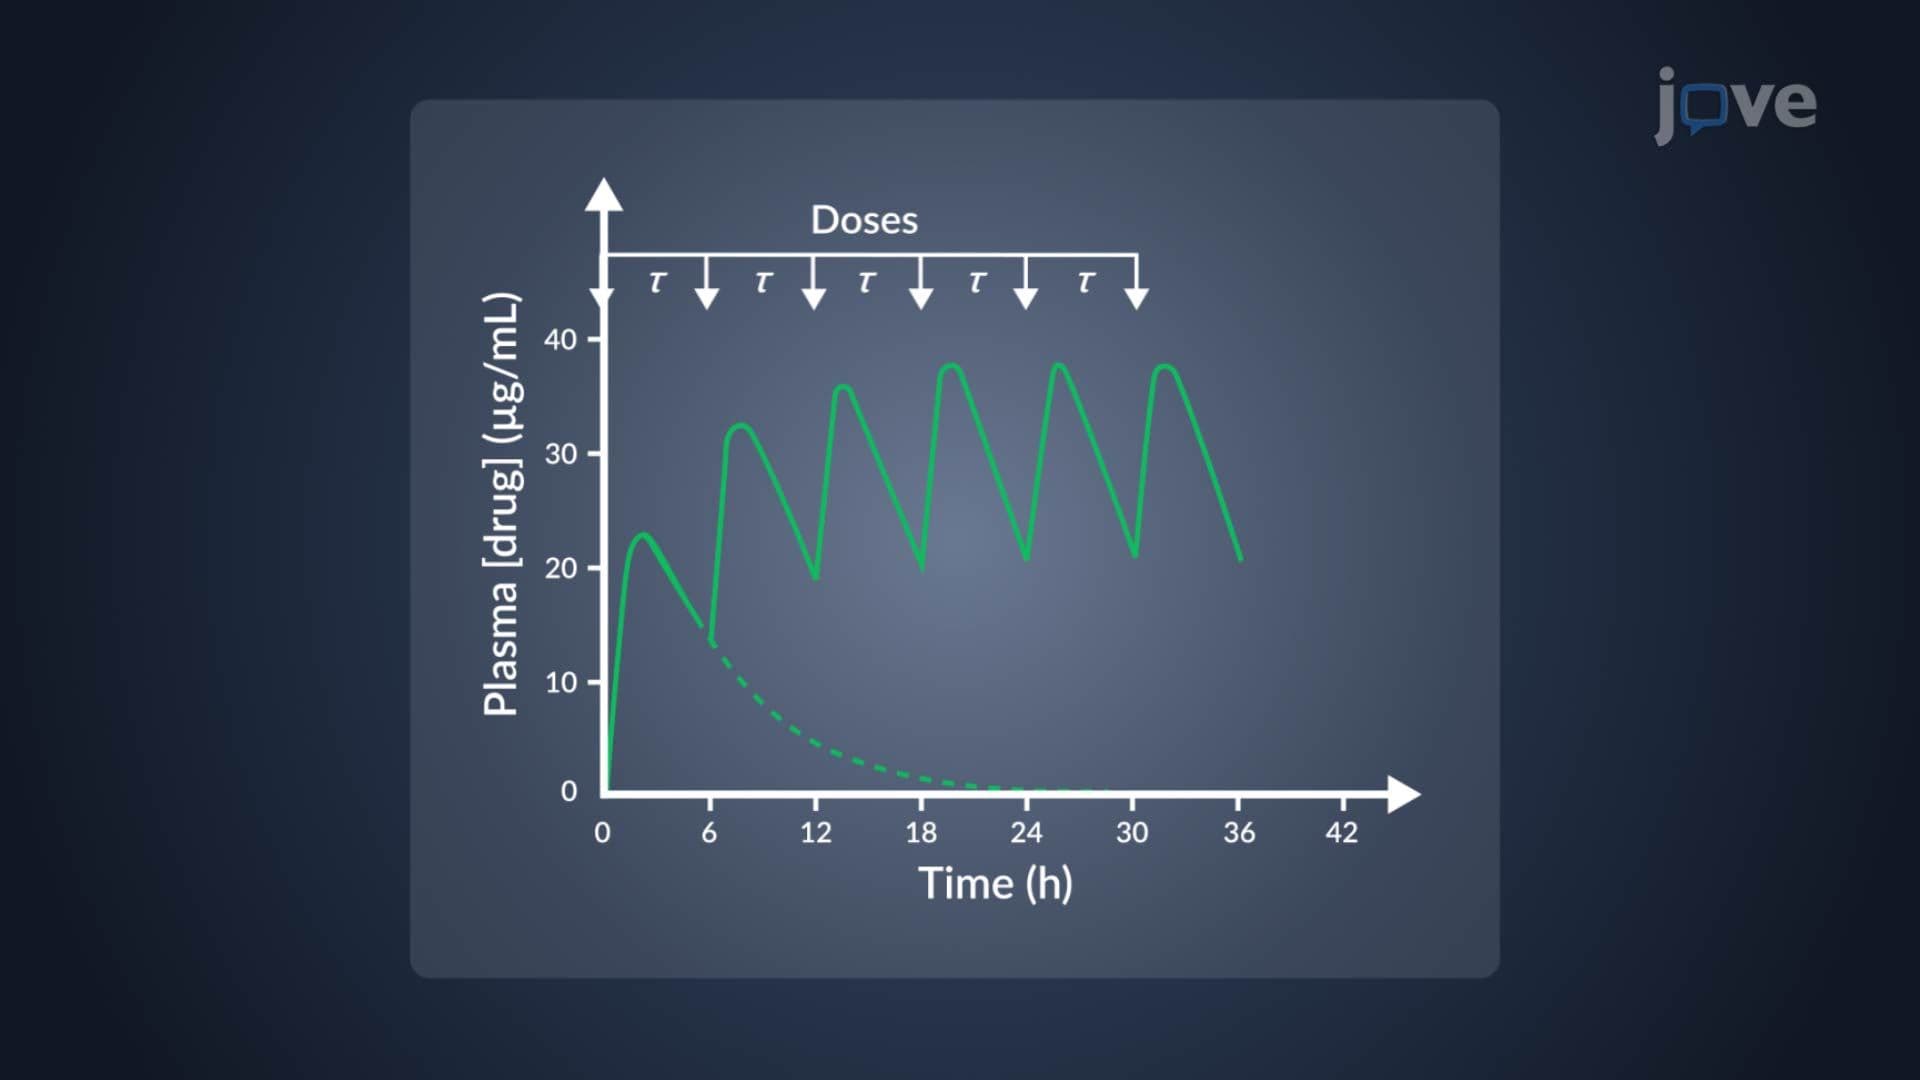
Dosage Regimen: Multiple Oral Dosage
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 02:59
Biological Effects of Radiation
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:20
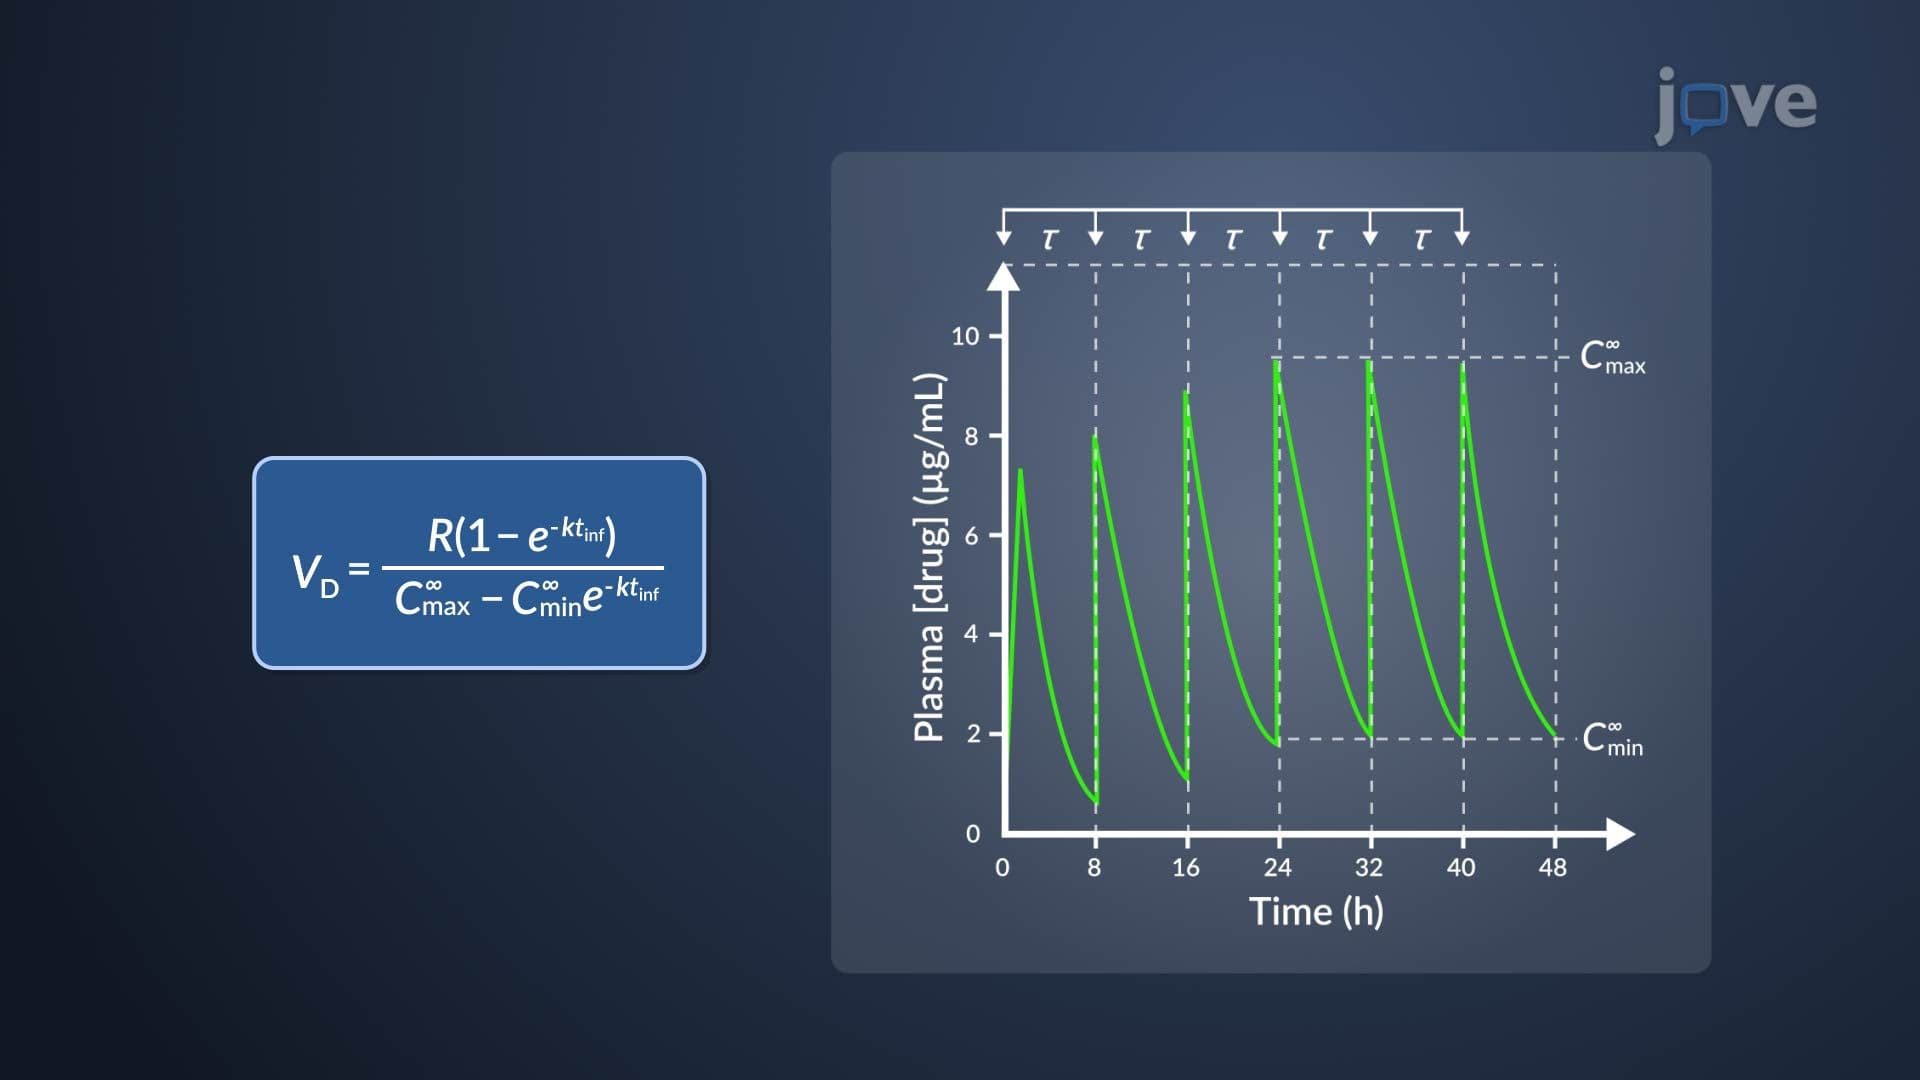
Estimation of k and VD of Aminoglycosides