Related Experiment Video
Updated: Oct 8, 2025


Measuring Local Anaphylaxis in Mice
Published on: October 14, 2014
Clinical features of anaphylaxis in children

Insights
Anaphylaxis in children is often triggered by food, especially in younger kids, while older children experience more drug or bee sting reactions. Improved recognition and management are crucial, particularly for infants and food-induced anaphylaxis cases.
Area of Science:
- Pediatric Allergy and Immunology
- Clinical Immunology
- Emergency Medicine
Background:
- Anaphylaxis incidence is rising globally, yet data on pediatric cases in developing nations remain scarce.
- Limited research exists on the specific clinical characteristics of childhood anaphylaxis in Turkey.
- Understanding demographic and trigger-specific features is vital for improving patient outcomes.
Purpose of the Study:
- To analyze the demographic and clinical features of anaphylaxis in Turkish children.
- To compare anaphylaxis characteristics across different age groups and etiological triggers.
- To identify areas for improved anaphylaxis recognition and management.
Main Methods:
- Retrospective analysis of medical records for 147 children (0-18 years) diagnosed with anaphylaxis between 2010-2019.
- Comparison of clinical features based on age groups (infants, <6 years, >6 years) and triggers (food, drugs, bee venom).
- Evaluation of symptom presentation, recurrence rates, emergency department (ED) epinephrine use, and specialist referrals.
Main Results:
- Food was the leading trigger (44.2%), prevalent in children <6 years; drugs (28.6%) and bee venom (22.4%) were more common in older children.
- Gastrointestinal symptoms were frequent in infants and food-induced anaphylaxis (FIA), while cardiovascular symptoms dominated in older children and drug-induced anaphylaxis.
- Only 47.6% received epinephrine in the ED, with lower rates in FIA patients (32.3%); specialist referral rates were also suboptimal, especially for FIA (10.8%).
- Drug-induced anaphylaxis showed the highest rate of severe reactions (57.1%).
Conclusions:
- Anaphylaxis presentation varies significantly by age and trigger in children.
- There is a critical need for enhanced anaphylaxis recognition and timely management, particularly for infants and those with FIA.
- Suboptimal epinephrine administration and specialist referral highlight significant gaps in current pediatric anaphylaxis care pathways.
Abstract:
Background: Despite the considerable increase in anaphylaxis frequency, there are limited studies on clinical features of anaphylaxis in children in developing countries. Objective: We aimed to analyze the demographic and clinical features of anaphylaxis in children in Turkey by comparing different age groups and triggers. Methods: Medical records of 147 children, ages 0-18 years, diagnosed with anaphylaxis between 2010 and 2019 were retrospectively analyzed. Results: The mean ± standard deviation age at first anaphylaxis episode was 5.9 ± 5.2 years, with a male predominance (63.9%); 25.2% were infants and 52.4% were < 6 years of age at their first anaphylaxis episode; 78.2% were atopic, with the highest frequency in children with food-induced anaphylaxis (FIA). The home (51.7%) was the most frequent setting. The overall leading cause of anaphylaxis was food (44.2%), which was more frequent at < 6 years of age, followed by drugs (28.6%) and bee venom (22.4%), both were more frequent among older children (>6 years). The patients with venom allergy had the highest rate of rapid onset of symptoms (p < 0.001). Gastrointestinal symptoms were observed significantly more in infants (48.6%) and in children with FIA (38.5%); cardiovascular symptoms were more frequently observed in children > 6 years of age (48.6%) and in children with drug-induced anaphylaxis (64.3%). Although recurrent anaphylaxis was reported for 23.1% of the patients, it was highest in the patients with FIA (35.9%). Overall, only 47.6% of the patients received epinephrine in the emergency department (ED) and 27.3% were referred to an allergy specialist, with the patients with FIA having the lowest rate for both, 32.3% and 10.8%, respectively. Children with drug-induced anaphylaxis had the highest rate of severe anaphylaxis (57.1%). Conclusion: There is a need to improve anaphylaxis recognition and management in all children regardless of age and trigger. Inadequate treatment was most evident in infants and patients with FIA.


Related Concept Videos
 02:06
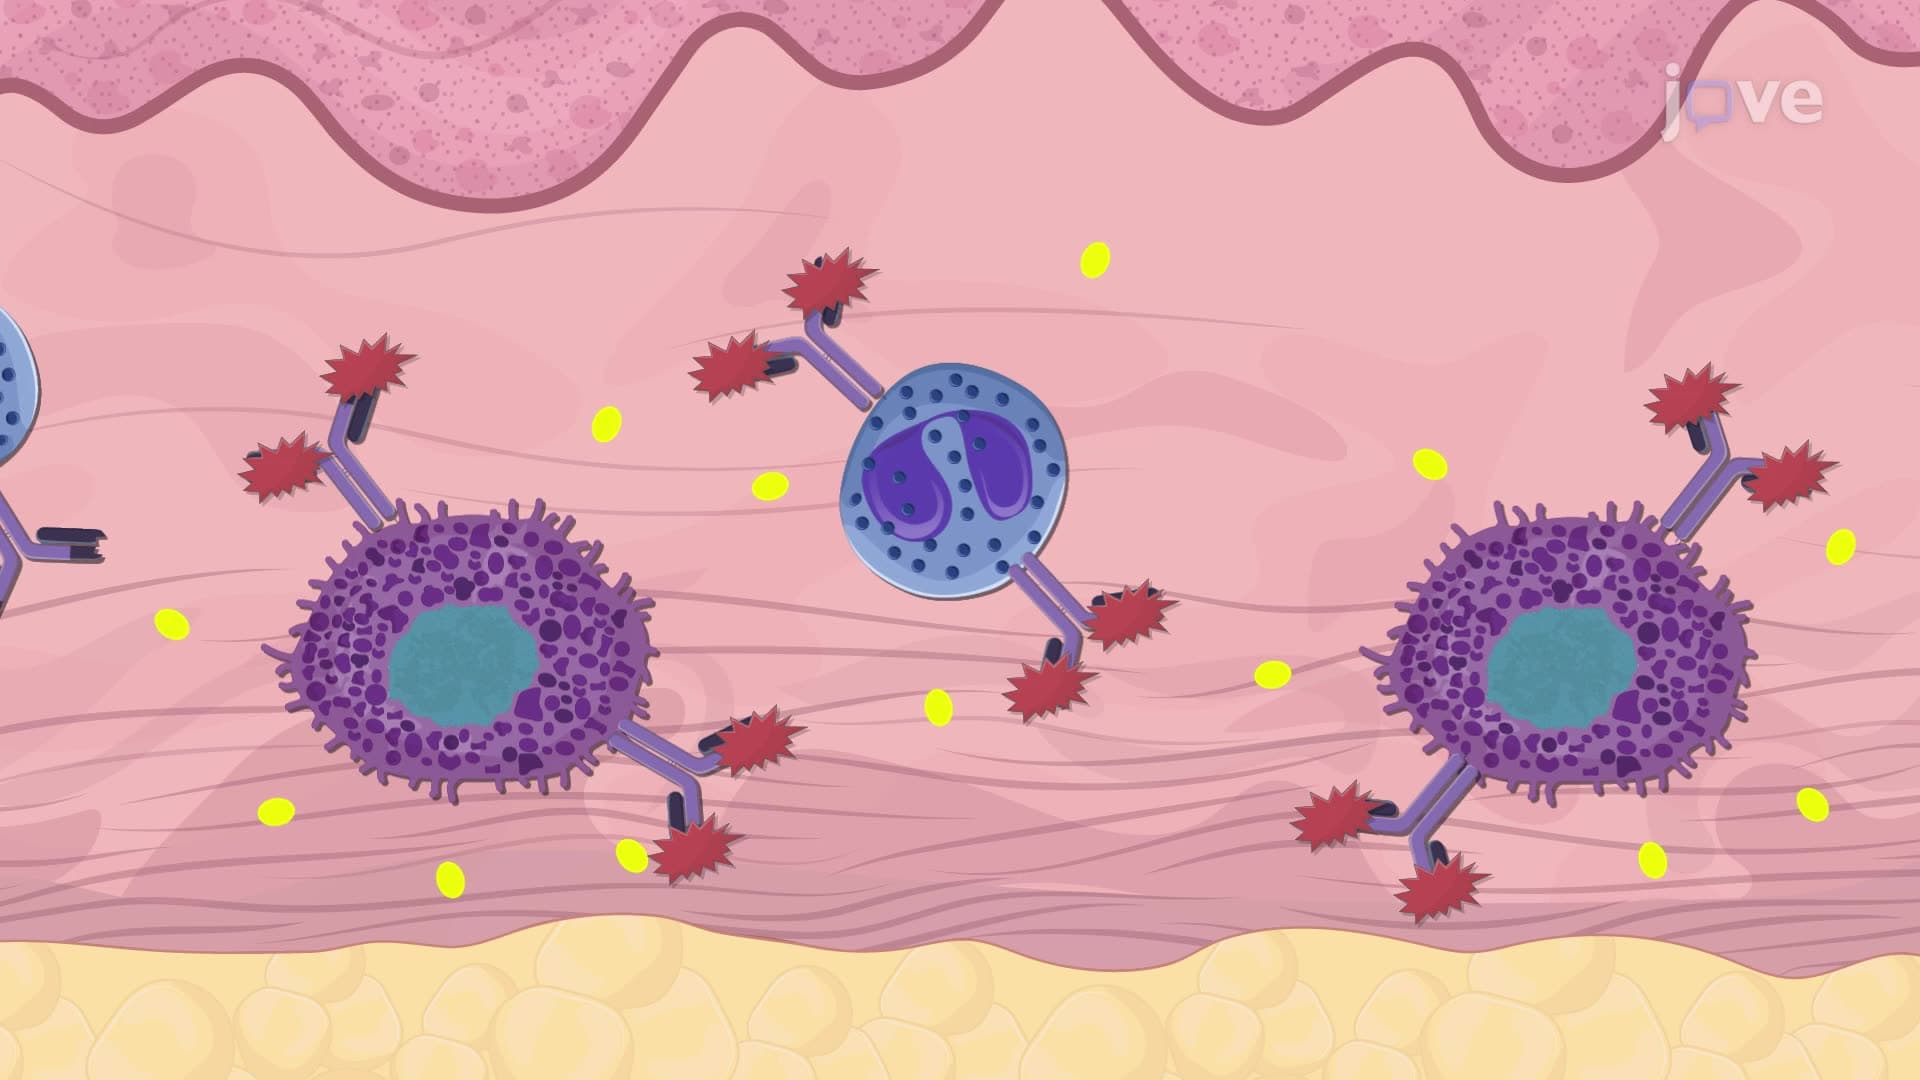
Allergic Reactions
 01:30
Hypersensitivities
Types of Hypersensitivities
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:27
Allergic Drug Reactions
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.