Related Experiment Video
Updated: Oct 7, 2025
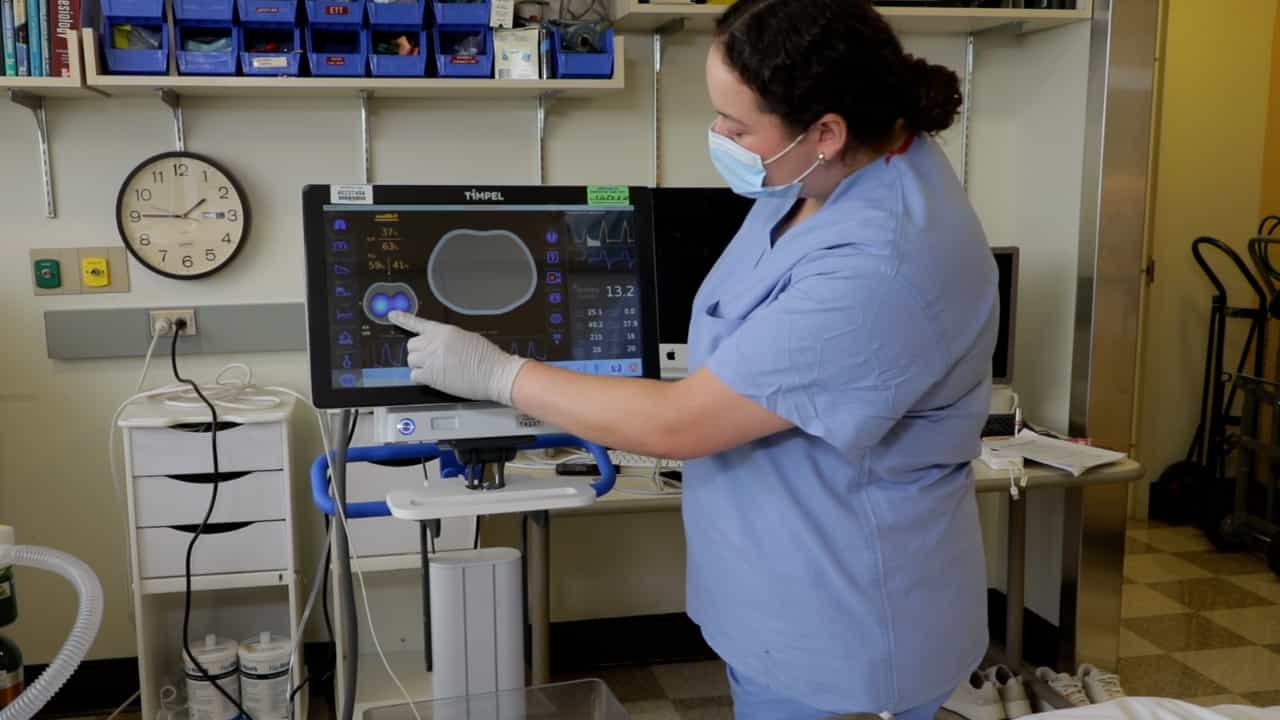
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Impact of therapeutic thoracentesis and pleural pressure changes on breathing pattern, dyspnea, lung function, and
Monika Zielinska-Krawczyk1, Anna M Stecka2, Elzbieta M Grabczak1
1Department of Internal Medicine, Pulmonary Diseases and Allergy, Medical University of Warsaw, Warsaw, Poland

Introduction:
Therapeutic thoracentesis is highly effective in providing symptomatic improvement in patients with large volume pleural effusion (PE). However, some physiological effects of pleural fluid (PF) withdrawal are still not fully elucidated.
Objectives:
The study aimed to evaluate alterations in the breathing pattern, pulmonary function, and arterial blood gases (ABG) in relation to both withdrawn PF volume and pleural pressure (Ppl) changes in patients undergoing therapeutic thoracentesis.
Patients And Methods:
This prospective, observational, cross‑sectional study included 37 patients with large volume PE. Respiratory rate (RR), dyspnea, pulmonary function, and ABG were assessed before the thoracentesis, at the termination of the PF withdrawal and 1, 3, and 24 hours after the procedure. The volume of PF drained, Ppl, and tidal volume (TV) were monitored during the thoracentesis.
Results:
Thoracentesis resulted in a transient but significant increase in RR directly after the procedure, and a transient decrease, followed by subsequent increase in TV. There was a significant and constant increase in forced vital capacity up to 24 hours after thoracentesis (P = 0.001). Oxygen partial pressure (PaO2) significantly improved directly after PF withdrawal (P = 0.01) and returned to baseline values after 24 hours. Thoracentesis was invariably associated with a significant increase in the amplitude of Ppl (Ppl_ampl) changes during the respiratory cycle (P <0.001).
Conclusions:
Therapeutic thoracentesis results in a modest improvement in pulmonary function, tran-sient increase in PaO2 and increase in Ppl_ampl. The improvement in pulmonary function and ABG is closely related to the volume of PF drained and pleural elastance. The increase in Ppl_ampl probably represents a more efficient work of the respiratory muscles.


Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...