Related Experiment Video
Updated: Oct 7, 2025
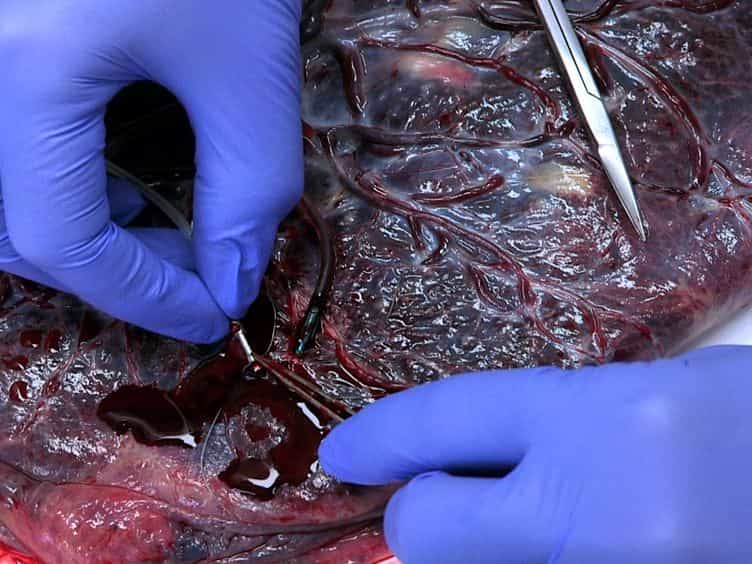

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Regulation of Placental Efflux Transporters during Pregnancy Complications
Danielle Kozlosky1, Emily Barrett1, Lauren M Aleksunes2
1Joint Graduate Program in Toxicology (D.K.) and Department of Pharmacology and Toxicology, Ernest Mario School of Pharmacy (D.K., L.M.A.), Rutgers University, Piscataway, New Jersey; Environmental and Occupational Health Sciences Institute, Piscataway, New Jersey (E.B., L.M.A.); Department of Biostatistics and Epidemiology, Rutgers School of Public Health, Piscataway, New Jersey (E.B.); and Center for Lipid Research, New Jersey Institute for Food, Nutrition, and Health, Rutgers University, New Brunswick, New Jersey (L.M.A.).

The placenta is essential for regulating the exchange of solutes between the maternal and fetal circulations. As a result, the placenta offers support and protection to the developing fetus by delivering crucial nutrients and removing waste and xenobiotics. ATP-binding cassette transporters, including multidrug resistance protein 1, multidrug resistance-associated proteins, and breast cancer resistance protein, remove chemicals through active efflux and are considered the primary transporters within the placental barrier. Altered transporter expression at the barrier could result in fetal exposure to chemicals and/or accumulation of xenobiotics within trophoblasts. Emerging data demonstrate that expression of these transporters is changed in women with pregnancy complications, suggesting potentially compromised integrity of placental barrier function. The purpose of this review is to summarize the regulation of placental efflux transporters during medical complications of pregnancy, including 1) placental inflammation/infection and chorioamnionitis, 2) hypertensive disorders of pregnancy, 3) metabolic disorders including gestational diabetes and obesity, and 4) fetal growth restriction/altered fetal size for gestational age. For each disorder, we review the basic pathophysiology and consider impacts on the expression and function of placental efflux transporters. Mechanisms of transporter dysregulation and implications for fetal drug and toxicant exposure are discussed. Understanding how transporters are up- or downregulated during pathology is important in assessing possible exposures of the fetus to potentially harmful chemicals in the environment as well as the disposition of novel therapeutics intended to treat placental and fetal diseases. SIGNIFICANCE STATEMENT: Diseases of pregnancy are associated with reduced expression of placental barrier transporters that may impact fetal pharmacotherapy and exposure to dietary and environmental toxicants.
The placenta is essential for regulating the exchange of solutes between the maternal and fetal circulations. As a result, the placenta offers support and protection to the developing fetus by delivering crucial nutrients and removing waste and xenobiotics. ATP-binding cassette transporters, including multidrug resistance protein 1, multidrug resistance-associated proteins, and breast cancer resistance protein, remove chemicals through active efflux and are considered the primary transporters within the placental barrier. Altered transporter expression at the barrier could result in fetal exposure to chemicals and/or accumulation of xenobiotics within trophoblasts. Emerging data demonstrate that expression of these transporters is changed in women with pregnancy complications, suggesting potentially compromised integrity of placental barrier function. The purpose of this review is to summarize the regulation of placental efflux transporters during medical complications of pregnancy, including 1) placental inflammation/infection and chorioamnionitis, 2) hypertensive disorders of pregnancy, 3) metabolic disorders including gestational diabetes and obesity, and 4) fetal growth restriction/altered fetal size for gestational age. For each disorder, we review the basic pathophysiology and consider impacts on the expression and function of placental efflux transporters. Mechanisms of transporter dysregulation and implications for fetal drug and toxicant exposure are discussed. Understanding how transporters are up- or downregulated during pathology is important in assessing possible exposures of the fetus to potentially harmful chemicals in the environment as well as the disposition of novel therapeutics intended to treat placental and fetal diseases. SIGNIFICANCE STATEMENT: Diseases of pregnancy are associated with reduced expression of placental barrier transporters that may impact fetal pharmacotherapy and exposure to dietary and environmental toxicants.
More Related Videos
 12:17
The 4-vessel Sampling Approach to Integrative Studies of Human Placental Physiology In Vivo
Published on: August 2, 2017
 05:31
Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
Related Concept Videos
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:06
Carrier-Mediated Transport
Active transport involves two types of membrane-spanning transporters: uptake and efflux. Uptake transporters are expressed in the small...
 01:14
Hepatic Drug Clearance: Role of Transporters
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...