Related Experiment Video
Updated: Oct 7, 2025


Lumped-Parameter and Finite Element Modeling of Heart Failure with Preserved Ejection Fraction
Published on: February 13, 2021
Cardiac geometry, function and mechanics in left ventricular non-compaction cardiomyopathy with preserved ejection
Sarah A Guigui1, Sofia A Horvath1, Ivan A Arenas1
1Echocardiography Laboratory, Columbia University Division of Cardiology, Mount Sinai Heart Institute, 4300 Alton Road, De Hirsch Meyer Tower Suite 2070, Miami Beach, FL, 33140, USA.

Insights
Left ventricular non-compaction (LVNC) with preserved ejection fraction (EF) shows abnormal heart geometry and reduced longitudinal mechanics. This suggests increased myocardial stiffness in affected adults.
Area of Science:
- Cardiology
- Cardiovascular Imaging
- Cardiac Mechanics
Background:
- Left ventricular non-compaction (LVNC) cardiomyopathy is often associated with reduced ejection fraction (EF) and dilated cardiomyopathy.
- Data on LVNC presenting with preserved EF in adults is limited.
- This study focuses on characterizing cardiac geometry and mechanics in LVNC patients with preserved EF.
Purpose of the Study:
- To evaluate cardiac geometry and mechanics in adult patients diagnosed with LVNC and preserved EF.
- To compare these parameters with a control group without LVNC.
Main Methods:
- Retrospective cohort study of 17 LVNC patients with preserved EF (2008-2019).
- LVNC diagnosis based on transthoracic 2D echocardiographic criteria.
- Matched 1:1 with controls without LVNC.
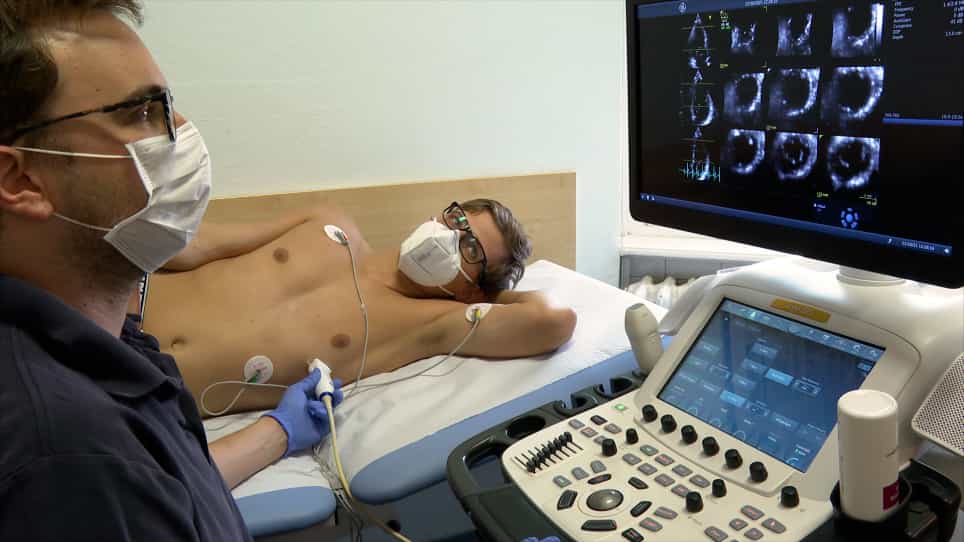
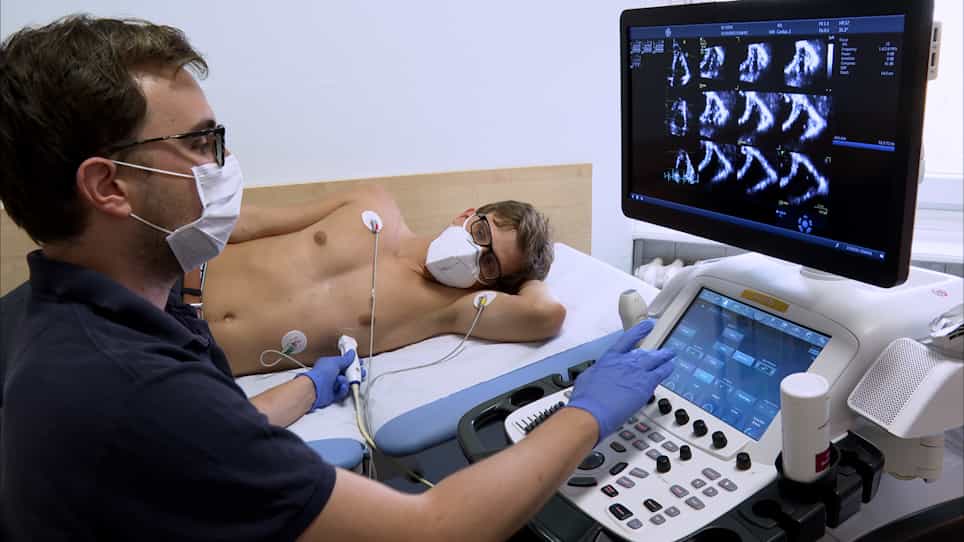
- Analysis of geometric, functional, and mechanical parameters using 2D and speckle-tracking echocardiography.
Main Results:
- LVNC patients had similar LV systolic function and chamber dimensions but increased mass and relative wall thickness compared to controls.
- Abnormal LV geometry was more prevalent in LVNC patients (76% vs. 18%).
- Significantly decreased global longitudinal strain and increased rigid body rotation were observed in the LVNC group.
Conclusions:
- LVNC with preserved EF is characterized by impaired LV geometry and longitudinal mechanics.
- Increased myocardial stiffness, indicated by rigid body rotation, is a feature of this condition.
- These findings differentiate LVNC with preserved EF from typical presentations.
Background:
Left ventricular non-compaction (LVNC) cardiomyopathy in adults has primarily been studied with a phenotypic expression of low ejection fraction (EF) and dilated cardiomyopathy; however, data on LVNC with preserved EF is scarce. The present study aimed to evaluate cardiac geometry and mechanics in LVNC patients with preserved EF.
Methods:
A retrospective cohort study of patients diagnosed with LVNC and a preserved EF between 2008 and 2019 was performed. LVNC was defined according to the presence of established transthoracic 2D echocardiographic (TTE) criteria as follows: (1) prominent LV trabeculations with deep recesses; (2) bi-layered myocardial appearance; and, (3) systolic non-compacted:compacted ratio≥ 2. Subjects were matched 1:1 to controls without LVNC referred for routine TTE. Geometric, functional and mechanics parameters were analyzed in the two cohorts using 2D and speckle-tracking TTE.
Results:
Seventeen patients with LVNC and preserved EF were identified. Compared with controls, patients with LVNC had similar LV systolic function and chamber dimensions, but a larger mass and relative wall thickness, and more abnormal LV geometry (76% vs. 18%, p = 0.002), LA remodeling, and pulmonary hypertension. Global longitudinal strain was significantly decreased (-15.4 ± 3.2 vs. -18.9 ± 2.8%, p = < 0.01) and the prevalence of rigid body rotation was significantly increased (57% vs. 14%, p = 0.05) in the LVNC population. The peak twist values were comparable in both cohorts.
Conclusions:
Impaired LV geometry and longitudinal mechanics, as well as increased myocardial stiffness as expressed by rigid body rotation, characterize LVNC with preserved EF when compared with controls.
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...