
COVID-19: a trigger for severe thrombotic microangiopathy in a patient with complement gene variant
Larisa Pinte1,2, Bogdan Marian Sorohan3,2, Zoltán Prohászka4
1Colentina Clinical Hospital, Internal Medicine Department, Bucharest, Romania.

Abstract:
The evidence regarding thrombotic microangiopathy (TMA) related to Coronavirus Infectious Disease 2019 (COVID-19) in patients with complement gene mutations as a cause of acute kidney injury (AKI) are limited. We presented the case of a 23-year-old male patient admitted with an asymptomatic form of COVID-19, but with uncontrolled hypertension and AKI. Kidney biopsy showed severe lesions of TMA. In evolution patient had persistent microangiopathic hemolytic anemia, decreased level of haptoglobin and increased LDH level. Decreased complement C3 level and the presence of schistocytes were found for the first time after biopsy. Kidney function progressively decreased and the patient remained hemodialysis dependent. Complement work-up showed a heterozygous variant with unknown significance in complement factor I (CFI) c.-13G>A, affecting the 5' UTR region of the gene. In addition, the patient was found to be heterozygous for the complement factor H (CFH) H3 haplotype (involving the rare alleles of c.-331C>T, Q672Q and E936D polymorphisms) reported as a risk factor of atypical hemolytic uremic syndrome. This case of AKI associated with severe TMA and secondary hemolytic uremic syndrome highlights the importance of genetic risk modifiers in the alternative pathway dysregulation of the complement in the setting of COVID-19, even in asymptomatic forms.

Related Concept Videos
 01:27
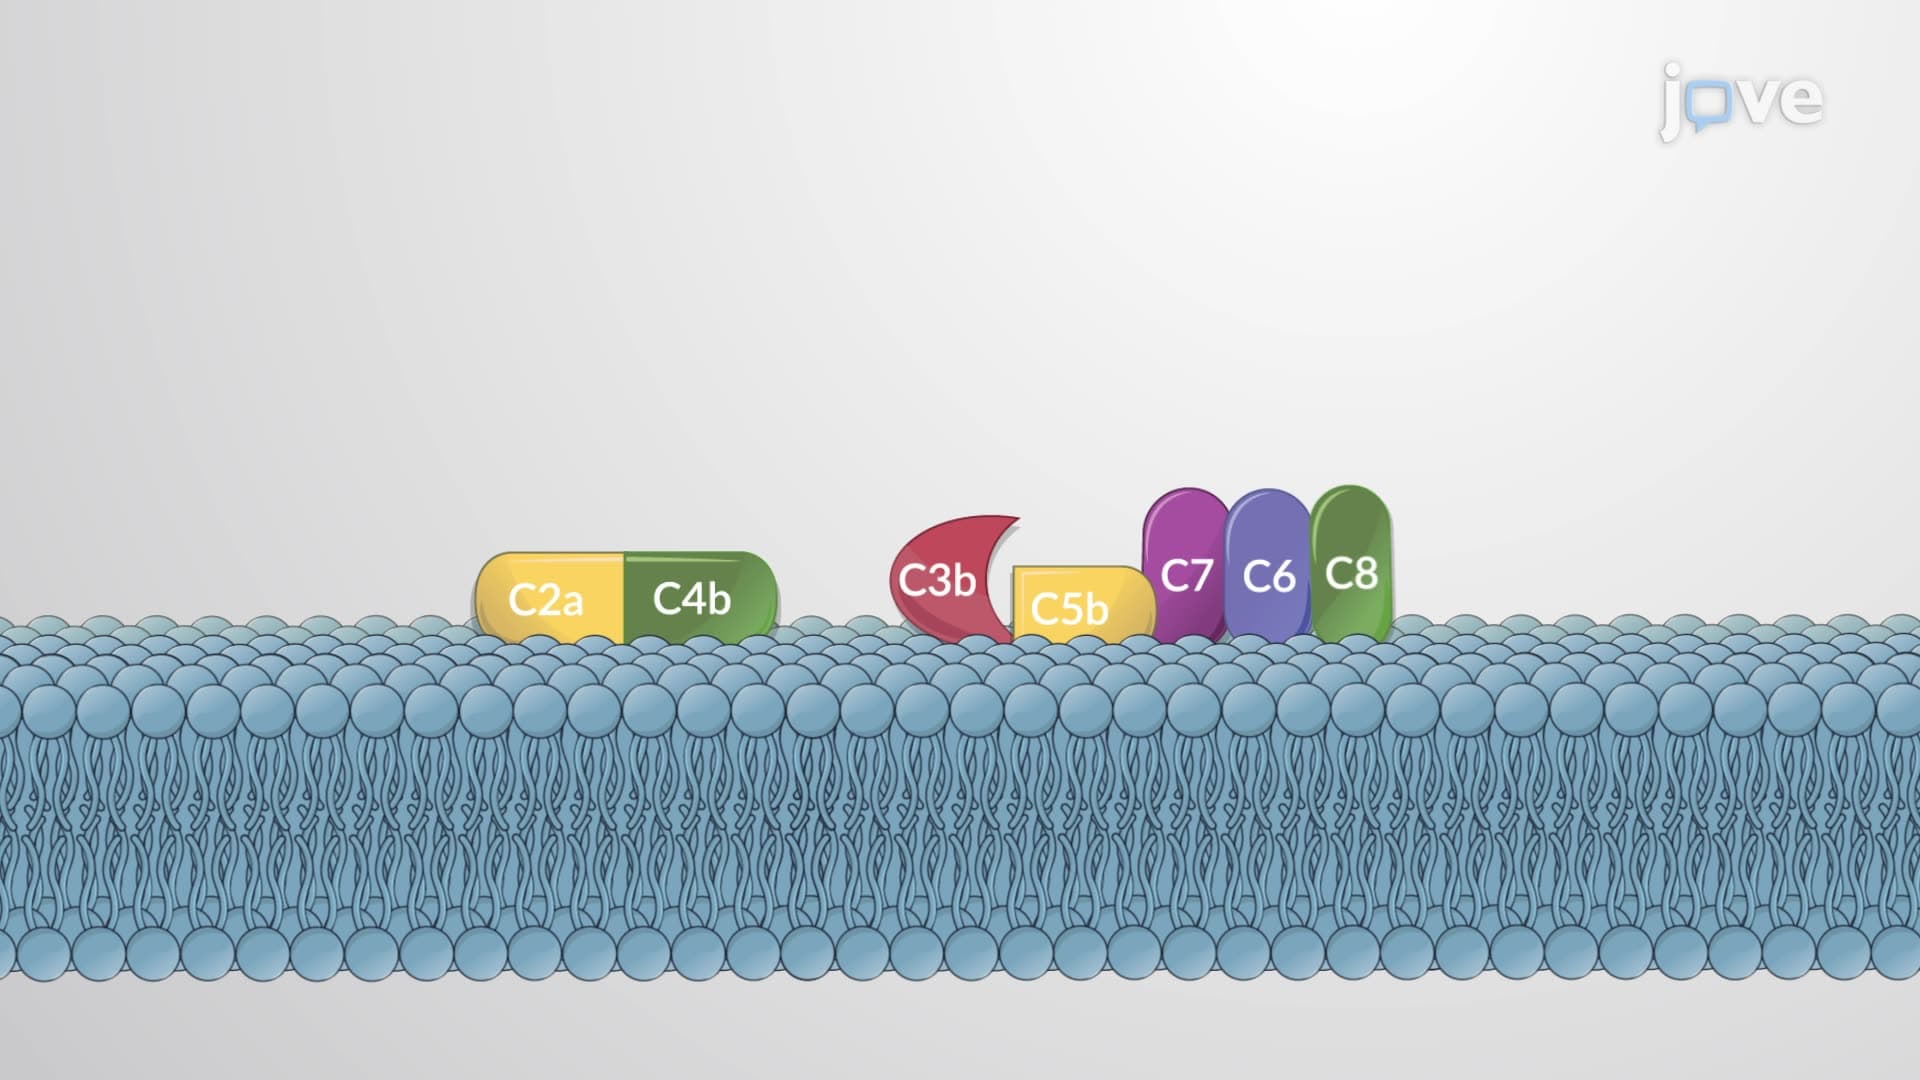
Complement System
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:30
Venous Thrombosis I: Introduction
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies