Related Experiment Video
Updated: Oct 7, 2025
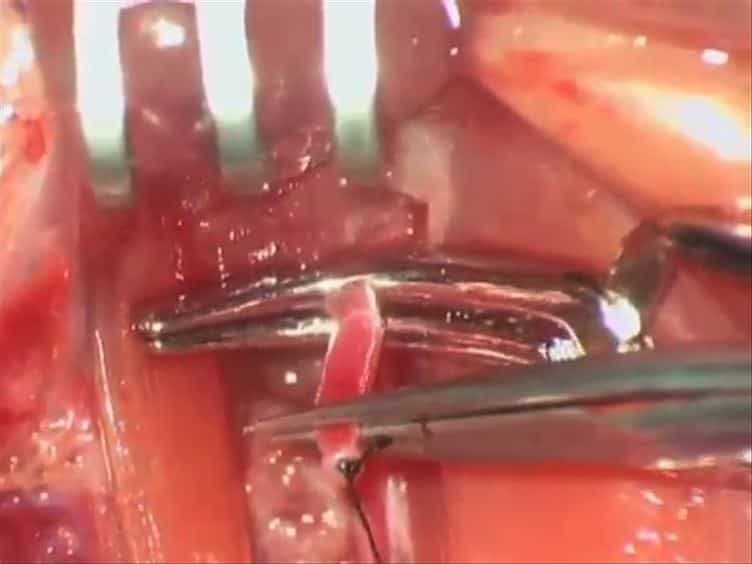

Training a Sophisticated Microsurgical Technique: Interposition of External Jugular Vein Graft in the Common Carotid Artery in Rats
Published on: November 11, 2012
Internal jugular to internal jugular vein bypass of symptomatic central vein obstruction
Jared Carleton1, Jason Chang1, Qinghua Richard Pu1
1Department of Vascular Surgery, Maimonides Medical Center, Brooklyn, NY, USA.

Insights
Central venous obstruction in hemodialysis patients can cause severe swelling. An internal jugular-jugular vein bypass successfully maintained arteriovenous fistula access and relieved symptoms in a challenging case.
Area of Science:
- Vascular Surgery
- Nephrology
- Interventional Radiology
Background:
- Central venous obstruction (CVO) affects 20%-40% of hemodialysis patients with upper extremity access.
- CVO can overwhelm collateral circulation, leading to severe upper extremity and facial swelling.
- Preserving existing hemodialysis access while managing CVO is complex.
Purpose of the Study:
- To present a case of successful internal jugular-jugular vein bypass in a hemodialysis patient with CVO.
- To demonstrate a method for maintaining arteriovenous fistula function despite brachiocephalic vein occlusion.
- To highlight strategies for managing complex access issues in end-stage renal disease.
Main Methods:
- A 49-year-old female hemodialysis patient with a right arm arteriovenous fistula presented with CVO symptoms.
- Angiography confirmed right brachiocephalic vein chronic occlusion.
- Endovascular revascularization attempts were unsuccessful.
Main Results:
- An internal jugular-jugular vein bypass was successfully created.
- The bypass maintained the right arm arteriovenous fistula.
- Patient symptoms of headaches, swelling, and vision changes resolved.
Conclusions:
- Internal jugular-jugular vein bypass is an effective option for preserving arteriovenous fistula in cases of central venous obstruction.
- This surgical approach addresses both access patency and symptom relief.
- It offers a viable solution for complex hemodialysis access management.
Introduction:
Central venous obstruction (CVO) often arises among hemodialysis patients with upper extremity access due to a varying number of risk factors. While the true incidence of CVO in hemodialysis patients is unknown, it been reported in the range of 20%-40% in dialysis patients undergoing venograms. In the non-hemodialysis population, chronic central vein obstruction has a compensatory mechanism comprised of numerous collaterals along the chest wall, neck, and mediastinum. However, the presence of an AVF or AVG ipsilateral to a central venous stenosis or occlusion can overwhelm the collateral network due to the significantly elevated blood flow. This may result in severe and debilitating upper extremity and fascial swelling. While ligation results in almost instantaneous symptomatic relief, it does not address the patient's underlying pathologic process and necessitates an additional access. As these patients continue to live longer, our strategies to manage these failing accesses are becoming increasingly complex. The goal of preserving existing access while correcting any symptoms is paramount. Previous case reports have documented various surgical options for preserving an existing access.
Case Presentation:
Our patient is a 49-year-old female with hypertension and end-stage renal disease, on hemodialysis through a right arm arteriovenous (AV) fistula. She had a history of multiple AV fistulae creations in the past, all of which previously thrombosed. Several years after the creation of her most recent fistula, she developed severe throbbing headaches, right arm and facial swelling, right eye lacrimation, and blurry vision. AV fistula angiogram demonstrated right brachiocephalic vein chronic occlusion and endovascular revascularization through both trans-AVF and transfemoral approaches were attempted, but unsuccessful.
Discussion:
This case illustrates the success of the creation of an internal jugular-jugular vein bypass to maintain a right arm arteriovenous fistula, while at the same time, correcting the symptoms of a right brachiocephalic vein occlusion.
More Related Videos
 07:02
A Rabbit Venous Interposition Model Mimicking Revascularization Surgery using Vein Grafts to Assess Intimal Hyperplasia under Arterial Blood Pressure
Published on: May 15, 2020
 07:53
Author Spotlight: Improved Imaging for Neovascular Development in Congenital Heart Disease Research
Published on: April 26, 2024
Related Concept Videos
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...
 01:24
Esophageal Varices-I: Introduction
 01:19
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care