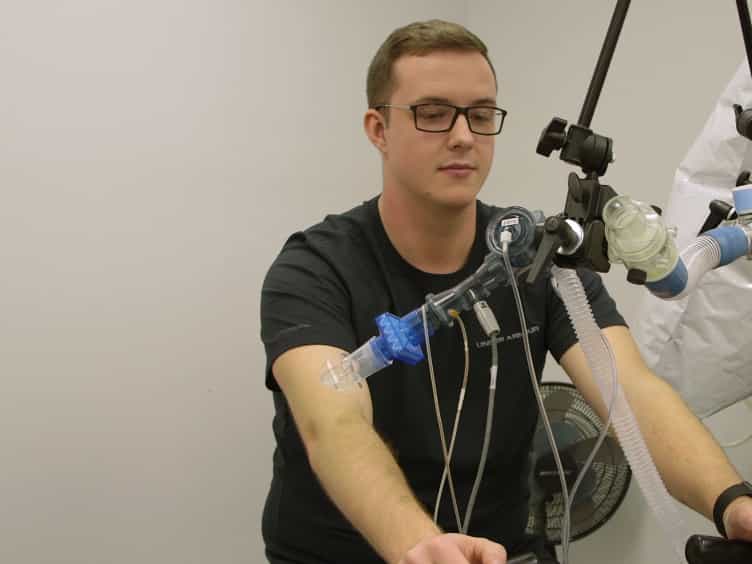

Mechanism of Dyspnea during Exercise in Children with Corrected Congenital Heart Disease
Mehdi Chlif1,2, Mohamed Mustapha Ammar3, Noureddine Ben Said4
1EA 3300 "APS and Motor Patterns: Adaptations-Rehabilitation", Picardie Jules Verne University, 80025 Amiens, France.

Insights
This study found that cardiorespiratory and peripheral muscle function are impaired after congenital heart disease surgery in children. However, subjective dyspnea threshold reliably predicts exercise capacity in these patients.
Area of Science:
- Pediatric Cardiology
- Exercise Physiology
- Rehabilitation Medicine
Background:
- Congenital heart disease (CHD) significantly impacts children's physical function post-surgical correction.
- Cardiorespiratory and peripheral muscle function are crucial for exercise capacity but are often compromised in these patients.
Purpose of the Study:
- To evaluate cardiorespiratory and peripheral muscle function in children after surgical correction of CHD.
- To determine the relationship between these physiological parameters and the subjective dyspnea threshold.
- To assess the predictive value of dyspnea threshold for exercise capacity.
Main Methods:
- Incremental cycle ergometer exercise testing to exhaustion in 13 children with surgically repaired CHD.
- Continuous gas exchange analysis for maximal aerobic parameters and ventilatory thresholds.
- 6-minute walk test (6MWT) for functional capacity and isokinetic Cybex Norm for peripheral muscle strength and endurance.
- Subjective dyspnea scoring using a visual analog scale during exercise.
Main Results:
- Exercise performance parameters (VO2 Peak, HR, VEmax, P max, maximal voluntary isometric force, time to exhaustion) were measured.
- Oxygen consumption at the dyspnea threshold correlated significantly with VO2 Peak (R²=0.74), time to exhaustion (R²=0.78), and 6MWT distance (R²=0.57).
- Surgical correction did not fully restore exercise performance compared to theoretical maximums, indicating persistent cardiorespiratory and peripheral limitations.
Conclusions:
- Exercise performance in children post-CHD surgery is limited by persistent cardiorespiratory and peripheral muscle dysfunction.
- The subjective dyspnea threshold is a reliable and valuable criterion for predicting exercise capacity in this population.
- Further research should focus on targeted rehabilitation strategies to improve functional outcomes.
Abstract:
This study will evaluate cardiorespiratory and peripheral muscle function and their relationship with subjective dyspnea threshold after the surgical correction of congenital heart disease in children. Thirteen children with surgically repaired congenital heart disease were recruited. Each participant performed an incremental exercise test on a cycle ergometer until exhaustion. Gas exchanges were continuously sampled to measure the maximal aerobic parameters and ventilatory thresholds. The functional capacity of the subjects was assessed with a 6 min walk test. At the end of the exercise test, isokinetic Cybex Norm was used to evaluate the strength and endurance of the knee extensor muscle in the leg. Dyspnea was subjectively scored with a visual analog scale during the last 15 s of each exercise step. Oxygen consumption measured at the dyspnea score/VO2 relationship located at the dyspnea threshold, at which dyspnea suddenly increased. Results: The maximal and submaximal values of the parameters describing the exercise and the peripheral muscular performances were: VO2 Peak: 33.8 ± 8.9 mL·min-1·kg-1; HR: 174 ± 9 b·min-1; VEmax: 65.68 ± 15.9 L·min-1; P max: 117 ± 27 W; maximal voluntary isometric force MVIF: 120.8 ± 41.9 N/m; and time to exhaustion Tlim: 53 ± 21 s. Oxygen consumption measured at the dyspnea threshold was related to VO2 Peak (R2 = 0.74; p < 0.01), Tlim (R2 = 0.78; p < 0.01), and the distance achieved during the 6MWT (R2 = 0.57; p < 0.05). Compared to the theoretical maximal values for the power output, VO2, and HR, the surgical correction did not repair the exercise performance. After the surgical correction of congenital heart disease, exercise performance was impeded by alterations of the cardiorespiratory function and peripheral local factors. A subjective evaluation of the dyspnea threshold is a reliable criterion that allows the prediction of exercise capacity in subjects suffering from congenital heart disease.
More Related Videos

Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:25
Hyperpnea and Hyperventilation
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:30
Mechanism of Breathing I: Inspiration
The respiratory system, an essential network for breathing, comprises the conducting and respiratory zones, each playing a crucial role in the overall process of respiration. Let us explore the detailed mechanism of inspiration, or inhalation, which is the first phase of the respiratory cycle.
Pathway of Air during Inspiration
During inspiration, air enters our body through the nose or mouth and moves through the conducting zone,...